Related Experiment Video
Updated: Jun 3, 2025
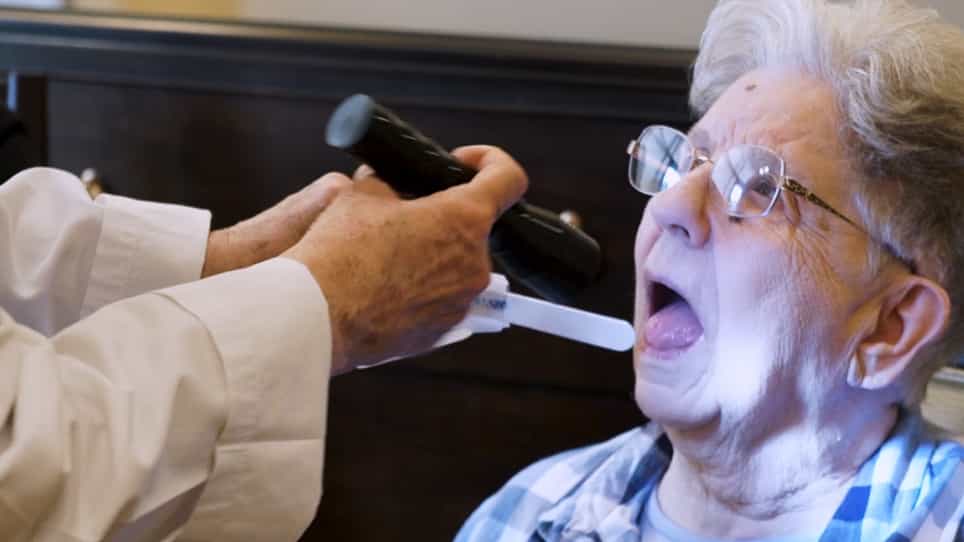

Oral Health Assessment by Lay Personnel for Older Adults
Published on: February 2, 2020
Prediction of oral diseases in care dependent older people
Christina Andersen1, Astrid Pernille Jespersen2, Kim Ekstrand3
1Department of Odontology, Faculty of Health and Medical Sciences, University of Copenhagen, Nørre Allé 20, Copenhagen, 2200, Denmark. christina.andersen@sund.ku.dk.

Background:
A large number of older people depend on others for help with their daily personal care, including oral health care. Nursing home and elder-care staff often face challenges identifying older people, who are exposed to or at an increased risk of oral diseases. Thus, the aim of this study was to identify risk factors that non-dental care staff can use to identify older people at risk of oral diseases and poor oral hygiene.
Methods:
In this cross-sectional study, the oral health and risk factors for poor oral health were determined for 217 care dependent older people living in two nursing homes and a rehabilitation centre or receiving home care in two Danish municipalities. The outcome variables for oral disease i.e. caries, periodontitis, and gingivitis, and oral hygiene, i.e. plaque and calculus, were assessed using standardised oral examinations. Risk factors for oral diseases and poor oral hygiene were assessed based on a questionnaire concerning (1) background information, (2) health status, (3) social support, (4) oral health behaviours, and (5) self-reported oral health. The associations between oral health and risk factors were investigated using logistic regression analyses.
Results:
In general, older people with different living arrangements had quite similarly distributed risk factors. The oral examinations showed that 54.5% had oral diseases, and 14.8% had poor oral hygiene. Not seeing a dentist regularly was significantly associated with having oral diseases (Odds Ratio, 2.87; CI, 1.53-5.39) and poor oral hygiene (OR, 4.50; CI, 1.83-11.05). A significant association was found between the presence of an oral disease and adversely affected quality of life (OR, 2.65; CI, 1.42-4.95), especially due to challenges eating (OR, 3.76; CI, 1.64-8.60) and/or smiling and showing teeth (OR, 3.64; CI, 1.27-10.42). A significant association was also found between poor oral hygiene and taking psychotropic drugs (OR, 2.61; CI, 1.08-6.30).
Conclusion:
Questions regarding the use of the dental care system and oral health problems could be used by nondental care staff in conversations with older people to determine their risk of oral diseases and poor oral hygiene.


Related Concept Videos
 01:26
Assessment of the Mouth
Mouth Inspection
The inspection begins with visually examining the mouth for symmetry, color, and size.
 01:21
Tooth Anatomy
The Crown, Neck, and Root
The visible part of the tooth is referred to as the crown. It's covered by enamel, the hardest substance in the human body. The crown is uniquely shaped for each type of tooth, allowing for different functions such as cutting, tearing, or...
 01:15
Teeth
In the bud stage, the tooth germ (an aggregation of cells) starts to form in the developing jawbone. During the cap stage, the tooth germ differentiates into enamel organ, dental papilla, and dental sac, which will later develop into the tooth's enamel, dentin...
 01:11
Oral Cavity
Teeth: The teeth are the hardest structures in our bodies. Humans have two sets of teeth throughout their lifetime: deciduous (baby) teeth and permanent teeth. Each tooth consists of several parts: the crown (visible part), the root (embedded in the jaw), enamel (hard outer...
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History