Related Experiment Video
Updated: Aug 1, 2026


Harvest of Endothelial Cells from the Balloon Tips of Swan-Ganz Catheters after Right Heart Catheterization
Published on: January 23, 2019
Peripheral vascular emboli in patients with infective endocarditis are common
Eric Sung1, Eric H Awtry2, Daniel J Koh1
1Division of Vascular and Endovascular Surgery, Department of Surgery, Boston Medical Center, Boston University Chobanian and Avedisian School of Medicine, Boston, MA.

Objective:
Infective endocarditis (IE) is associated with significant morbidity and mortality and places patients at risk for subsequent peripheral vascular emboli. Our goals were to analyze the incidence of peripheral emboli and their associated complications and outcomes.
Methods:
A retrospective single-center review of all patients with IE from 2013 through 2021 was performed. Patients with IE who had peripheral vascular emboli were identified, and their clinical characteristics and outcomes were analyzed.
Results:
Overall, 525 patients with IE were identified, and of these, 14.3% had peripheral emboli. In patients with peripheral emboli, the average age was 47 years, and 58.7% were of male gender; race composition included 56% White and 24% Black patients. Comorbidities included hypertension (49.3%), congestive heart failure (30.7%), prior valve replacement/repair (26.7%), and diabetes (24%). Intravenous drug use (62.7%) was the most common cause of IE, followed by non-dental infectious sources (16%), an indwelling catheter (6.7%), or dental infection (4%). Valve distribution was mitral (45.3%), aortic (28%), and tricuspid (24%). Gram-positive organisms, including methicillin-resistant Staphylococcus aureus (30.7%) and methicillin-susceptible Staphylococcus aureus (25.3%), were the most commonly identified bacteria, and Candida was identified in 6.7% of patients. Splenic (57.3%; n = 43) and renal (32%; n = 24) arteries were the most common locations for peripheral vascular emboli, followed by lower (28%; n = 21) and upper extremity (2.7%; n = 2) arteries. Cerebrovascular emboli occurred concurrently in 20 patients (26.7%) with other peripheral emboli. The most common locations for embolism that underwent an intervention were the common femoral (54.4%), superficial femoral (54.4%), popliteal (36.4%), tibial (27.3%), deep femoral (27.3%), peroneal (9.1%), superior mesenteric (SMA) (9.1%), and brachial (9.1%) arteries. Although open surgical embolectomy (81.8%) was the most common intervention, one patient underwent an endovascular intervention. Other interventions included two lower extremity amputations (one primary and one after embolectomy), one infrapopliteal bypass for a popliteal artery occlusion, and an attempted SMA embolectomy stopped due to cardiac arrest. One patient with splenic and cerebrovascular emboli had a mycotic thoracic aneurysm, which was deemed nonoperative. At 30 days, 1 year, and 5 years, 92%, 83%, and 65% of patients with IE survived, respectively; among those with IE and peripheral emboli, 86%, 71%, and 43% of patients survived, respectively (P = .01). Those who underwent peripheral vascular interventions had a 1- and 5-year survival of 45.5% and 36.6%, respectively.
Conclusions:
Peripheral vascular emboli are common in patients with IE and frequently occur in association with cerebral embolic events. Overall morbidity and mortality are high in this young population, in particular for those undergoing interventions.


Related Concept Videos
 01:25
Endocarditis I: Introduction
 01:25
Endocarditis II: Clinical Features of Infective Endocarditis
 01:18
Endocarditis III: Medical Management
 01:29
Endocarditis IV: Nursing Management
 01:29
Pulmonary Embolism I: Introduction
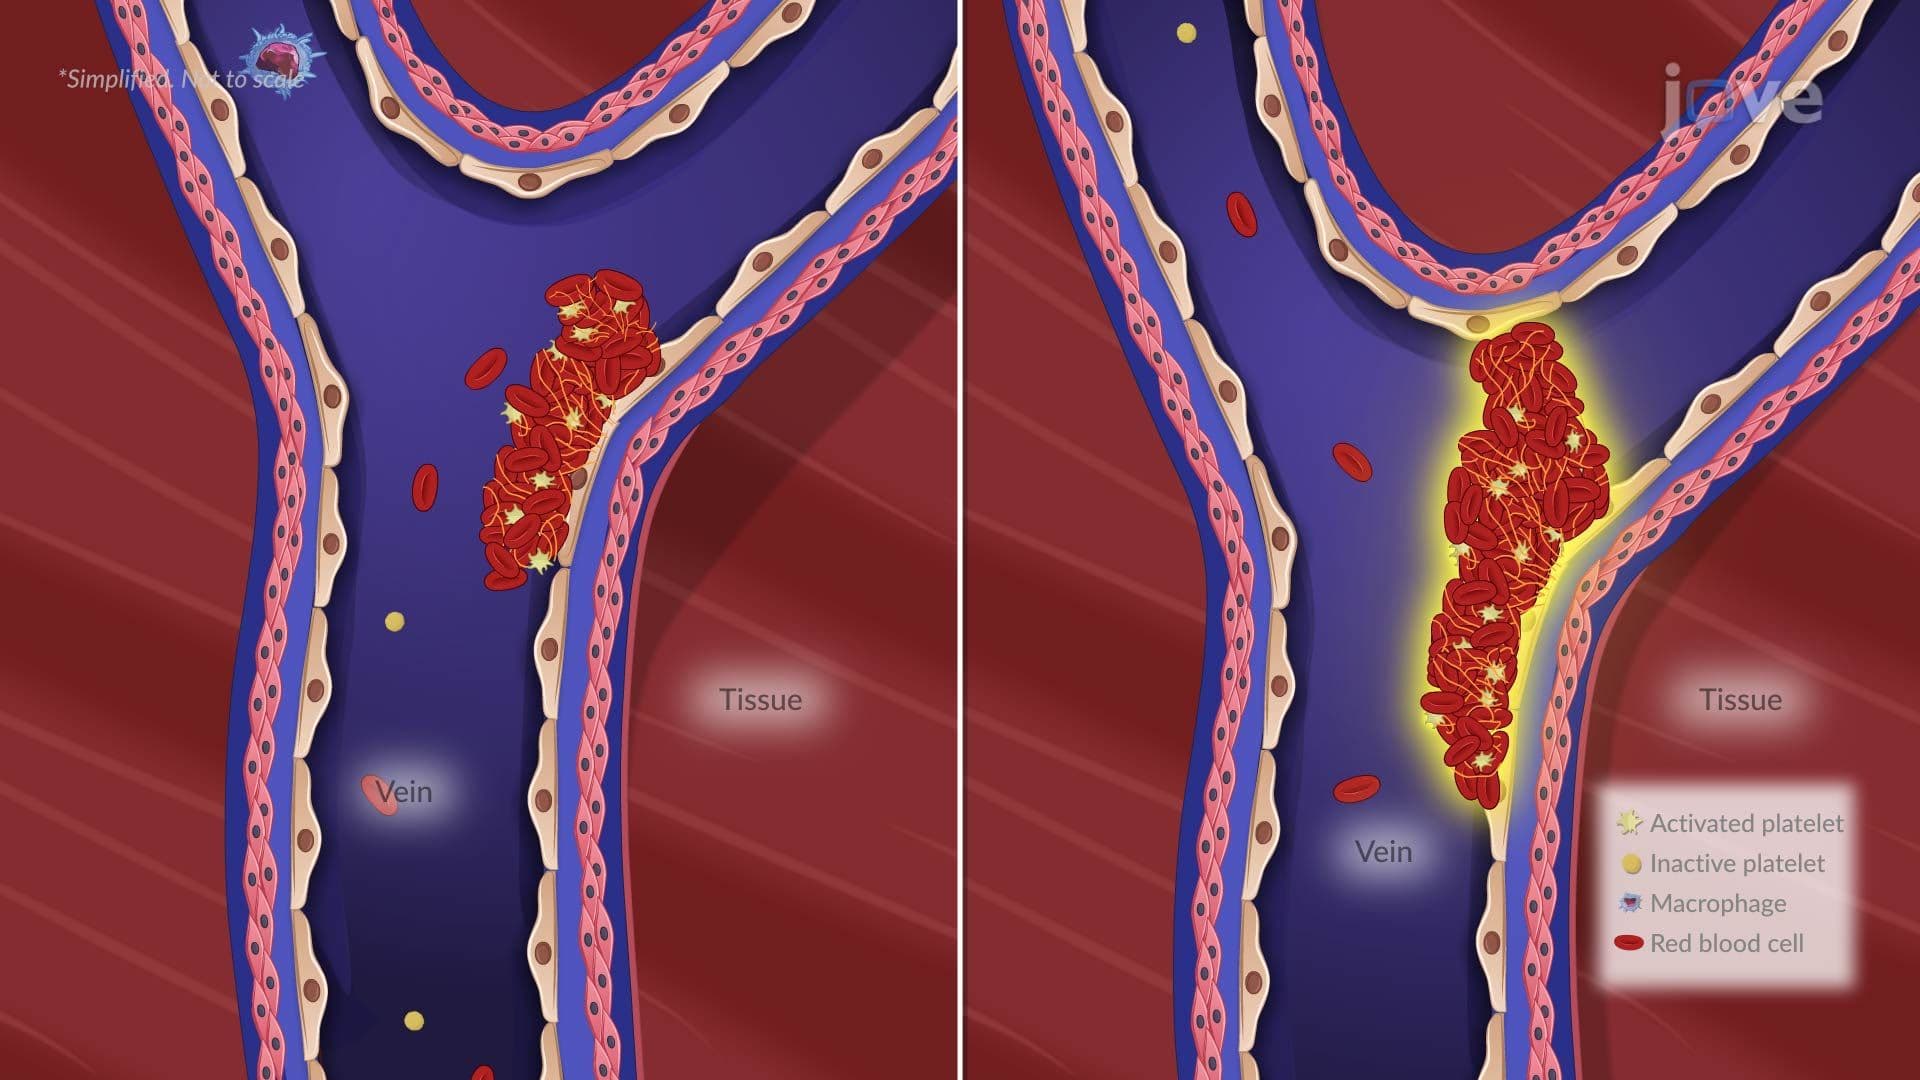 01:19
Pulmonary Embolism I: Introduction