Related Experiment Video
Updated: Jun 1, 2025

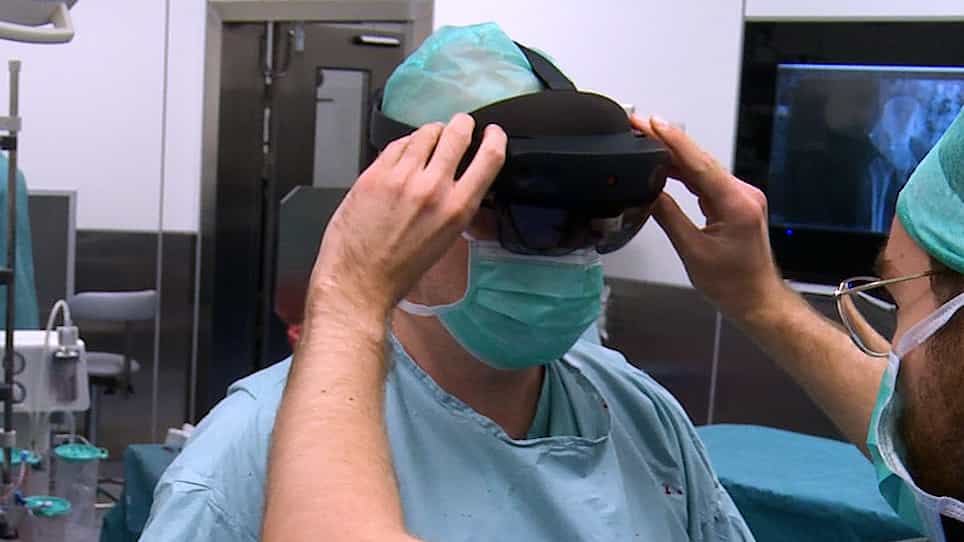
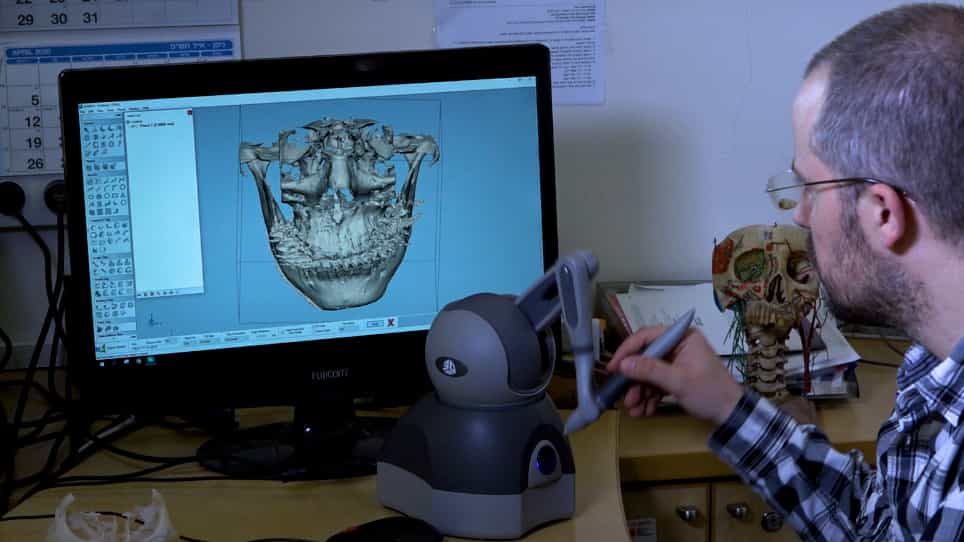
Three-Dimensional Preoperative Virtual Planning in Derotational Proximal Femoral Osteotomy
Published on: February 17, 2023
3D-printed patient-specific instrumentation and the freehand technique in high-tibial osteotomy: A prospective
Giovanni Grillo1,2, Alexandre Coelho1, Xavier Pelfort1
1Department of Orthopedics and Traumatology, Knee Unit, Parc Taulí Hospital Universitari, Institut d'Investigació I Innovació Parc Taulí (I3PT-CERCA) Universitat Autònoma Barcelona (UAB) Sabadell Spain.

Purpose:
Tibial valgus osteotomy has shown to be a successful and cost-effective procedure. The advent of image processing and three-dimensional (3D) printing is an interesting tool for achieving more accurate and reproducible results. The aim of our study was to compare the accuracy of the conventional technique and the use of customized guides in the correction of tibial deformities in tibial varus patients, the surgical and clinical benefits, and the impact of treatment in the outpatient setting.
Methods:
A prospective cohort of 30 patients who underwent tibial valgus osteotomy were selected and randomized into two groups (3D-printed guidewires and conventional techniques). All patients underwent a complete radiological study to plan the surgical procedure. During the surgical procedure, the surgical time and X-ray exposure were analysed. The following results were evaluated: surgical time and X-ray exposure, the correlation between the planned correction and the correction obtained at 3 post-operative months, pre- and post-operative knee injury and osteoarthritis outcome score (KOOS) value at 3 and 12 months, and differences between the two groups in terms of the correction obtained.
Results:
Radiation exposure in the '3D-guide' group was significantly different (8 [±4.51], p < 0.05), whereas surgical time was not significantly different between the control and guide 3D groups (60.69 [±8.89] and 53.43 [±11.69], respectively). At the 3-month follow-up, the post-operative hip-knee-ankle and post-operative mechanical-proximal-tibial angle were not significantly different (p > 0.05). At 3- and 12-month post-surgery, the Knee Injury and Osteoarthritis Outcome Score (KOOS) did not significantly differ between the conventional technique and the 3D-guide technique (p > 0.05). The KOOS at 3 months were 87.86 (±5.64) for the control group and 88.46 (±3.53) for the 3D-guide group, while at 12 months they were 91.5 (±5.72) for the control group and 88.57 (±8.81) for the 3D-guide group.
Conclusion:
Customized 3D-printed guides do not permit better correction or functional results than the conventional technique; rather, they reduce surgical time and intraoperative radiation exposure.
Level Of Evidence:
II.