Related Experiment Video
Updated: Jun 12, 2025
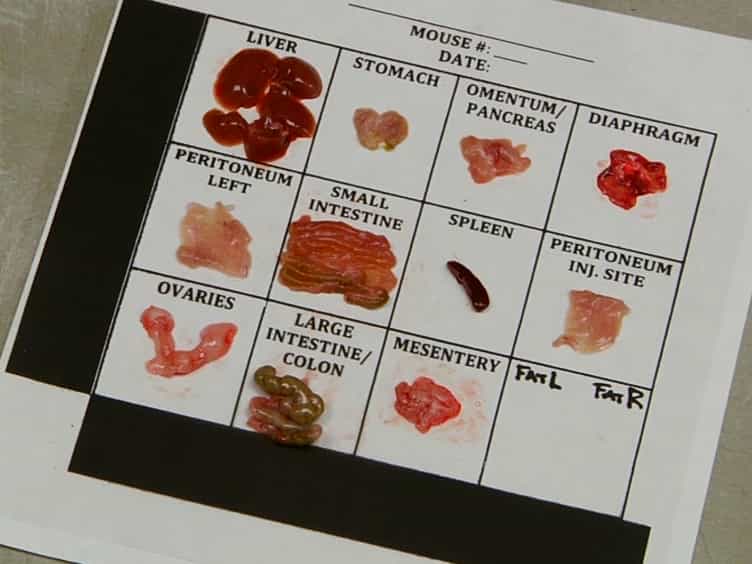

Quantitation of Intra-peritoneal Ovarian Cancer Metastasis
Published on: July 18, 2016
Neoadjuvant Chemotherapy for Newly Diagnosed, Advanced Ovarian Cancer: ASCO Guideline Update
Stéphanie Gaillard1, Christina Lacchetti2, Deborah K Armstrong1
1Johns Hopkins University, Baltimore, MD.

Purpose:
To provide updated guidance regarding neoadjuvant chemotherapy (NACT) and primary cytoreductive surgery (PCS) among patients with stage III-IV epithelial ovarian, fallopian tube, or primary peritoneal cancer (epithelial ovarian cancer [EOC]).
Methods:
A multidisciplinary Expert Panel convened and updated the systematic review.
Results:
Sixty-one studies form the evidence base.
Recommendations:
Patients with suspected stage III-IV EOC should be evaluated by a gynecologic oncologist, with cancer antigen 125, computed tomography of the abdomen and pelvis, and chest imaging included. All patients with EOC should be offered germline genetic and somatic testing at diagnosis. For patients with newly diagnosed advanced EOC who are fit for surgery and have a high likelihood of achieving complete cytoreduction, PCS is recommended. For patients fit for PCS but deemed unlikely to have complete cytoreduction, NACT is recommended. Patients with newly diagnosed advanced EOC and a high perioperative risk profile should receive NACT. Before NACT, patients should have histologic confirmation of invasive ovarian cancer. For NACT, a platinum-taxane doublet is recommended. Interval cytoreductive surgery (ICS) should be performed after ≤four cycles of NACT for patients with a response to chemotherapy or stable disease. For patients with stage III disease, good performance status, and adequate renal function treated with NACT, hyperthermic intraperitoneal chemotherapy may be offered during ICS. After ICS, chemotherapy should continue to complete a six-cycle treatment plan with the optional addition of bevacizumab. Patients with EOC should be offered US Food and Drug Administration-approved maintenance treatments. Patients with progressive disease on NACT should have diagnosis reconfirmed via tissue biopsy. Patients without previous comprehensive genetic or molecular profiling should be offered testing. Treatment options include alternative chemotherapy regimens, clinical trials, and/or initiation of end-of-life care.Additional information is available at www.asco.org/gynecologic-cancer-guidelines.This guideline has been endorsed by the Society of Gynecologic Oncology.
More Related Videos

Related Concept Videos
 02:56
Treatment Resistant Cancers
 01:27
Chemotherapy-Induced Nausea and Vomiting: 5-HT3 Receptor Antagonists
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
 01:28
Chemotherapy-Induced Nausea and Vomiting: Neurokinin-1 Receptor Antagonists
 01:29
Chemotherapy-Induced Nausea and Vomiting: Dopamine Receptor Antagonists
Phenothiazines, such as prochlorperazine...
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against...