Related Experiment Video
Updated: Aug 19, 2026


Endoscopic Ultrasound-Guided Biliary Drainage: Endoscopic Ultrasound-Guided Hepaticogastrostomy in Malignant Biliary Obstruction
Published on: March 25, 2022
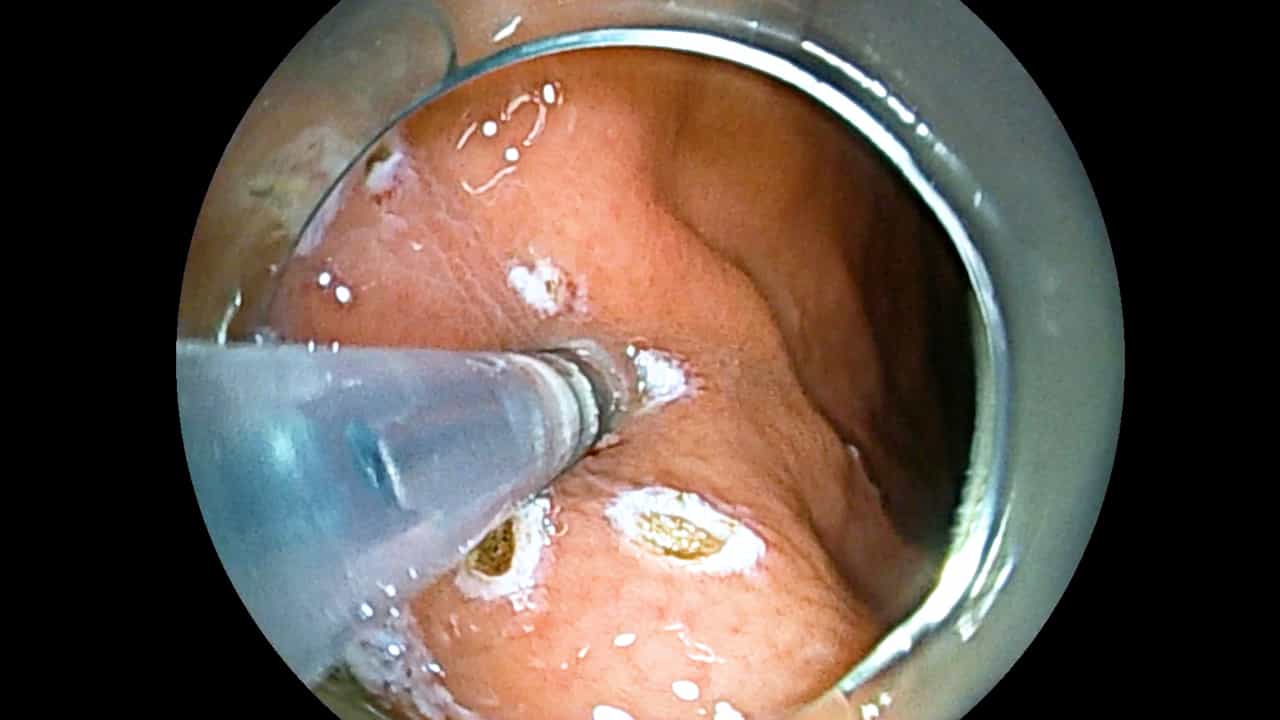
Endoscopic electrocoagulation of major bleeding from peptic ulcer

Abstract:
Endoscopic electrocoagulation with a liquid monopolar probe was exclusively attempted in 77 patients with major bleeding from peptic ulcer assessed as requiring emergency surgery. Endoscopy failed to control bleeding in 14 patients (18%), who proceeded directly to surgery. Initial endoscopic hemostasis was obtained in 63 patients, but hemorrhage recurred in 18 (29%). Rebleeding required surgery in 11 patients and another patient died prior to surgery. Permanent endoscopic control was achieved in 51 patients (66%). Without difference in transfusion requirement, endoscopy was most likely to succeed in patients with superficial acute ulcer, onset of bleeding in hospital, gastric ulcer, no earlier history of dyspepsia and in patients with previous ulcer surgery. Endoscopy was less likely to succeed in patients with chronic duodenal ulcer or earlier dyspepsia, though it controlled major bleeding in more than half of such patients. Profuse bleeding, and in particular poor access in a narrowed duodenal bulb, were important determinants of endoscopic failure. Of the patients with permanent endoscopic hemostasis, 8% subsequently underwent elective ulcer surgery. Endoscopic electrocoagulation is safe and has potential to control major bleeding, obviating emergency surgery, in two-thirds of the cases. As the less invasive method, endoscopy should be attempted before surgery, particularly in patients regarded as poor surgical risks or with no history of dyspepsia.

Related Concept Videos
 01:20
Drugs for Peptic Ulcer Disease: Prostaglandin Analogs as Mucosal Protective Agents
Non-steroidal anti-inflammatory drugs (NSAIDs) can induce peptic ulcers by inhibiting cyclooxygenase, decreasing...
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Peptic Ulcer Disease IV: Management
The therapeutic approach involves ensuring adequate rest, implementing drug therapy, promoting smoking cessation, making dietary modifications, and emphasizing long-term follow-up care.
Pharmacological management
The prevailing therapy for peptic ulcers involves a combination of managing the patient's current medication...
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:27
Peptic Ulcer