Related Experiment Video
Updated: May 1, 2026
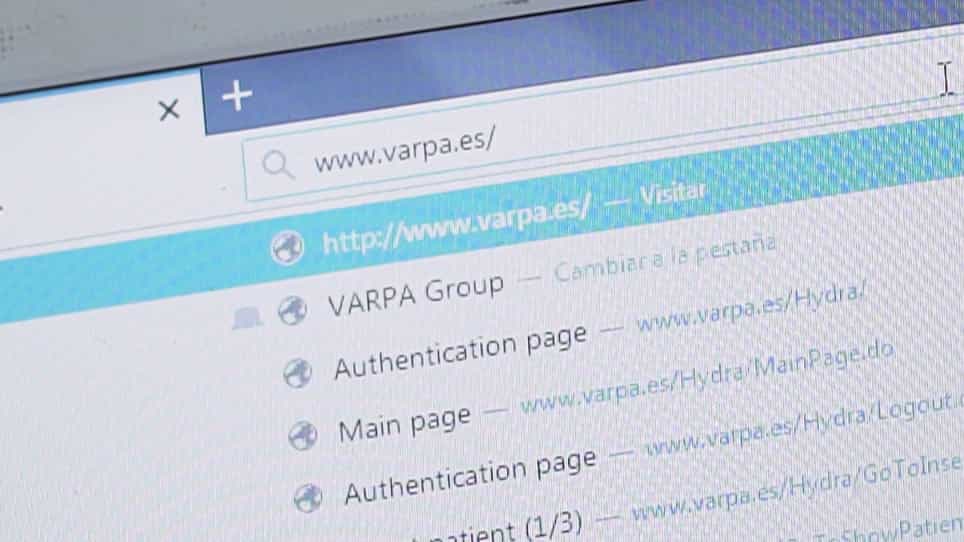

Hydra, a Computer-Based Platform for Aiding Clinicians in Cardiovascular Analysis and Diagnosis
Published on: September 26, 2018
Efficacy of a Clinical Decision Support Tool to Promote Guideline-Concordant Evaluations in Patients With High-Risk
Richard S Matulewicz1, Sarah Tsuruo2, William C King2
1Department of Surgery, Urology Service, Memorial Sloan Kettering Cancer Center, New York, New York.

Purpose:
We aimed to determine whether implementation of a clinical decision support (CDS) tool integrated into the electronic health record of a multisite academic medical center increased the proportion of patients with AUA "high-risk" microscopic hematuria (MH) who receive guideline-concordant evaluations.
Materials And Methods:
We conducted a 2-arm cluster randomized quality improvement project in which 202 ambulatory sites from a large health system were randomized to either have their physicians receive at time of test results an automated CDS alert for patients with high-risk MH with associated recommendations for imaging and cystoscopy (intervention) or usual care (control). Primary outcome was met if a patient underwent both imaging and cystoscopy within 180 days from MH result. Secondary outcomes assessed individual completion of imaging, cystoscopy, or placement of imaging orders.
Results:
There were 917 patients randomized to intervention (n = 476) or control (n = 441) arms between October and December 2021. The percentage of eligible patients for whom the alert correctly triggered in the intervention arm was 83%. Primary outcome was achieved in 0.6% vs 0.9% (relative risk 0.69; 95% CI 0.15, 3.10) of patients in the intervention and control arms, respectively. Patients in the intervention and control groups had similar rates of completed imaging (17.7% vs 14.7%) and cystoscopy (1.5% vs 0.9%). Those in the intervention arm had a higher likelihood of CT urogram order (5.5% vs 1.1%, P = .003) and a nonsignificant increase in urology evaluation (11.1% vs 7.5%, P = .09).
Conclusions:
Implementing an electronic health record-integrated CDS tool to promote evaluation of patients with high-risk MH did not lead to improvements in patient completion of a full guideline-concordant evaluation. The development of an algorithm to trigger a CDS alert was demonstrated to be feasible and effective. Further multilevel assessment of barriers to evaluation is necessary to continue to improve the approach to evaluating high-risk patients with MH.

Related Concept Videos
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:23
Types of Biopharmaceutical Studies: Controlled and Non-Controlled Approaches
Non-controlled studies, commonly employed for initial exploration, lack a control group, rendering them susceptible to biases and external influences. In contrast,...
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:12
Hazard Ratio
For example, in a clinical trial...