Chronic Hand Ischemia in Pediatric Patients Due to Brachial Artery Injury After Supracondylar Humerus Fracture
Dino Papes1, Stanko Ćavar1, Ivan Jelčić1
1Department of Surgery, University Hospital Centre Zagreb, Zagreb, Croatia.

Insights
Brachial artery reconstruction is safe and effective for children with supracondylar fractures and pulseless hands, preventing long-term ischemia. Early revascularization is crucial for all patients with persistent absent radial pulses.
Area of Science:
- Pediatric Orthopedics
- Vascular Surgery
- Trauma Surgery
Background:
- Supracondylar humerus fractures in children can cause brachial artery injury, leading to pink pulseless hand or acute ischemia.
- Long-term consequences of untreated brachial artery injury, like claudication and contracture, are poorly documented.
Purpose of the Study:
- To evaluate the long-term outcomes of brachial artery injury in children treated for supracondylar humerus fractures.
Main Methods:
- Retrospective review of 10 pediatric patients (3-10 years) with supracondylar fracture and brachial artery injury from 2010-2022.
- Analysis of functional outcomes, brachial artery patency, and complications after surgical exploration and/or revascularization.
Main Results:
- All 10 patients underwent brachial artery exploration; 6 immediately after fracture fixation, 2 after 48 hours, and 2 developed late ischemia requiring revascularization.
- Mean follow-up was 3.5 years. No postoperative complications occurred.
- All patients achieved a palpable radial pulse and patent brachial artery with no ischemic contractures at final follow-up.
Conclusions:
- Brachial artery reconstruction following supracondylar fracture is a safe procedure with excellent long-term patency.
- Prompt revascularization in all cases of persistently absent radial pulse is recommended to prevent chronic hand and forearm ischemia.
Objectives:
Brachial artery injury due to displaced supracondylar fracture (SC) of the humerus in children may present with pink pulseless hand (PPH), denoting a well perfused hand without radial pulse, or acute hand ischemia. Some reports state that brachial artery reconstruction is not necessary in children with persisting PPH, but the reports on long-term consequences such as intermittent claudications, growth retardation and ischemic contracture in children with pulseless hand are scarce and often misinterpreted. The objective of our analysis was to assess the long-term outcomes of children with brachial artery injury associated with SC fracture.
Methods:
A retrospective review was performed and data on all children treated for SC fracture with brachial artery injury from 2010 to 2022 were collected. Functional outcomes, brachial artery patency and complications were analyzed.
Results:
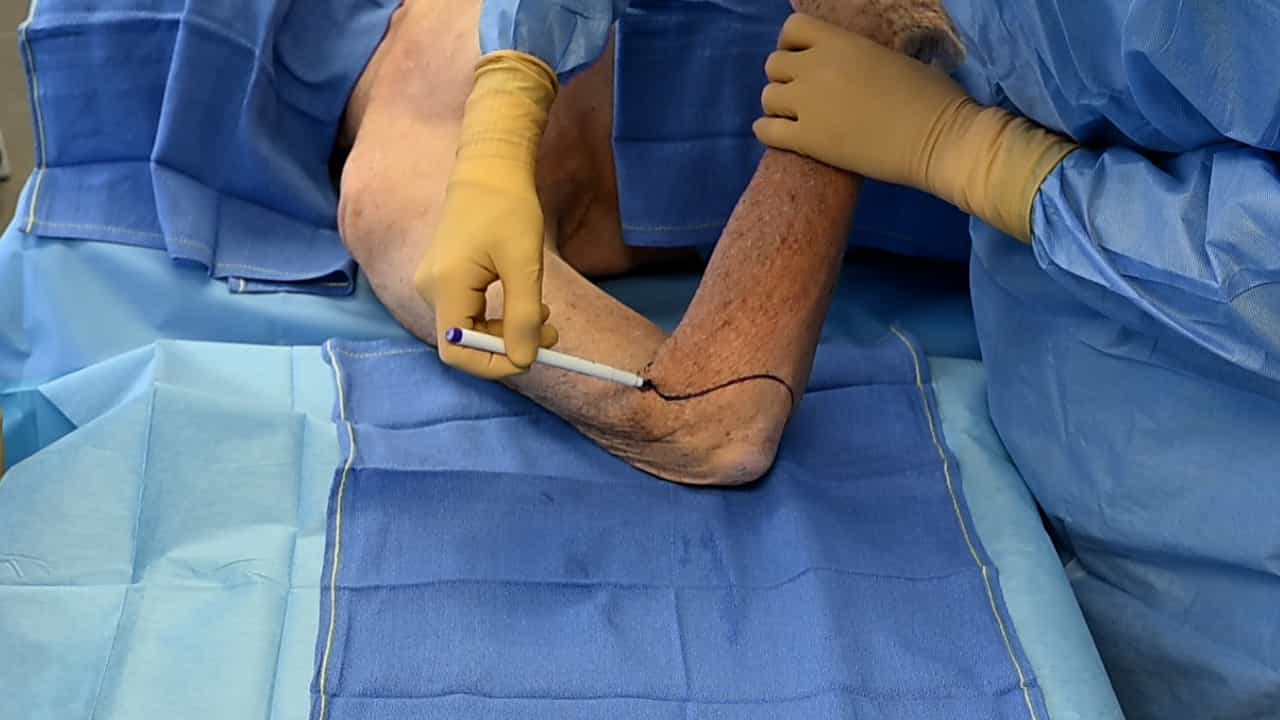
Overall, 10 patients with acute ischemia or PPH persisting after fracture reduction/fixation were identified, and all underwent brachial artery exploration (age range 3-10 years). Six patients underwent immediate exploration after fracture reduction and fixation: 3 due to signs of acute ischemia, and 3 for persisting PPH. Two patients underwent vascular surgery for PPH that persisted for more than 48 hr following fracture reduction. Two patients were discharged and later developed intermittent claudications/critical ishemia requiring revascularization. Mean follow up was 3.5 years (ranged 2-6 years). There were no postoperative complications. All patients had a palpable radial pulse, patent brachial artery on the last follow-up examination and no signs of ischemic contracture.
Conclusion:
Brachial artery reconstruction after SC fracture with brachial artery injury is a safe procedure that offers excellent long-term patency. Revascularization should be done in all patients with persistently absent radial pulse to avoid chronic hand and forearm ischemia.