Related Experiment Video
Updated: May 30, 2025

Author Spotlight: Advancing Hepatobiliary and Pancreatic Tumor Treatment with Minimally Invasive Surgical Techniques
Published on: September 27, 2024
Rethinking Right Upper Quadrant (RUQ) Pain: The Role of Lemmel Syndrome in Biliary Obstruction
Karan Yagnik1, Sai Gaddameedi1, Jayasree Ravilla1
1Internal Medicine, Monmouth Medical Center, Long Branch, USA.

Abstract:
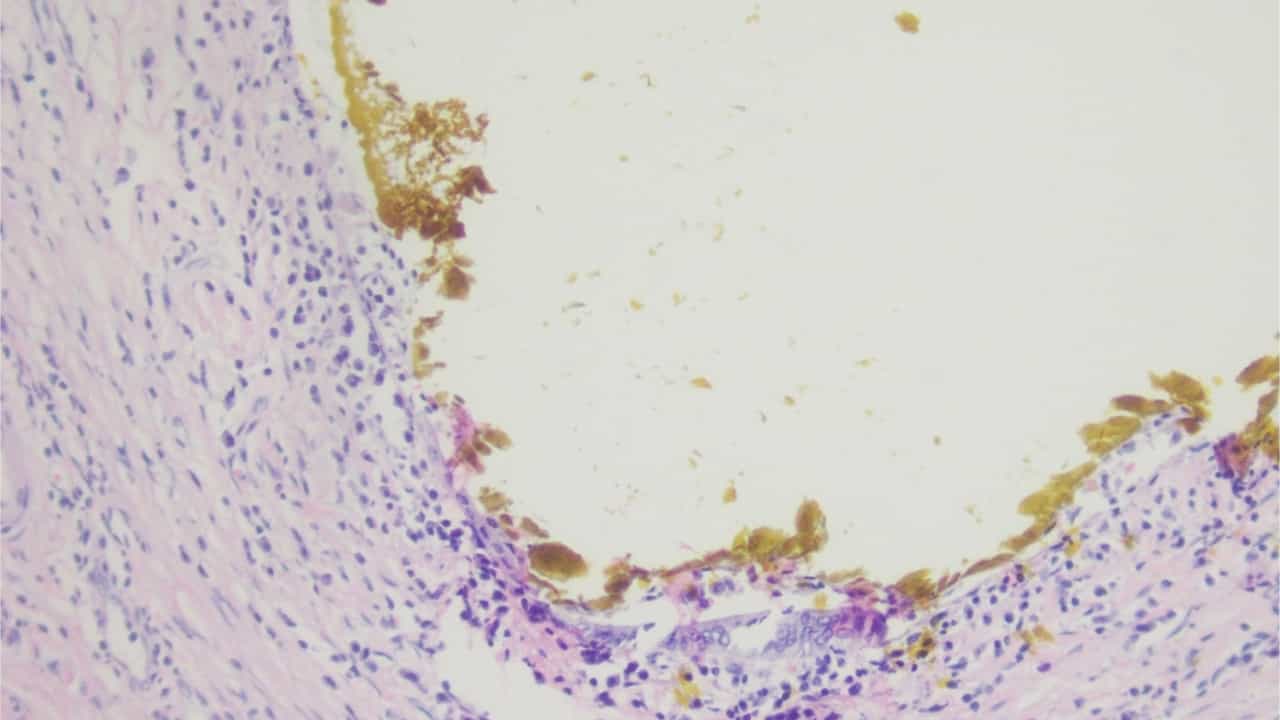
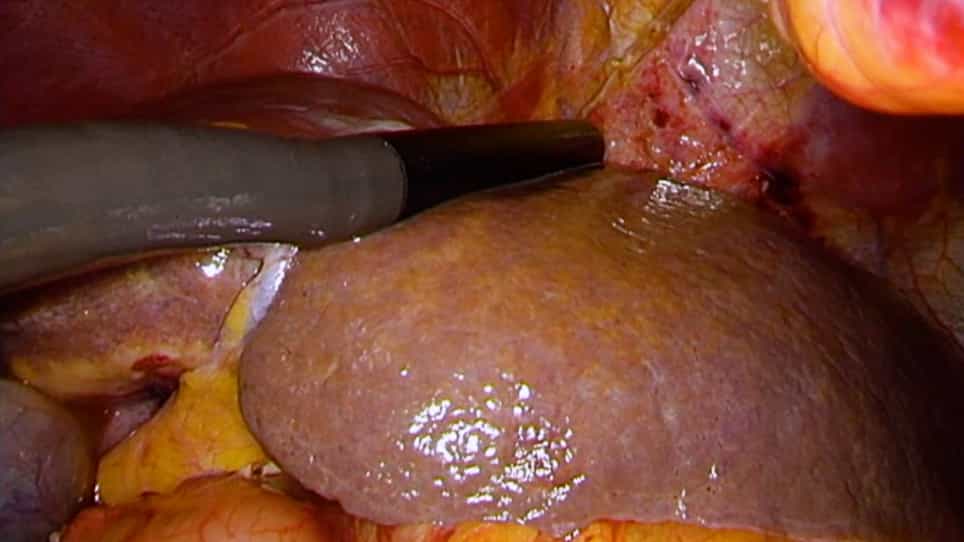
Lemmel syndrome involves a periampullary duodenal diverticulum (PAD), a pouch-like outpouching near the ampulla of Vater, compressing the common bile duct. We describe a case of severe abdominal pain in a patient who had a large periampullary diverticulum, managed with surgical intervention after an initial failed endoscopic retrograde cholangiopancreatography (ERCP). An elderly female patient in her early 90s arrived at the emergency department with severe cramping pain localized to the right upper quadrant of her abdomen, progressively intensifying over several weeks. Her blood pressure measured 161/68 mmHg, while other vital signs and the physical exam showed no abnormalities. A CT scan of the chest, abdomen, and pelvis with IV contrast revealed both biliary and pancreatic duct dilation, along with choledocholithiasis and a possible obstructing lesion at the pancreatic head. Further imaging with MRI and MRCP confirmed choledocholithiasis, dilation of the common bile duct (CBD), and the presence of a duodenal diverticulum. The initial attempt at endoscopic retrograde cholangiopancreatography (ERCP) was unsuccessful due to a large periampullary diverticulum, leading to the placement of a temporary percutaneous cholecystostomy tube. In a subsequent ERCP, the stones were successfully removed. During the same hospital stay, she underwent cholecystectomy and was later discharged. Patients experiencing right upper quadrant (RUQ) pain should consider Lemmel syndrome as one of the differential diagnoses. Although rare, it is a treatable condition that, if overlooked, can result in repeated hospitalizations and ongoing investigations. The altered anatomy associated with this syndrome can complicate standard medical procedures, requiring physicians to adapt their approach and utilize alternative methods.

Related Concept Videos
 01:22
Appendicitis-I: Introduction
Etiology: Appendicitis can arise from various causes, primarily rooted in the obstruction of the appendix lumen. Factors contributing to this obstruction include fecal accumulation, lymphoid hyperplasia and, in...
 01:19
Abdominal Regions and Quadrants
The simpler quadrants approach, which is more commonly used in medicine, subdivides the cavity with one horizontal and one vertical line that intersects at the patient's umbilicus (navel). The four...
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:17
Chronic Bowel Disorders: Introduction
Irritable Bowel Syndrome (IBS) is a common disorder affecting the gastrointestinal tract. The distinctive feature is recurrent abdominal pain associated with altered bowel movements, manifesting as constipation, diarrhea, or fluctuating between both. The...