Related Experiment Video
Updated: Jul 8, 2026
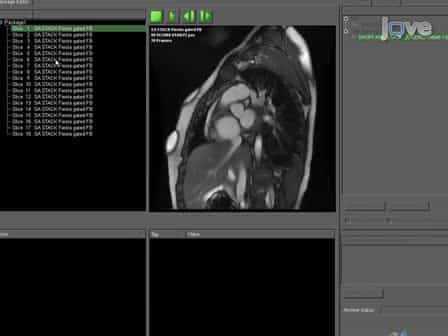
Magnetic Resonance Derived Myocardial Strain Assessment Using Feature Tracking
Published on: February 12, 2011
Utilization of Cardiac Magnetic Resonance Imaging for Assessing Myocardial Fibrosis in Prognosis Evaluation and Risk
Xin-Yi Feng1, Yu-Cong Zheng2, Ying-Xia Yang3
1Department of Radiology, Affiliated Hospital of North Sichuan Medical College, 637000 Nanchong, Sichuan, China.

Insights
Dilated cardiomyopathy involves impaired heart function, potentially leading to heart failure. Cardiac MRI techniques like T1 mapping can assess myocardial fibrosis, aiding in risk stratification for patients with this condition.
Area of Science:
- Cardiology
- Medical Imaging
- Pathology
Background:
- Dilated cardiomyopathy (DCM) is a severe heart condition characterized by impaired ventricular function.
- DCM can lead to heart failure, ventricular arrhythmia, and sudden cardiac death, often necessitating heart transplantation.
- Myocardial fibrosis, a key pathological feature, significantly contributes to adverse events in DCM.
Purpose of the Study:
- To comprehensively assess myocardial fibrosis in DCM.
- To evaluate the role of cardiac magnetic resonance imaging (CMR) in prognostic evaluation and risk stratification of DCM patients.
- To compare different CMR techniques for fibrosis detection.
Main Methods:
- Review of current literature on DCM and myocardial fibrosis.
- Analysis of cardiovascular magnetic resonance (CMR) techniques, including Late Gadolinium Enhancement (LGE), T1 mapping, and extracellular volume (ECV) fraction mapping.
- Comparison of CMR findings with pathological assessments of myocardial fibrosis.
Main Results:
- Late Gadolinium Enhancement (LGE) is the gold standard for replacement fibrosis but has limitations in detecting diffuse interstitial fibrosis.
- T1 mapping and ECV mapping show promise as complementary or alternative methods for interstitial fibrosis assessment.
- CMR imaging provides valuable prognostic information and aids in risk stratification for DCM patients.
Conclusions:
- Myocardial fibrosis is a critical determinant of outcomes in DCM.
- Advanced CMR techniques, beyond LGE, are essential for comprehensive fibrosis evaluation.
- CMR-based fibrosis assessment is crucial for guiding clinical management and risk stratification in DCM.
Abstract:
Dilated cardiomyopathy (DCM) is the ultimate manifestation of the myocardial response to various genetic and environmental changes and is characterized mainly by impaired left ventricular systolic and diastolic function. DCM can ultimately lead to heart failure, ventricular arrhythmia (VA), and sudden cardiac death (SCD), making it a primary indication for heart transplantation. With advancements in modern medicine, several novel techniques for evaluating myocardial involvement and disease severity from diverse perspectives have been developed. Myocardial fibrosis is a significant contributor to VA events and SCD. Based on different pathological mechanisms, myocardial fibrosis can be categorized into replacement and interstitial forms. Late gadolinium enhancement (LGE) derived from cardiovascular magnetic resonance is the clinical gold standard for evaluating replacement myocardial fibrosis and exhibits high concordance with histological replacement fibrosis. However, because of the absence of normal tissue as a control, the LGE technique often fails to effectively visualize diffuse interstitial fibrosis. In such cases, T1 mapping and extracellular volume fraction mapping can be complementary or alternative methods to the LGE technique for detecting interstitial fibrosis. This review aimed to provide a comprehensive and precise assessment of myocardial fibrosis and to determine the use of cardiac magnetic resonance imaging for prognostic evaluation and risk stratification of patients with DCM.
More Related Videos

Related Concept Videos
 01:21
Imaging Studies for Cardiovascular System IV: CMRI
 01:28
Imaging Studies for Cardiovascular System V: CT
 01:23
Mitral Stenosis II: Clinical features and Diagnostic Tests
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:29
Cardiomyopathy IV: Restrictive Cardiomyopathy