Related Experiment Video
Updated: May 30, 2025


Guidelines for Elective Pediatric Fiberoptic Intubation
Published on: January 17, 2011
Decoding airway granulogenesis in children: unveiling risk factors for tracheobronchial foreign body aspiration and
Yuting You1, Meili Shen2, Li'e Zeng1
1Children's Respiratory Department, Quanzhou Maternity and Children's Hospital, Quanzhou, Fujian, 362000, China.

Insights
Pediatric foreign body aspiration, often occurring in winter/spring, can cause airway granulomas. Time of impaction and oil release are key risk factors for granulation, necessitating prompt medical intervention and parental supervision.
Area of Science:
- Pediatric Pulmonology
- Otolaryngology
- Emergency Medicine
Background:
- Exogenous foreign body aspiration is a frequent, high-risk pediatric condition.
- Aspiration can lead to life-threatening airway granulomas complicating removal.
Purpose of the Study:
- To analyze clinical data of pediatric patients with tracheobronchial foreign bodies.
- To identify risk factors for airway granulation following foreign body aspiration.
Main Methods:
- Retrospective analysis of 184 pediatric patients (2018-2021).
- Inclusion criteria: exogenous tracheobronchial foreign bodies.
- Statistical modeling (logistic, XGBoost) to assess risk factors.
Main Results:
- Foreign bodies common in winter/spring; often nut-related, impacting the left lung.
- Complications include atelectasis, emphysema, and granulomatous tissue.
- Impaction time and oil release are significant risk factors for tracheal granulation (AUC up to 0.948).
Conclusions:
- Tracheobronchial foreign bodies predominantly affect males under 3, causing complications.
- Prolonged impaction time and oil release increase granulation risk.
- Prompt removal and increased child supervision are crucial to prevent complications.
Background:
Exogenous foreign body aspiration is a common high-risk condition in children. In a few cases, foreign body aspiration can lead to airway granulomas that interfere with tracheoscopic foreign body removal and threaten the life of the child.
Methods:
This study was a retrospective analysis of the clinical data of 184 pediatric patients who were admitted to Quanzhou Children's Hospital from 2018 to 2021 with exogenous tracheobronchial foreign bodies.
Results:
Respiratory foreign bodies tend to occur during the winter and spring seasons. The solid foreign bodies were mostly nut foreign bodies, the location of implantation was the left lung rather than the right lung in many patients, and complications such as pulmonary atelectasis, emphysema, mediastinal and subcutaneous emphysema, and granulomatous tissue formation were noted in these patients. Statistical models suggested that the time of foreign body impaction and the release of oil were risk factors for tracheal granulation, with the logistic model presenting an AUC of 0.948, precision of 0.676, and sensitivity of 0.895, whereas the XGBoost model presented an AUC of 0.902, precision of 0.912, and sensitivity of 0.875.
Conclusions:
Tracheobronchial foreign bodies primarily develop in male children under the age of 3 and often lead to various complications. The time of foreign body insertion and the release of oil from the obstructed foreign body have been identified as high-risk factors for the development of tracheobronchial granulation tissue. When the time of foreign body insertion without oil release exceeds 99.98 h or when the time of foreign body insertion with oil release exceeds 47.94 h, tracheobronchial granulation formation strongly suggests that the child is at high risk of developing airway granulation. In such cases, family members must implement increased supervision of the child to prevent choking. Medical professionals should obtain a detailed medical history of the affected child and accordingly select the most appropriate method to promptly remove the foreign body to resolve the issue of airway obstruction and reduce the likelihood of pulmonary complications in the child.

Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of...
 01:24
Asthma-III: Symptoms and Complications
Classification of Asthma
 01:29
Asthma-I: Introduction
 01:23
The Bronchial Tree
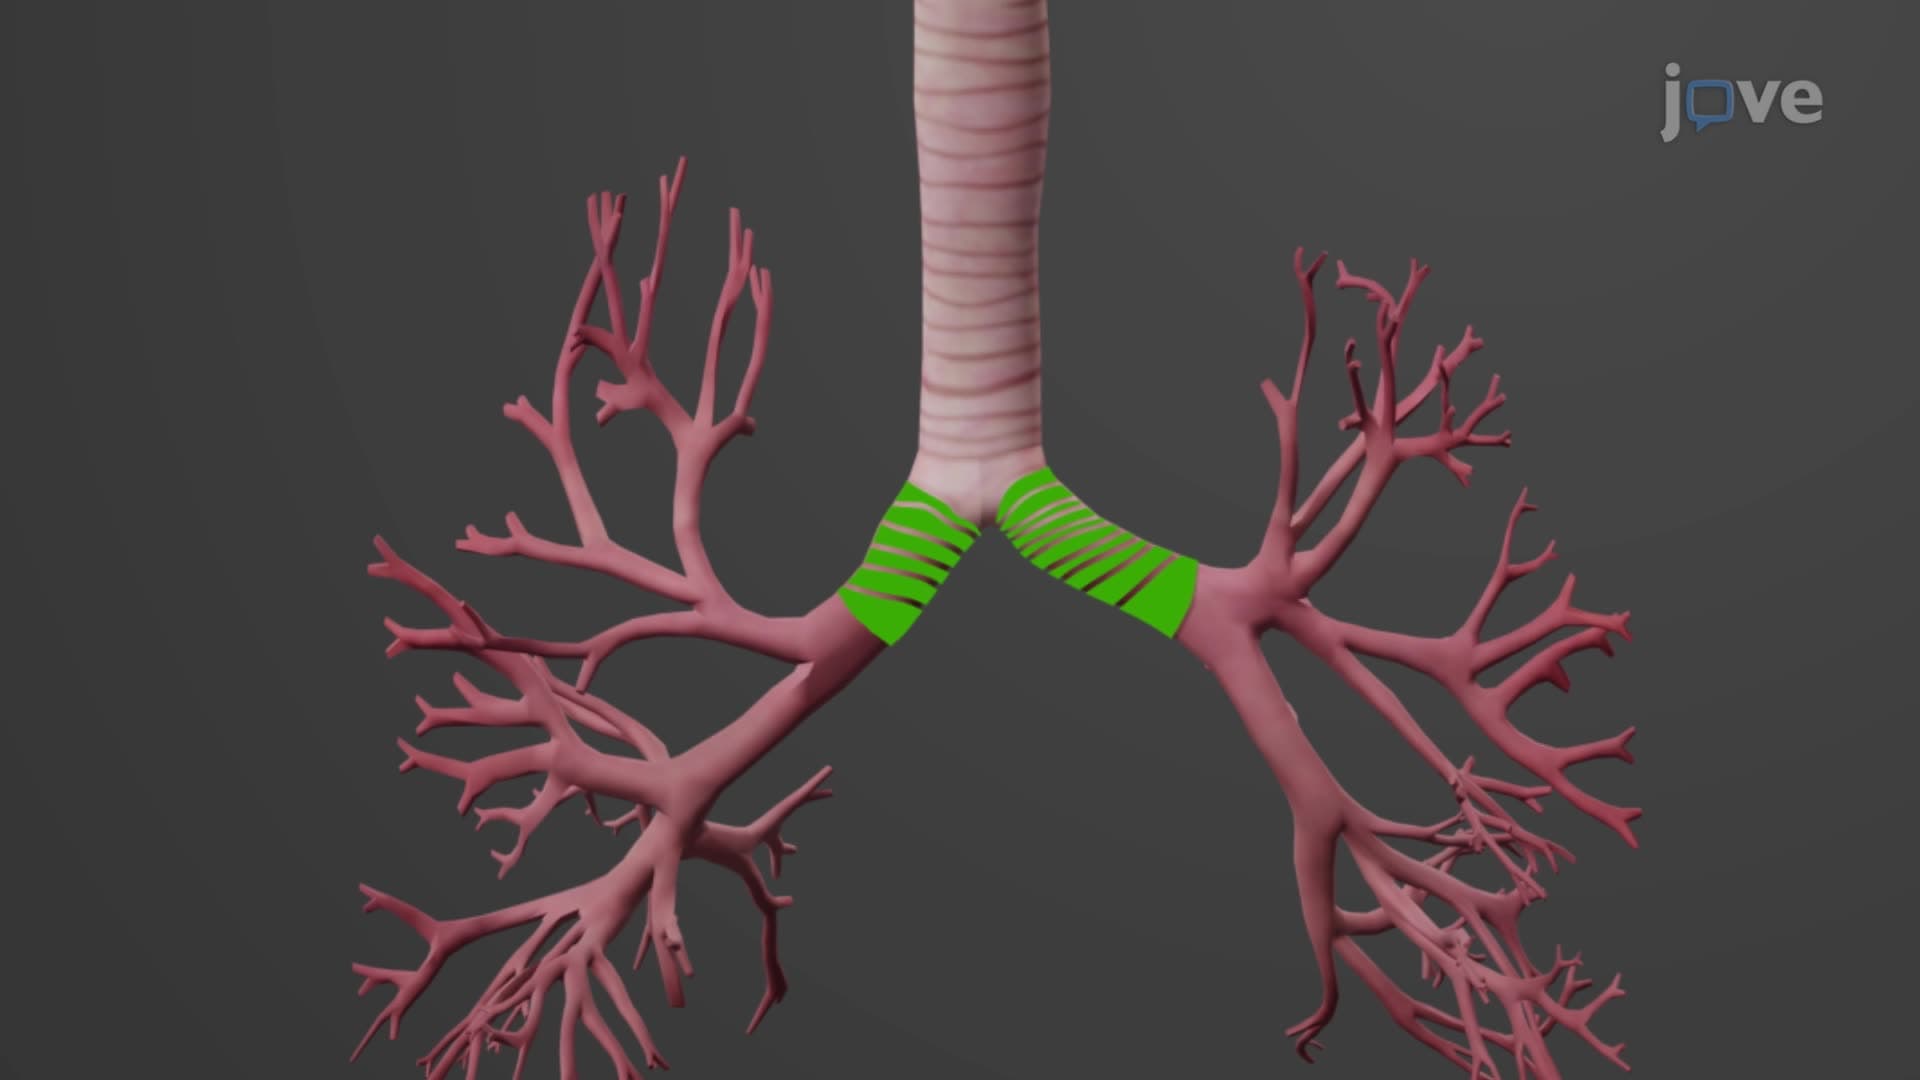
The trachea, commonly known as the windpipe, is a tube that connects the larynx (voice box) to the bronchi. At a point called the carina, it bifurcates into two primary bronchi. The right primary bronchus is wider, shorter, and more vertical than the left primary...
 01:17
Pulmonary Cycle: Exhalation
 01:20
Asthma: Pathogenesis and Management
Asthma is classified as allergic and non-allergic. Allergens such as dust mites, pollen, and pet dander trigger allergic asthma, while factors like cold air, intense emotions, or exercise can induce non-allergic asthma.