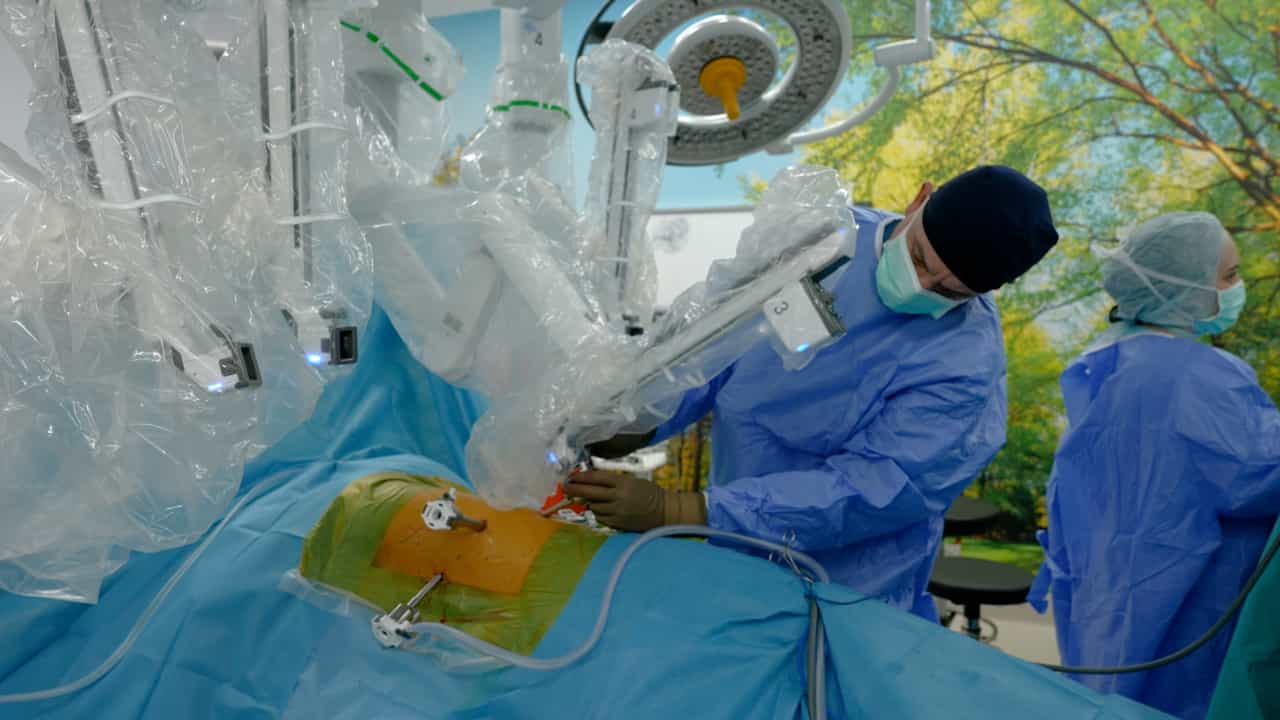
Long-term survival from a randomized controlled trial of lobectomy by video-assisted thoracoscopic surgery versus thoracotomy for early-stage lung cancer
Related Experiment Video
Updated: May 30, 2025

Author Spotlight: A Non-Intubated Video-Assisted Thoracoscopic Surgery with Multimodal Analgesia and Sevoflurane Inhalation Anesthesia
Published on: May 26, 2023
Finn Amundsen Dittberner1, Morten Bendixen1, Peter Bjørn Licht1
1Department of Cardiothoracic Surgery, Odense University Hospital, Odense, Denmark.

Objectives:
We previously did a randomized clinical trial of lobectomy by video-assisted thoracoscopic surgery (VATS) or thoracotomy for early-stage lung cancer and found that patients who underwent VATS had less postoperative pain and better quality of life compared with thoracotomy. VATS has since been regarded the preferred surgical method for early-stage lung cancer. It is assumed that long-term survival is not influenced by surgical approach, but this assumption primarily rests on non-randomized comparative studies. We decided to do a long-term follow-up of patients who entered our previous randomized trial.
Methods:
Between 2008 and 2014, we randomly assigned 206 patients to VATS (n = 103) or anterolateral thoracotomy (n = 103) for proven or suspected early-stage non-small-cell lung cancer (NSCLC). Records from patients with NSCLC on final pathology were identified in the national electronic patient-record system and the Danish Lung Cancer Registry. Overall, disease-free and cancer-specific survival (CSS) were estimated using the Kaplan-Meier method and log-rank test was used to compare the 2 interventions.
Results:
A total of 196 patients had NSCLC on final histopathology. Four patients were lost to follow-up and the remaining 192 were included in this follow-up study with 128 events used for overall survival analysis, 100 events for disease-free survival analysis and 79 events for CSS analysis. VATS was used in 99 patients versus 93 by thoracotomy. Median age at time of surgery was 66 years (range 41-85 years). After a median follow-up time of 12.8 years (range 9.9-15.8 years), 33% of patients were alive. Overall, disease-free and CSS were not significantly different between VATS and thoracotomy: overall survival (P = 0.29), disease-free survival (P = 0.17) and CSS (P = 0.31).
Conclusions:
We did not find any statistically significant differences in overall, disease-free or CSS between VATS and thoracotomy. However, larger trials with better power for survival analysis are needed to fully explore if there are differences. Alternatively, differences in survival between thoracotomy and VATS for early-stage NSCLC could be investigated by pooling survival data from 2 similar randomized trials that have since been published.