Related Experiment Video
Updated: May 30, 2025

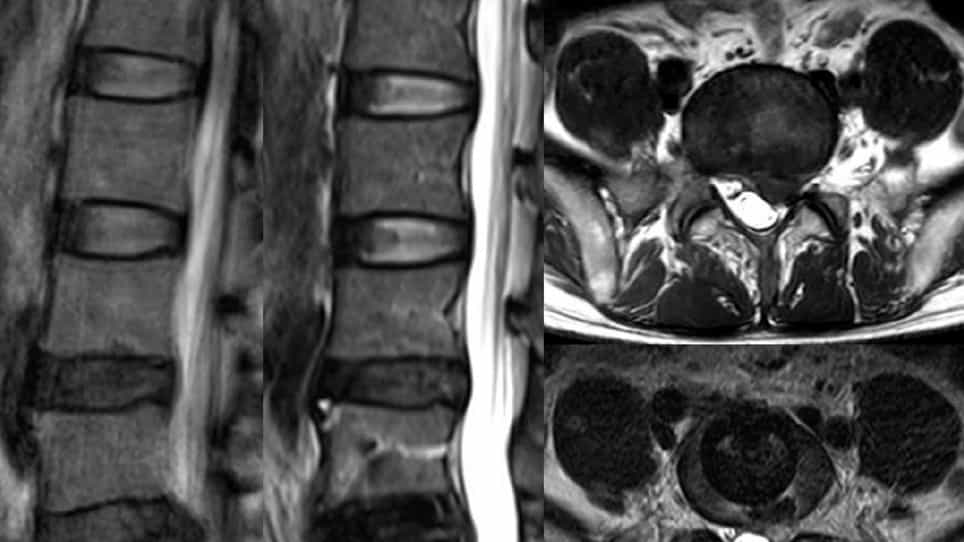
Author Spotlight: Scope of LE-ULBD as a Safe, Effective, and Minimally Invasive Approach to Treat Lumbar Spinal Stenosis
Published on: February 9, 2024
Previous surgery for lumbar spinal stenosis and association with amyloidosis and heart failure - A Danish nationwide
Navid Noory1, Eva Havers-Borgersen1, Adelina Yafasova1
1Department of Cardiology, Copenhagen, Denmark.

Insights
Lumbar spinal stenosis (LSS) surgery patients face a doubled risk of cardiac amyloidosis and increased heart failure risk. This highlights LSS as a potential early indicator for cardiac amyloidosis screening.
Area of Science:
- Cardiology
- Neurology
- Public Health
Background:
- Cardiac amyloidosis (CA) involves amyloid deposits leading to heart failure (HF).
- Lumbar spinal stenosis (LSS) is a potential, yet understudied, red flag for CA.
Purpose of the Study:
- To investigate the association between LSS surgery and the subsequent risk of CA and HF.
Main Methods:
- A nationwide Danish registry-based cohort study.
- Included 44,548 patients aged ≥60 years who underwent LSS surgery, matched 1:1 with controls.
- Adjusted for comorbidities like malignancy, hypertension, and liver disease.
Main Results:
- The 10-year cumulative incidence of amyloidosis was higher in the LSS group (0.16% vs. 0.08%, HR 2.29).
- The 10-year cumulative incidence of heart failure was also higher in LSS patients (10.1% vs. 7.5%).
Conclusions:
- LSS surgery is linked to a significantly increased risk of both cardiac amyloidosis and heart failure.
- Further prospective research is recommended to fully elucidate this association.
Introduction:
Cardiac Amyloidosis (CA) is characterised by amyloid fibril deposits causing heart failure (HF). Lumbar spinal stenosis (LSS) is recognised as a potential red flag for CA, but the association remains underexplored in large-scale studies.
Methods:
This nationwide registry-based cohort study in Denmark included subjects ≥60 years with a history of LSS surgery. LSS patients were matched 1:1 with controls by age, sex, ischaemic heart disease, chronic obstructive lung disease, chronic kidney disease, diabetes, and atrial fibrillation.
Results:
A total of 44,548 LSS surgery patients and matched controls were included (median age 71.5 years, 56.2% women). The cumulative incidence of amyloidosis after 10 years was higher in the LSS group (0.16% vs. 0.08%, HR 2.29 [95% CI 1.46-3.60]) after adjustment for malignancy, hypertension, and liver disease. The cumulative incidence of HF after 10 years was 10.1% in LSS patients compared with 7.5% in controls (HR 1.28 [95% CI 1.22-1.35], p < 0.0001).
Conclusions:
In this nationwide cohort study, LSS surgery was associated with a significantly higher risk of amyloidosis and HF. Prospective studies are warranted to explore the association further.