Related Experiment Video
Updated: May 29, 2025
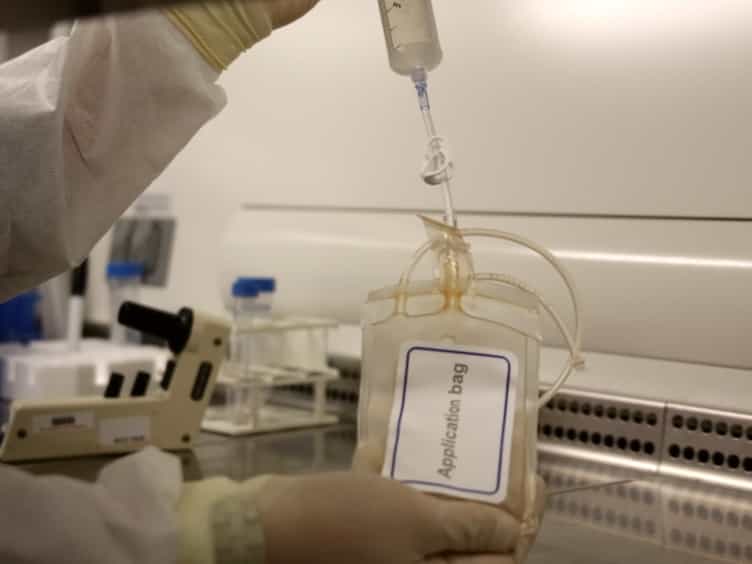

Automated Cell Enrichment of Cytomegalovirus-specific T cells for Clinical Applications using the Cytokine-capture System
Published on: October 5, 2015
CMV management of patients with leukopenia after CMV high-risk kidney transplantation
Amina Abu-Omar1, Janine Mihm2, Saskia Bronder3
1Department of Transplant and Infection Immunology, Saarland University, Homburg, Germany; Department of Internal Medicine IV, Saarland University, Homburg, Germany.

Background:
For CMV high-risk constellations, guidelines recommend 3-6 months of prophylaxis with valganciclovir (VGCV). Management in preventing CMV primary infection in patients developing VGCV-associated leukopenia remains challenging.
Methods:
We retrospectively analyzed the development of leukopenia during VGCV prophylaxis in 57 seronegative kidney recipients of a CMV-seropositive donor between 2008 and 2021. We analyzed CMV risk and development of CMV-specific T cells in the first post-transplant year depending on leukopenia during VGCV prophylaxis and management with CMV-IVIg.
Results:
Leukopenia developed in 19/57 patients, with a significant difference in leukocyte counts occurring after 10 weeks of VGCV prophylaxis compared to patients without leukopenia (p = 0.0003). VGCV discontinuation led to leukocyte reconstitution, which tended to be faster in patients receiving additional prophylaxis with CMV-IVIg after VGCV discontinuation (n = 11, p = 0.083). In the first post-transplant year, patients with leukopenia had no higher risk for severe CMV events. Interestingly, patients receiving CMV-IVIg prophylaxis showed a significantly lower peak CMV-load during primary infection (p = 0.040), with no difference in CMV-specific T-cell levels compared to patients without leukopenia or patients with additional CMV-IVIg prophylaxis (p = 0.972). Patients developing adequate CMV-specific T-cell responses less frequently underwent CMV reactivation 50 days following primary infection.
Conclusion:
Leukopenia developed late during VGCV prophylaxis and did not result in an increased risk for CMV primary infections or severe disease. Leukopenic patients receiving CMV-IVIg tended to have a faster leukocyte reconstitution and had lower peak DNAemia, which did not adversely affect CMV-specific T-cell induction. CMV-IVIg may therefore be considered as an alternative prophylactic strategy in patients with VGCV-associated leukopenia.
More Related Videos
 08:52
Generation of Multivirus-specific T Cells to Prevent/treat Viral Infections after Allogeneic Hematopoietic Stem Cell Transplant
Published on: May 27, 2011
 11:18
Expanding Cytotoxic T Lymphocytes from Umbilical Cord Blood that Target Cytomegalovirus, Epstein-Barr Virus, and Adenovirus
Published on: May 7, 2012
Related Concept Videos
 01:22
Bone Marrow Sampling and Transplants
The transplant begins with high doses of chemotherapy and radiation treatment, which aim to destroy...
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune...