Related Experiment Video
Updated: May 29, 2025
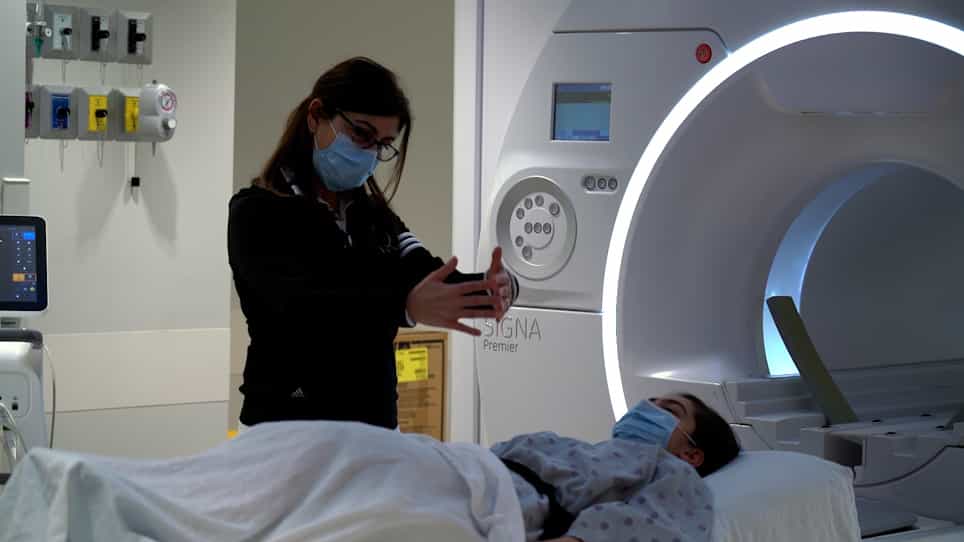
Oxygenation-sensitive Cardiac MRI with Vasoactive Breathing Maneuvers for the Non-invasive Assessment of Coronary Microvascular Dysfunction
Published on: August 17, 2022
Excess ventilation and chemosensitivity in patients with inefficient ventilation and chronic coronary syndrome or
Prisca Eser1, Dominic Käesermann1, Pietro Calamai1
1Centre for Rehabilitation & Sports Medicine, Inselspital, Bern University Hospital, University of Bern, Bern, Switzerland.

Background:
In patients with chronic coronary syndromes (CCS), increased ventilation/carbon dioxide production ( E/ CO2) slope has been found to predict disease progression and mortality, similarly to patients with heart failure (HF); however, increased chemosensitivity, a well-established predictor for mortality in patients with HF, has rarely been assessed in patients with CCS.
Method:
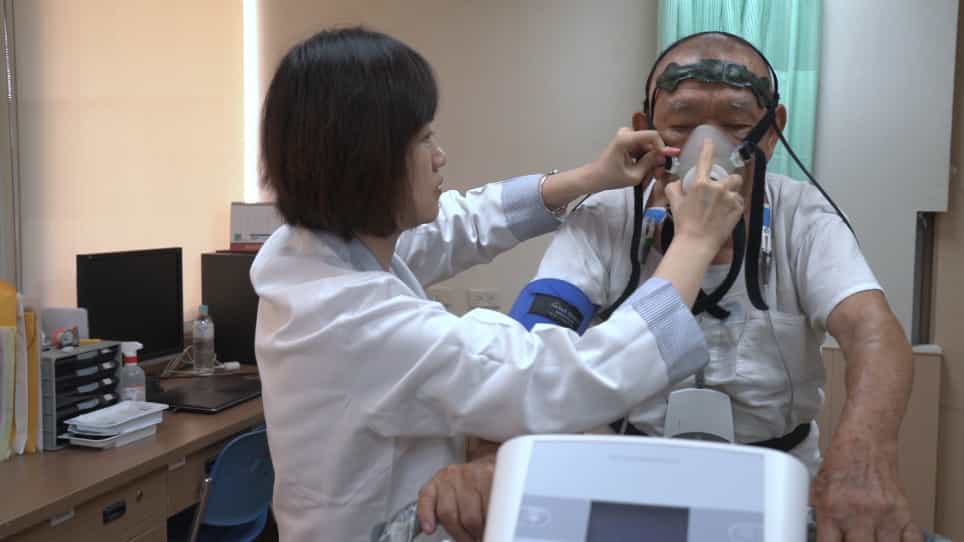
Patients with CCS, HF with reduced ejection fraction (EF < 50%), healthy controls (45+ years), and young healthy adults (<35 years) were recruited. For patients, a E/ CO2 slope ≥36 was an inclusion criterion. The Duffin rebreathing method was used to determine the resting end-expiratory partial pressure of carbon dioxide (PETCO2), ventilatory recruitment threshold (VRT), and slope (sensitivity) during a hyperoxic (150 mmHg O2) and hypoxic (50 mmHg O2) rebreathing test to determine the central and peripheral chemosensitivity.
Results:
In patients with CCS, HF, controls, and young healthy adults, median E/ CO2 slopes were 40.2, 41.3, 30.5, and 28.0, respectively. Both patient groups had similarly reduced hyperoxic VRT (at PETCO2 42.1 and 43.2 mmHg) compared to 46.0 and 48.8 mmHg in the control and young healthy adults. Neither hypoxic VRT nor hyper- or hypoxic slopes were significantly different in patients compared to controls. Both patient groups had lower resting PETCO2 than controls, but only patients with HF had increased breathing frequency and rapid shallow breathing at rest.
Conclusion:
In patients with HF and/or CCS and excess ventilation, central chemoreflex VRT was reduced independently of the presence of HF. Low VRTs were related to resting excess ventilation in patients with CCS or HF; however, rapid shallow breathing at peak exercise was present only in patients with HF.
Clinical Trial Registration Number:
NCT05057884.
Related Concept Videos
 01:26
Imbalances in Cardiac Output
CHF can occur due to the failure of either side of the heart. Left-side failure leads to pulmonary congestion—the right side continues to send...
 01:30
Acute Respiratory Failure-III
 01:25
Hyperpnea and Hyperventilation
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: