Related Experiment Video
Updated: Jul 17, 2026
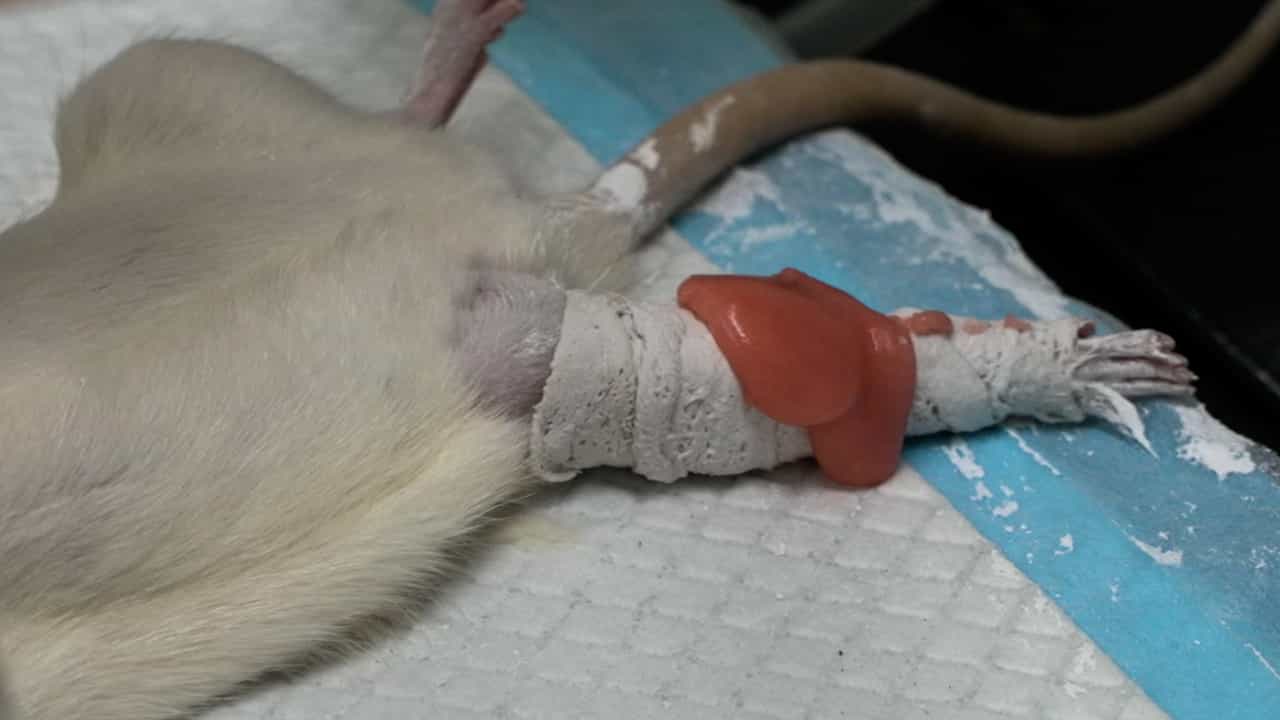

Tuina Manipulation to Reduce Inflammation and Cartilage Loss in Knee Osteoarthritis Rats
Published on: June 30, 2023
The eFEct of an Anti-Inflammatory Diet for Knee oSTeoarthritis (FEAST) Trial: Baseline Characteristics and
Lynette Law1, Joshua J Heerey1, Brooke L Devlin2
1La Trobe Sport and Exercise Medicine Research Centre, School of Allied Health, Human Services and Sport, La Trobe University, Bundoora, Australia.

Objective:
This study aims to: (i) describe the results of recruitment into the eFfEct of an Anti-inflammatory diet for knee oSTeoarthritis (FEAST) randomized controlled trial (RCT); (ii) report baseline characteristics of randomized participants and compare these with four large international cohorts; and (iii) explore cross-sectional associations between dietary inflammatory index (DII®) scores and baseline clinical characteristics.
Methods:
The FEAST RCT compares an anti-inflammatory dietary programme and standard care low-fat dietary programme for adults aged 45-85 years with knee osteoarthritis (OA). At baseline, participants provided medical history (medical comorbidities, symptomatic musculoskeletal sites), completed questionnaires (demographic characteristics, Knee injury and OA Outcome Score (KOOS)) and a 3-day food diary. Both DII® and energy-adjusted DII (E-DIITM) scores were calculated based on 3-day food diary data and was used to quantify the effect of diet on systemic inflammation. Associations between DII/E-DII and KOOS subscales, symptomatic musculoskeletal sites, and comorbidities was assessed using linear and negative binomial regression.
Results:
1121 individuals were screened to identify 182 eligible individuals, from which 144 participants (64% female, 36% male) enrolled, with a mean ± SD age 65 ± 8 years and body mass index 30.3 ± 6.2 kg/m2. Overweight (41%) and obesity (45%) was common. Two-thirds (62%) had ≥1 medical comorbidity, most commonly hypertension (26%). Musculoskeletal pain in sites other than the index knee was reported in 79%, most commonly in the lower back (42%). Mean DII and E-DII scores were 0.58 ± 1.49 and -0.31 ± 1.41, respectively. No associations were found between DII/E-DII and KOOS subscales except for activities of daily living (ADL), number of medical comorbidities and symptomatic MSK sites, and BMI.
Conclusion:
The FEAST cohort is comparable to other knee OA cohorts, supporting generalizability of the results. Despite a relatively pro-inflammatory diet at baseline, DII/E-DII was not associated with KOOS subscales, number of comorbidities or symptomatic musculoskeletal sites.

