

Short-acting urapidil compared to long-acting phenoxybenzamine in the management of pheochromocytoma
A Feld1, I Mintziras1, S Wächter1
1Department of Visceral, Thoracic and Vascular Surgery, Philipps-University Marburg, University Hospital Marburg, Baldingerstrasse, 35043, MarburgMarburg, Germany.

Purpose:
In patients with pheochromocytoma current guidelines recommend preoperative alpha-adrenoceptor blockade with selective or nonselective antagonists for at least 7-14 days. To date, no information exists about orally administered urapidil retard, a short-acting selective antagonist.
Methods:
The medical records of consecutive patients with pheochromocytoma between 2010 and 2023 were reviewed. Patients received phenoxybenzamine between 2010 and 2017, intravenous urapidil was given between 2017 and 2019. Orally administered urapidil retard has been used from 2019 until present.
Results:
Forty-nine patients with pheochromocytomas were included. Twenty-six patients received orally administered long-acting phenoxybenzamine and 23 patients were pretreated with short-acting intravenous (n = 8) or orally administered urapidil (n = 15). Treatment prior to surgery was significantly shorter with intravenously (3 days (IQR, 3-4), p = 0.015) or orally administered urapidil (2 days (IQR 2-3), p = 0.003) compared to phenoxybenzamine (7 days (IQR, 4-10)). Side effects were more often in the phenoxybenzamine group (17/26 vs 6/23, p = 0.02). The modified hemodynamic instability (HI) score was low and there was no significant difference between patients treated with phenoxybenzamine and those treated with intravenous or oral urapidil (29 (IQR 18.5-38); 26 (IQR 18-42); 31 (IQR 15-36) ns). No 30-day postoperative mortality or cardiovascular complications occurred in any of the three groups. The postoperative hospital stay was significantly shorter in the orally administered urapidil group compared to the phenoxybenzamine group (3 days (IQR 3-5)) vs 4 days (IQR 4-5)), p = 0.04).
Conclusion:
Oral pretreatment with urapidil retard is well tolerated for patients with pheochromocytoma, enabling a safe intra- and postoperative course.

Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:17
Adrenergic Antagonists: Chemistry and Classification of ɑ-Receptor Blockers
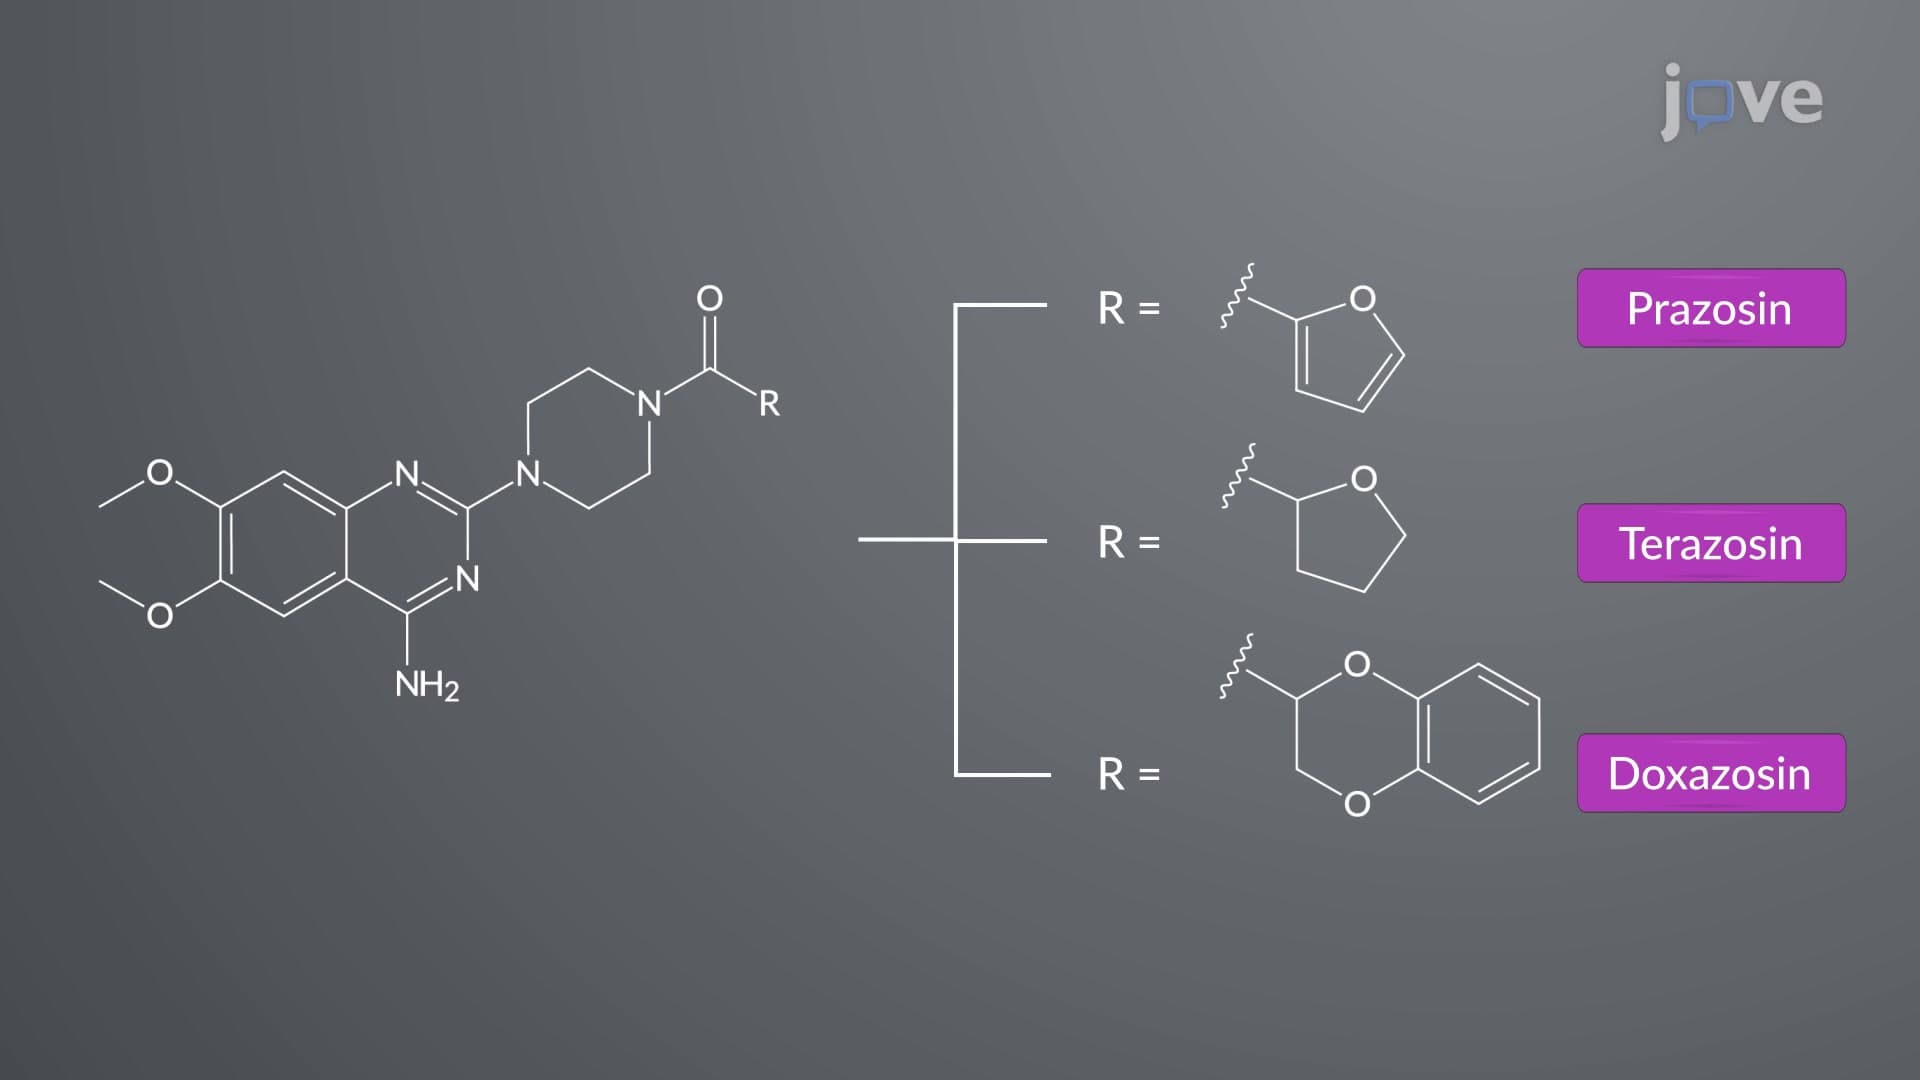
Nonselective α-blockers: Nonselective α-blockers contain haloalkylamine or imidazoline...
 01:28
Adrenergic Agonists: Mixed-Action Agents
Ephedrine and pseudoephedrine lack a catecholamine group, making them less susceptible to degradation by metabolic enzymes. They have increased oral bioavailability and lipophilicity, resulting in a longer duration of action. Their response is reduced by...
 01:30
Adrenergic Agonists: Direct-Acting Agents
These agents can be classified...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers