Related Experiment Video
Updated: May 28, 2025
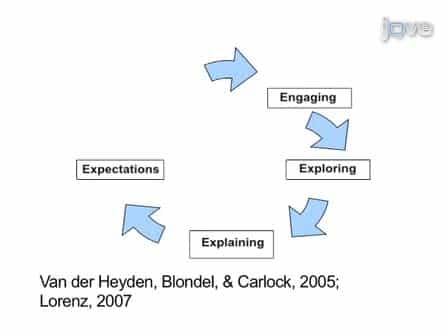

Using Visual and Narrative Methods to Achieve Fair Process in Clinical Care
Published on: February 16, 2011
Audit and group feedback in nursing home physician groups: lessons learned from a qualitative study
Gary Y C Yeung1,2, Charlotte A W Albers3,4,5, Martin Smalbrugge3,4
1Department of Medicine for Older People, Amsterdam UMC, Location Vrije Universiteit Amsterdam, Boelelaan 1117, Amsterdam, the Netherlands. g.y.yeung@amsterdamumc.nl.

Background:
Audit and group feedback (A&F) is an instrument used to encourage healthcare professionals to improve the quality of care. Clinical practice was audited against a set of criteria and fed back to a group by a facilitator. The aim of this study was to gain a better understanding of how physician group feedback sessions in nursing homes were conducted and to what extent they resulted in action planning.
Methods:
Fifteen group feedback sessions of the antibiotic A&F program within a nursing home network were audio-recorded, transcribed, and analyzed via the Framework Method for thematic analysis. The coding was performed using the existing Calgary A&F Framework and Cooke's conceptual model of physician behaviors, and open inductive codes were added.
Results:
Elements of the conceptual model and the Calgary A&F Framework occurred within all group feedback sessions. The relationships within the group and with the facilitators were important elements when moving a group from interpreting the results to formulating action plans. Physician groups responded positively to the audit data, particularly if they were among the best performing. The data were met with doubt by physicians who did not recognize their own practice. When exploring potential reasons for lower guideline adherence, groups often considered data quality or external factors such as the choice of non-adherent treatment by locum staff. The degree of reflection on personal factors as explanations for low adherence and the extent to which groups identified learning and improvement opportunities varied: some groups were able to formulate action plans to address data problems and knowledge gaps, whereas others scheduled a follow-up meeting to develop action plans for treatment or prescribing practice changes.
Conclusions:
The facilitator was crucial in supporting the group in interpreting the results, steering the conversation towards sharing change cues, and helping the physician group in developing action plans. The degree of reflection and action planning varied by group. By implementing the lessons learned from this study, group feedback sessions can be refined, supporting participants in action planning.
Related Concept Videos
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:15
Nursing Evaluation
 01:29
Nursing Assessment
The nurse collects all aspects of the patient's health in the initial assessment, establishing priorities for ongoing focused assessments...
 01:09
Accountability and Responsibility of a Nurse II
For example, a nurse demonstrating respect and compassion might listen attentively to a patient's concerns, provide...
 01:20
Nursing Process for Patient and Caregiver Teaching III: Evaluation and Documentation
Nurses can use several methods to evaluate patient outcomes. For example, oral questions can assess cognitive learning,...
 01:30
Accountability and Responsibility of a Nurse I