Highly cited scores, scoring systems, grading systems, and classifications of daily use in cranial neurosurgery: A must-have during residency training! A mini-review
Related Experiment Video
Updated: May 28, 2025

Setting Up a Stroke Team Algorithm and Conducting Simulation-based Training in the Emergency Department - A Practical Guide
Published on: January 15, 2017
1Neurosurgery department, Sainte-Anne Military Teaching Hospital, 2 boulevard Sainte-Anne, 83800 Toulon Cedex 9, France.

Context:
Neurosurgery has much evolved since the time of Kocher and Cushing. Thanks to operative microscope, radiation therapy, progress of neuroresuscitation care, and data from evidence-based neurosurgical research, neurosurgery patients' prognostic has improved. Now more than ever, we need simple, reliable, and reproducible scores, grades, and classifications to assist us in the surgical decision making, to assess patients' clinical evolution, and to conduct proper neurosurgical research.
Materials And Methods:
We conducted a three stage scoping review: (1) identification of sections of interest: brain trauma, tumor, vascular, infection, stroke, functional outcome (2) identification of the most common diseases within each section, (3) we retained every score, scale, classification that is internationally recognized and/or highly cited and/or used daily in clinical practice or research setting and/or that is currently used by the author.
Results:
23 scores were retained. Brain trauma section: Glasgow coma scale (1974), Glasgow Liège scale (1982), SHE score (2019), RASH score (2022). Tumor section: Karnofsky Performance status (1948), Graded Prognostic Assessment (2008), Simpson grade (1957), Sindou grade (2006), House and Brackmann (1983), Koos grade (1993), Knosp scale (1993). Vascular section: PHASES score (2014), UIATS score (2015), Hunt and Hess scale (1968), Fisher scale (1980), WFNS scale (1988), Spetzler Martin scale (1986), Borden scale (1995), Cognard scale (1995), Zabramski scale (1995). Stroke section: ICH score (2001), NIHSS (1989). Functional outcome section: Rankin scale (1957).
Conclusion:
We provide a non-exhaustive list of 23 reference scales, scores, and classifications that can be safely used for cranial neurosurgery clinical practice and research.
Related Concept Videos
 01:14
Brain Imaging
These technologies include computerized axial tomography (CAT or CT scans), positron-emission tomography (PET scans), magnetic resonance imaging (MRI), functional magnetic resonance imaging (fMRI), and Transcranial Magnetic...
 01:22
Sutures of the Skull
Sutures are immobile joints between adjacent bones of the skull. The narrow gap between the bones is filled with dense, fibrous connective tissue that unites the bones. The long sutures located between the skull bones are not straight but instead follow irregular, tightly twisting paths. These twisting lines tightly...
 01:14
Cranial Bones: Superior and Posterior View
The frontal bone is the single bone that forms the forehead. At its anterior midline, between the eyebrows, there is a slight depression called the glabella. The frontal bone also forms the supraorbital margin of the orbit. Near the middle of this margin is the supraorbital foramen, the opening that provides passage for a sensory nerve to the forehead. The frontal bone is thickened just above each supraorbital margin,...
 01:19
Cranial Nerves: Overview and Anatomy
 01:21
Cerebrospinal Fluid
CSF Production
CSF is produced mainly in the choroid plexus, a network of capillaries and ependymal cells located within the ventricular system of the brain....
 01:19
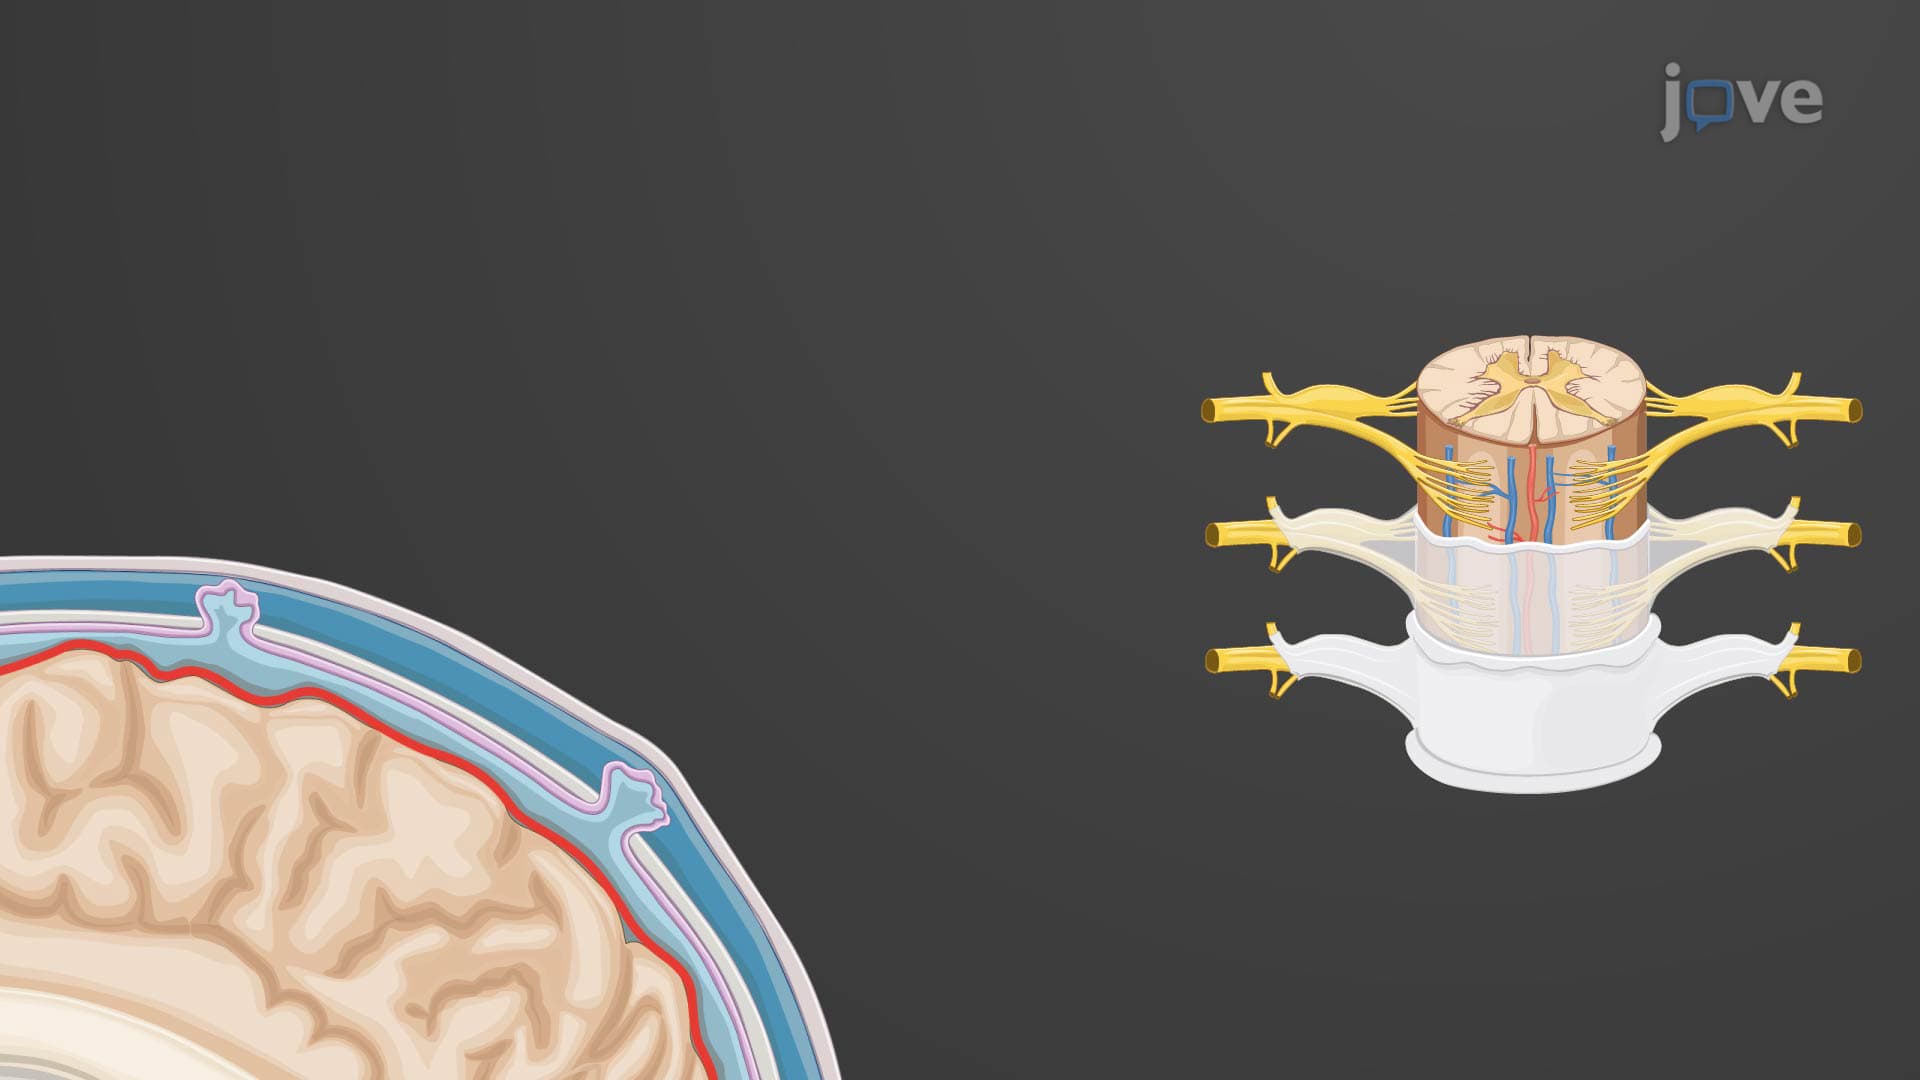
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...