Related Experiment Video
Updated: Jul 31, 2026

Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
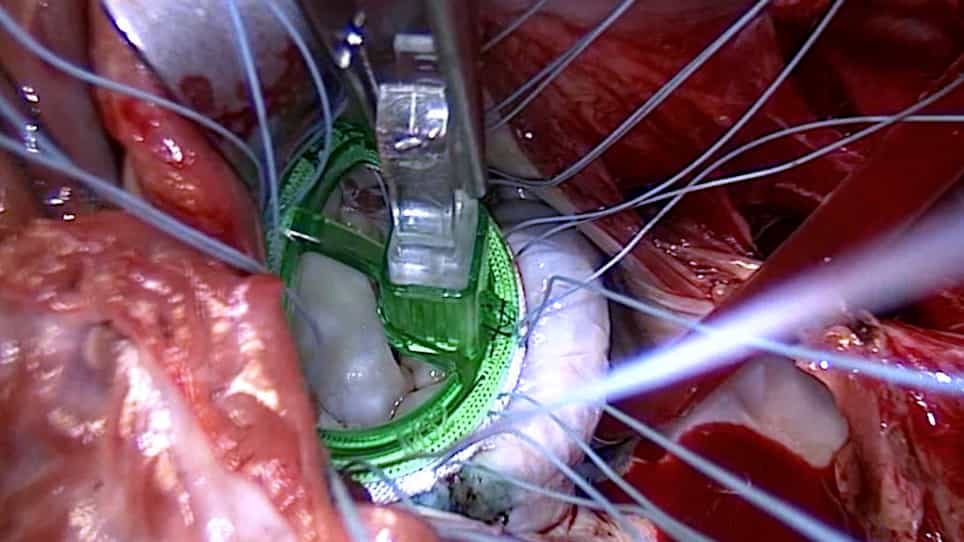
Enhanced Survival With Surgical Ablation of Atrial Fibrillation During Mitral Valve Surgery
John B Eisenga1, Kyle B McCullough1, Jasjit K Banwait1
1Department of Cardiovascular Research, Baylor Scott and White Research Institute, Plano, Texas.

Background:
Surgical ablation (SA) at the time of isolated mitral valve surgery (MVS) is recommended in patients with preexisting atrial fibrillation (AF). However, SA remains infrequently utilized during MVS with a poorly quantified impact on stroke and survival.
Methods:
Medicare claims (2008-2019) were queried to identify beneficiaries with preexisting AF undergoing MVS. All-cause mortality and the postoperative incidence of stroke/transient ischemic attack were evaluated as separate endpoints. Overlap propensity score weighting was used to risk-adjust for measured confounding variables. Analyses were repeated using surgeon frequency of SA as an instrumental variable to adjust for unmeasured confounding variables.
Results:
From 2008-2019, 41,795 Medicare beneficiaries with a preexisting diagnosis of AF underwent MVS. Surgeons were categorized, with 1326 infrequently (bottom quartile) performing SA (<30%; 10,364 beneficiaries) and 740 frequently (top quartile) performing SA (≥62%; 10,476 beneficiaries) during MVS. Beneficiaries undergoing MVS with SA ("as-treated" analysis) had a risk-adjusted median survival advantage of 0.56 (95% CI, 0.33-0.81) years (8.85 [95% CI, 8.64-9.04] vs 8.29 [95% CI, 8.11-8.47] years, P < .001 for risk-adjusted survival comparison) compared to those without. Beneficiaries undergoing MVS by frequent SA surgeons ("surgeon-preference" analysis) had a risk-adjusted median survival advantage of 0.35 (95% CI, 0.05-0.71) years (8.59 [95% CI, 8.40-8.85] vs 8.24 [95% CI, 7.97-8.40] years, P = .0015 for risk-adjusted survival comparison) compared to surgeons who infrequently performed SA.
Conclusions:
In Medicare beneficiaries with preexisting AF, concomitant SA during MVS is associated with improved survival, as is undergoing surgery by a frequent SA surgeon. When analyzed based on surgeon preference for SA, the magnitude and time-dependent nature of the treatment effect of SA were substantially different compared to the "as-treated" analysis, suggesting that "as-treated" analyses may be subject to bias from unmeasured confounding variables.
More Related Videos

Related Concept Videos
 01:29
Cardiomyopathy V: Interprofessional Care
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management