Related Experiment Video
Updated: May 27, 2025
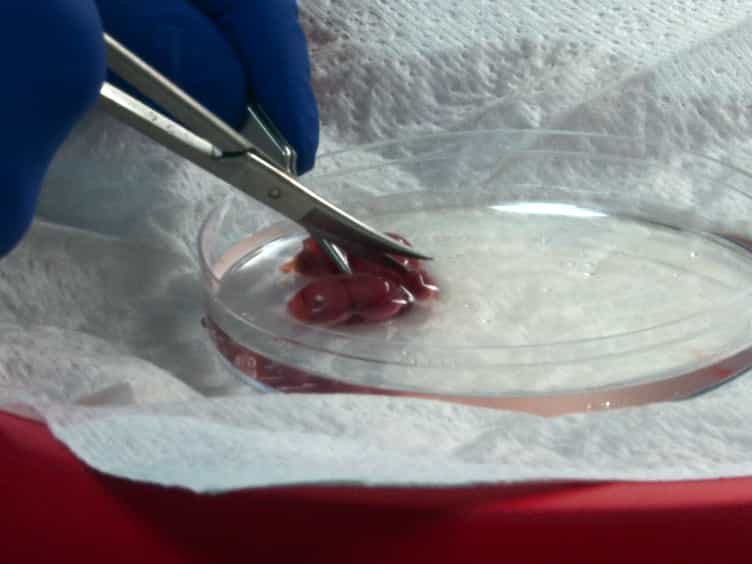
Method of Studying Palatal Fusion using Static Organ Culture
Published on: September 19, 2015
Barriers to timely primary cleft surgery in patients treated by an international cleft-focused NGO across 18
Alexander T Plonkowski1,2, Priyanka Naidu2,3, Greta L Davis2,4
1Division of Plastic and Maxillofacial Surgery, Children's Hospital Los Angeles, Los Angeles, California, USA.

Introduction:
Cleft lip and/or palate (CL ± P) constitutes a significant portion of the global surgical burden. Patients in low- and middle-income countries (LMICs) face disproportionate barriers that result in delayed surgical repair, worse long-term outcomes, and increased morbidity.
Objectives:
This study aimed to identify patient-reported barriers and demographic characteristics associated with delayed CL ± P surgery in LMICs where Operation Smile provides surgical care.
Methods:
A retrospective chart review of patients treated by Operation Smile between 2021 and 2024 was conducted. Variables included patient demographics, socioeconomic information, and self-reported barriers to care. Delayed repair was defined as greater than 9 months for cleft lip and 18 months for cleft palate. Data were analyzed using chi-squared and t-tests. Significant variables then underwent uni/multivariate logistic regression analysis.
Results:
Six hundred and sixty-eight patients were included, of which 339 (50.7%) underwent lip repair and 329 (49.3%) underwent palate repair. The most common patient-reported barrier was surgical cost (n = 561 and 84.0%). On multivariate regression, increased maternal age significantly increased odds of delayed surgery (OR = 1.03[1.003, 1.07] and p = 0.04) and maternal postsecondary education decreased odds among lip repair patients (OR = 0.22[0.05, 0.77] and p = 0.03). For palate repair, maternal age (OR = 1.05[1.01, 1.09] and p = 0.02) and surgical cost (OR = 2.85[1.42, 5.71] and p = 0.003) increased odds of delay, whereas paternal university-level education decreased odds (OR = 0.15[0.02, 0.81] and p = 0.04).
Conclusion:
Surgical cost is a primary barrier to timely CL ± P repair among patients in LMICs. Higher education among parents is associated with lower odds of delay. These barriers can inform global surgical organization strategies to improve access for patients at risk of delay.
Related Concept Videos
 01:21
Barriers to Effective Communication II
Cultural barriers:
Differences in values, beliefs, religion, knowledge, and tradition can significantly impact communication. Awareness of nonverbal cues is critical, especially when conversing with a patient from a different culture. What appears appropriate in one culture may be inappropriate in another.
Semantic barriers:
As a result of their tendency to use...
 01:30
Primary Healthcare Services
In 1978, international leaders convened in Alma-Ata, Kazakhstan, for what would be a pivotal event in global health. The Alma-Ata Declaration was the first to call...
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations: