Related Experiment Video
Updated: May 11, 2026
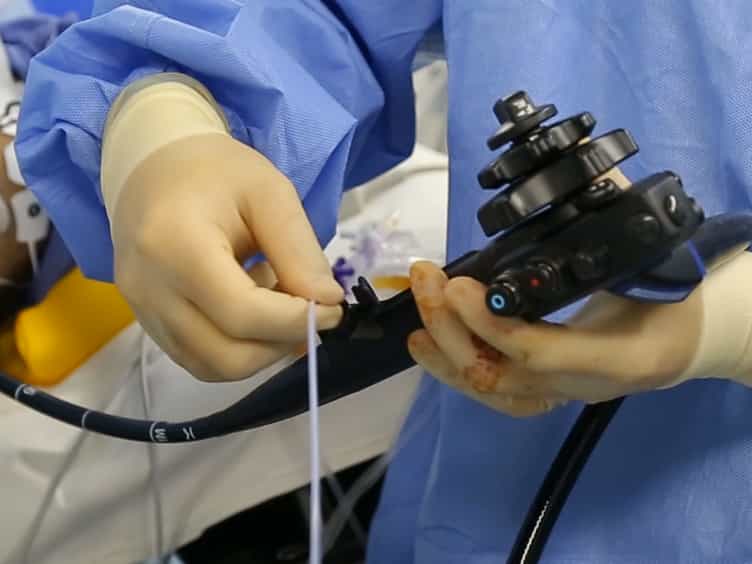
Intraoperative Gastroscopy for Tumor Localization in Laparoscopic Surgery for Gastric Adenocarcinoma
Published on: August 9, 2016
Well-differentiated Adenocarcinoma Arising from Gastric Cystica Profunda Treated by Endoscopic Submucosal Dissection:

Abstract:
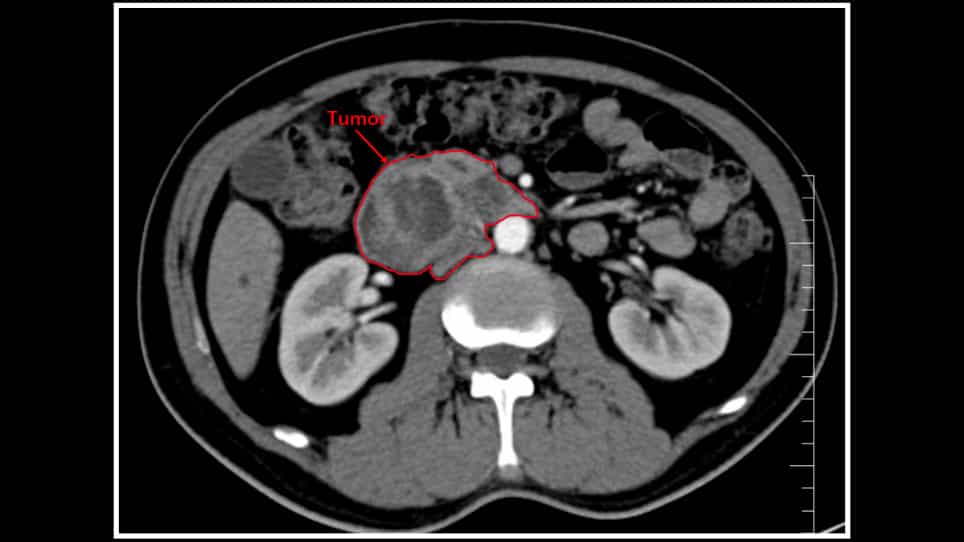
Gastritis cystica profunda (GCP) is a rare disease that is often observed at the stoma site of patients undergoing gastric surgery. Specific symptoms are often lacking, making it difficult to diagnose. GCP may develop into cancer. Endoscopic resection is a good method to reduce surgical injury, and the therapeutic effect depends on the status of the primary disease.The patient was a 77-year-old male who was admitted to the hospital for repeated epigastric distention. The man had never undergone gastric surgery and did not have Helicobacter pylori infection. Physical and laboratory tests showed no abnormality. Computed tomography showed no significant abnormality. Endoscopy revealed multiple ulcers on the posterior wall of the gastric body, but biopsy showed no evidence of malignancy. The patient subsequently underwent ESD surgery with a lesion of 1.5 cm×2.3 cm. Pathological results showed the cystic dilatation of gastric glands in the submucosa, with some well-differentiated adenocarcinoma. The final diagnosis was GCP with well-differentiated gastric adenocarcinoma.Herein, we describe a case of ESD therapy for GCP with well-differentiated gastric adenocarcinoma. When gastric mucosal lesions are difficult to diagnose, further treatment and diagnosis with EMR or ESD can be considered. For patients with early gastric cancer, long-term postoperative monitoring should be carried out.

Related Concept Videos
 01:21
Barrett Esophagus-I: Introduction
This constant acid exposure transforms the esophagus's pink mucosal lining (stratified squamous epithelium) into a type of lining more similar...
 01:27
Gastritis-I: Introduction and Types
Acute gastritis presents as a sudden inflammation triggered by various stressors to the stomach lining, such as exposure to corrosive agents, local irritants like aspirin and other NSAIDs, alcohol consumption, radiation therapy, physical trauma, severe burns, sepsis,...
 01:26
Gastritis II: Pathophysiology
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications
 01:27
Diverticular Disease of the Colon
 01:19
Appendicitis