Related Experiment Video
Updated: May 27, 2025


Donor Posterior Atrial Flap Rotation for Left Atrial Cuff Reconstruction in Lung Transplantation
Published on: October 11, 2024
Bilateral lung herniation with parenchymal infarction following clamshell thoracotomy for lobar lung transplantation:
Janis Tavandžis1, René Novysedlák1, Jiří Pozniak1
1Prague Lung Transplant Program, 3rd Department of Surgery, First Faculty of Medicine, Charles University and Motol University Hospital, Prague, Czech Republic.

Background:
Pulmonary hernia is a rare condition characterized by the protrusion of lung tissue through a chest wall defect. Trauma and thoracic surgery are the most common causes of acquired lung hernias. We present an unusual case of (sequential) bilateral lung herniation with parenchymal infarction after bilateral lobar lung transplantation.
Case Presentation:
A 50-year-old female, wait-listed as high-urgency candidate, with a body mass index (BMI) of 29 kg/m2 underwent a bilateral lobar lung transplantation for pulmonary fibrosis through a clamshell thoracotomy approach. Due to a size mismatch, stapler resection of the segment 3 and the middle lobe of the right lung, as well as an upper left lobectomy was required. The chest was closed with 3 braided non-absorbable pericostal sutures on each side. Sternal osteosynthesis was performed with a titanium sternal splint along with 7 self-tapping screws with a length of 18 mm. On the posttransplant day (PTD) 18, patient's clinical condition deteriorated. Physical examination didn't reveal any palpable subcutaneous chest resistance. However, a computed tomography (CT) scan showed a herniation of the segment 6 of the right lung. During acute surgical revision, perioperative finding revealed posterior pericostal suture failure. Therefore, a stapler resection was performed due to the infarction of the herniated segment. On the PTD 36, herniation of the left lung parenchyma was detected by acute CT scan. The protruding vital parenchyma was surgically repositioned without necessity of resection. Two posterior pericostal sutures were broken, and distal part of sternal splint detached. Thoracotomy was closed using 5 braided non-absorbable sutures. Sternum was re-osteosynthesized with the STRATOS™ system. After 3 months of intensive postoperative care, the patient was transferred to the rehabilitation department. She was discharged on the PTD 99. After 20 months of follow-up, lung function remains stable without the need for oxygen support.
Conclusion:
Clamshell incision remains ultimate approach in thoracic surgery. However, pulmonary herniation after clamshell thoracotomy is a rare complication and may manifest as acute respiratory distress syndrome with an inflammatory response. In these cases, CT scan should be always considered, even if no palpable pathology of chest is present.
Related Concept Videos
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:27
Pneumothorax-II
Clinical Manifestations:
 01:13
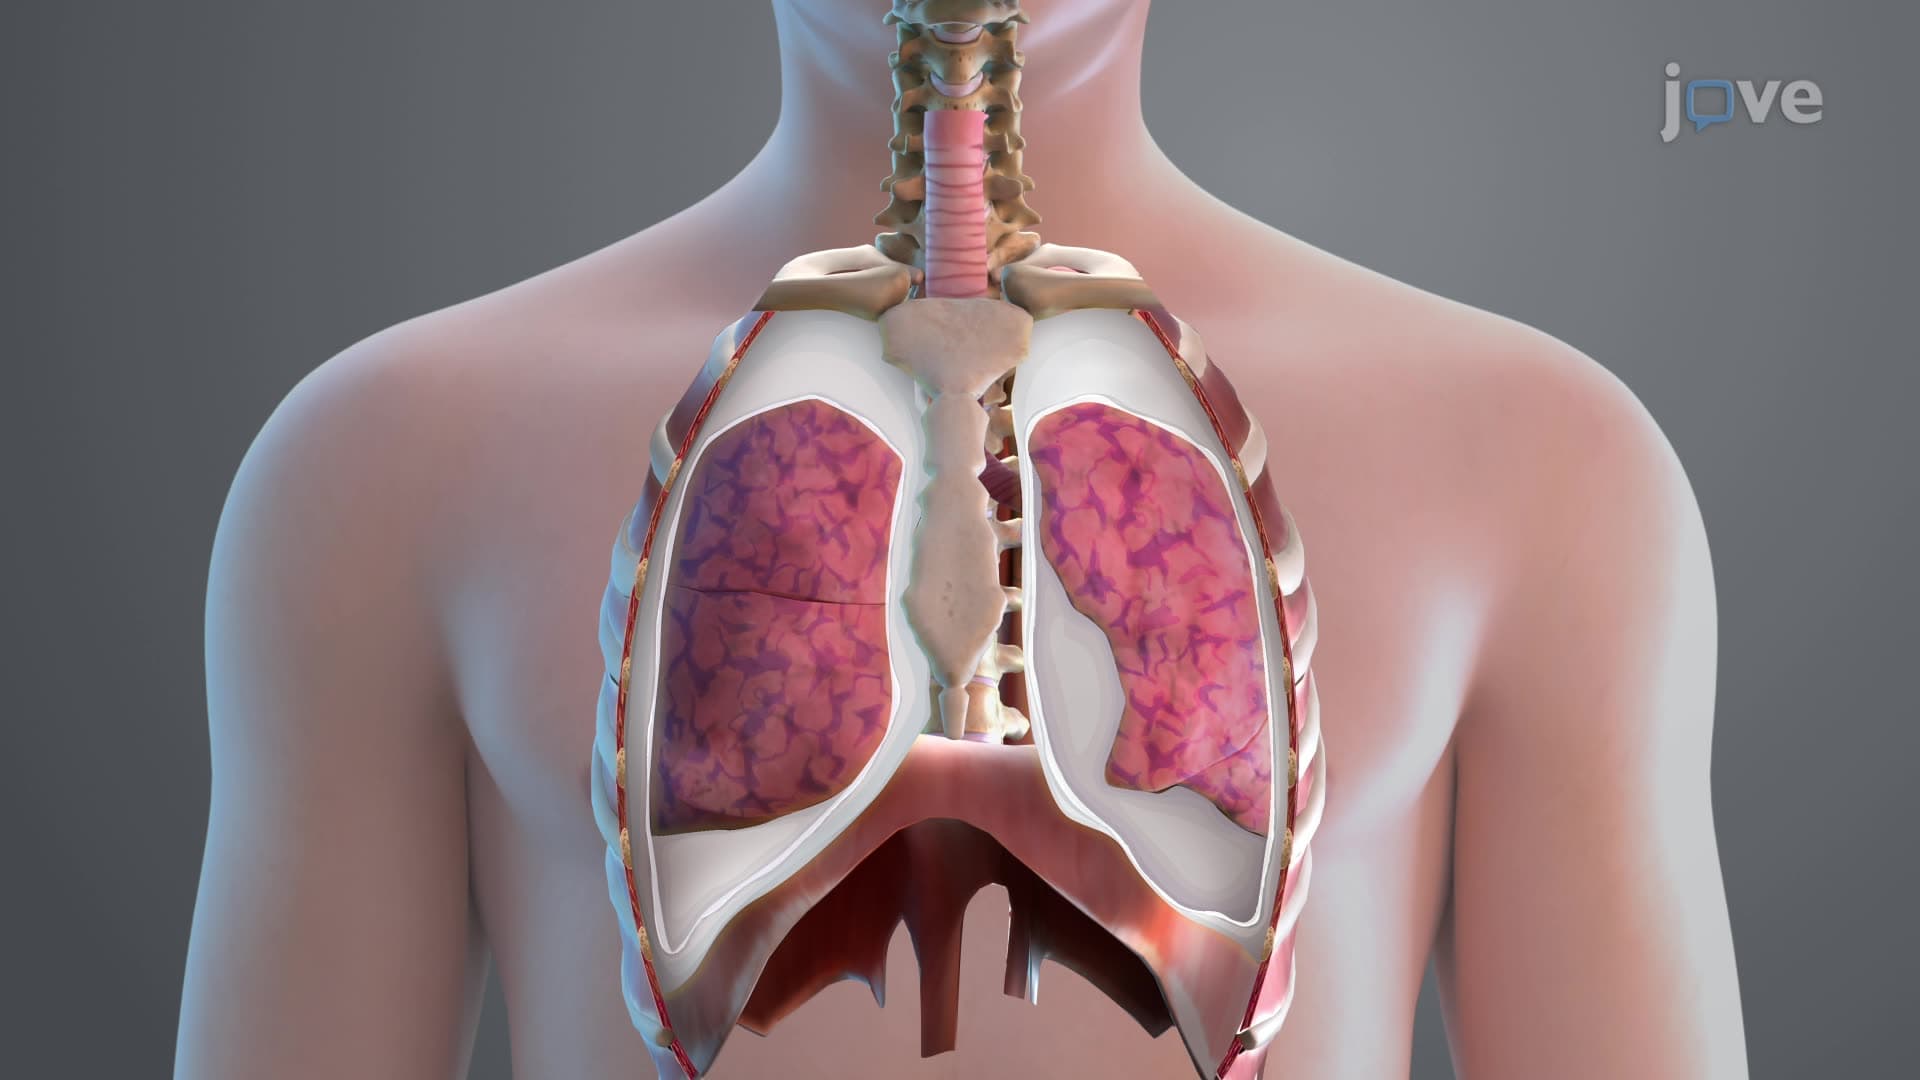
Pleura of the Lungs
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:24
Flail Chest-I
Flail chest is a severe and potentially life-threatening condition characterized by the fracture of three or more adjacent ribs in multiple places. It is most commonly caused by direct impacts and trauma, such as motor vehicle accidents or injuries from a steering wheel impact. It can also occur due to falls in elderly individuals with osteoporosis, or assaults involving sharp objects.
Pathophysiology
The pathophysiology of flail chest is complex, involving fractures of...