Related Experiment Video
Updated: May 27, 2025
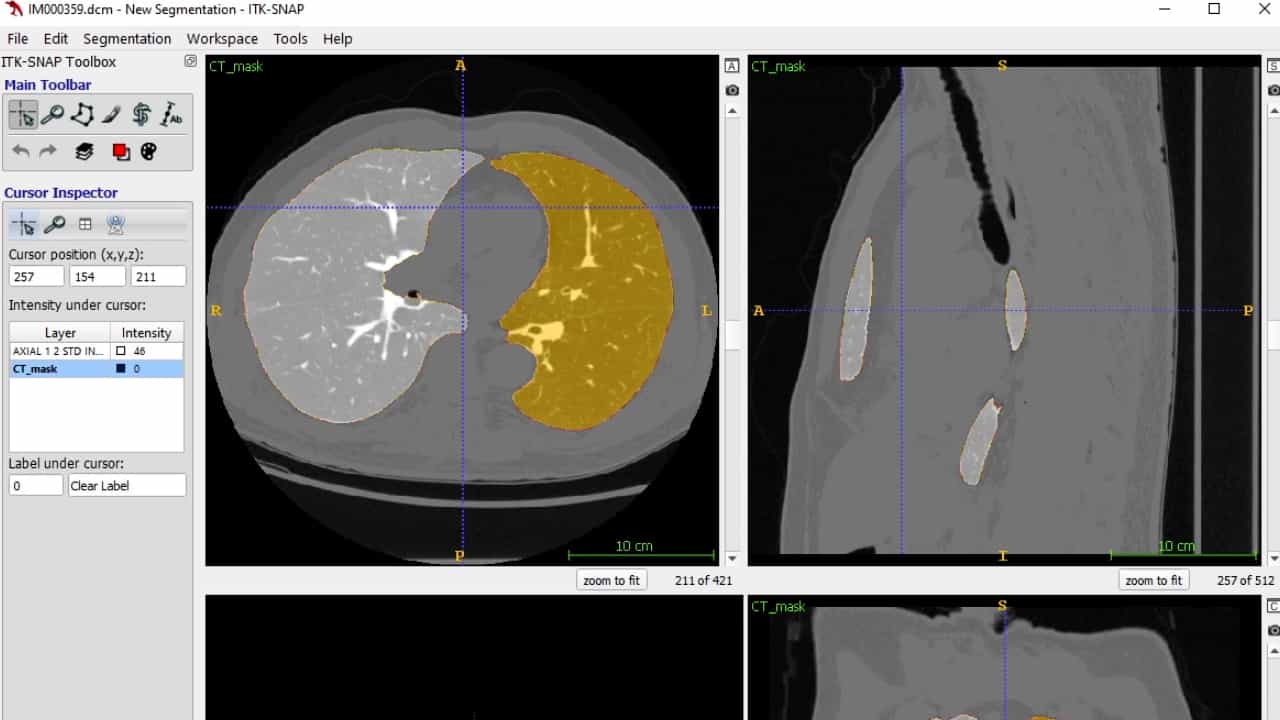
Multi-modal Pulmonary Imaging: Using Complementary Information from CT and Hyperpolarized 129Xe MRI to Evaluate Lung Structure-Function
Published on: April 12, 2024
Quantitative CT imaging characteristics of patients with chronic obstructive pulmonary disease with different
Lirong Du1, Xiaoxue Wu1, Shuiqing Zhao2
1Third Hospital of Shanxi Medical University, Shanxi Bethune Hospital, Shanxi Academy of Medical Sciences,Tongji Shanxi Hospital, Taiyuan, 032200, China.

Objective:
To investigate the relationship between eosinophil (EOS) and CT imaging, we quantitatively evaluated the bronchial wall thickening, emphysema index (EI) and pulmonary vascular parameters in patients with chronic obstructive pulmonary disease (COPD) based on different EOS levels.
Design:
Retrospective observational study.
Setting:
A tertiary hospital in China.
Participants:
448 patients with COPD from January 2020 to January 2023.
Main Outcome Measures:
Laboratory data, chest CT and pulmonary function based on different EOS levels: <150/µL, ≥150/µL; <100/µL, 100-300/µL, ≥300/µL; <2%, ≥2%.
Results:
We evaluated the records of 448 patients diagnosed with COPD. The prevalence of eosinophilia with EOS ≥2% was 41.1% (184 cases), 33.7% (151 cases) with EOS ≥150/µL and 9.4% (42 cases) with EOS ≥300/µL. A lower EOS (EOS <2% or EOS <150/µL) was associated with chronic pulmonary heart disease. The neutrophil count and percentage were significantly higher in the relatively lower EOS group (EOS <2%, EOS <150/µL or EOS <100/µL). When the groups were divided based on the two cut-off values of 2% of EOS percentage and 150/µL of absolute EOS value, no statistical significance was observed for the entire lung, left lung, right lung, lung lobe volume, lung index (EI), and lung emphysema heterogeneity index (HI). However, compared with the 100-300/µL group, the EI of the right upper lobe of the lung was lower in the EOS ≥300/µL group (0.32 vs 0.37, p<0.05). Airway wall thickness, wall area percentage and Pi10 in the EOS ≥2%, EOS ≥150/µL and 100-300/µL groups were lower than those in the EOS <2%, EOS <150/µL and EOS <100/µL groups, respectively. Compared with the EOS <100/µL group, Pi10 in the EOS ≥300/µL group was lower. According to the different cut-off values, such as percentage and absolute value of EOS, there was no significant difference in pulmonary vascular parameters, such as in cross-sectional area less than 5 mm2 (BV5), total blood volume (TBV), BV5/TBV, network length, branchpoints and endpoints (p>0.05 for both). The per cent predicted diffusing lung capacity for carbon monoxide (DLCO%) of the EOS ≥2% group was higher than that of the EOS <2% group. Compared with patients with blood EOS <150/µL, patients with blood EOS ≥150/µL had lower residual volume and lung volume ratio and higher values for per cent predicted forced vital capacity and DLCO%. The values for per cent predicted forced expiratory volume in 1 s, maximal expiratory flow at 75%/50%/25% of lung volume (MEF75%,MEF50%, MEF25%) and DLCO% in the EOS ≥300/µL group were higher than those in the EOS <100/µL group and in the 100-300/µL group.
Conclusions:
Hypereosinophilic COPD (EOS ≥2% or EOS ≥150/µL or EOS ≥300/µL) appears to have less bronchial thickening and better lung function. Notably, in patients with EOS ≥300/µL, the EI of the right upper lobe is reduced. These findings provide valuable insights into the role of EOS in COPD pathophysiology.
More Related Videos

Related Concept Videos
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:22
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:47
Lung Capacity