Related Experiment Video
Updated: May 26, 2025

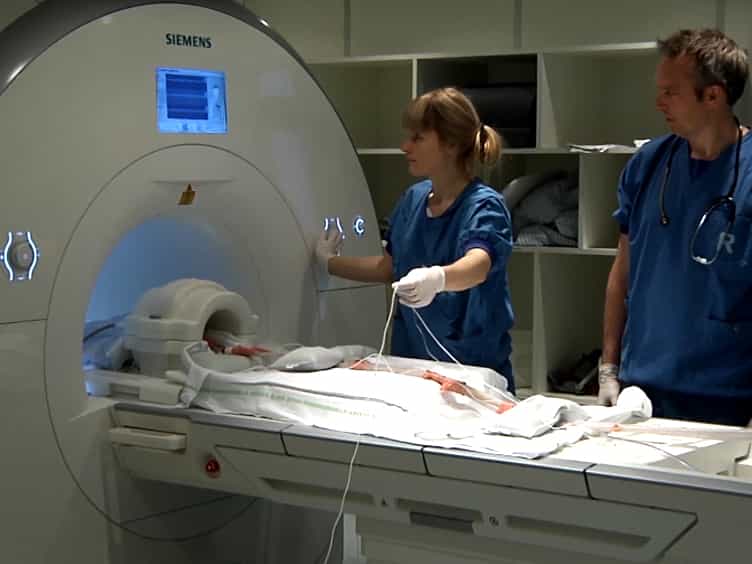
A Swine Model of Neonatal Asphyxia
Published on: October 11, 2011
Fluid restriction for term infants with hypoxic-ischemic encephalopathy following perinatal asphyxia-a randomized
Anitha Ananthan1, Haribalakrishna Balasubramanian2, Ruchi Nanavati1
1Department of Neonatology, Seth GS Medical College and King Edward Memorial Hospital, Mumbai, Maharashtra, 400012, India.

Insights
Fluid restriction did not improve outcomes for infants with hypoxic-ischemic encephalopathy (HIE). This study found no significant differences in mortality, neurological abnormalities, or long-term neurodevelopmental disability between fluid-restricted and conventional fluid groups in HIE infants.
Area of Science:
- Neonatal Medicine
- Pediatric Neurology
- Critical Care
Background:
- Fluid management is crucial for infants experiencing perinatal asphyxia and hypoxic-ischemic encephalopathy (HIE).
- Optimal fluid strategies in the first postnatal week for HIE infants remain an area needing further investigation.
- Therapeutic hypothermia is a standard treatment for moderate to severe HIE in term infants.
Purpose of the Study:
- To evaluate the impact of fluid restriction on short- and long-term outcomes in term infants diagnosed with moderate or severe HIE.
- To compare mortality, neurological abnormalities at discharge, and neurodevelopmental outcomes at 18-24 months between fluid-restricted and conventional fluid groups.
Main Methods:
- Randomized controlled trial involving 210 term infants with moderate or severe HIE receiving therapeutic hypothermia.
- Infants were assigned to either restricted intravenous fluids (starting at 45 ml/kg/day, max 120 ml/kg/day) or conventional fluids (starting at 60 ml/kg/day, max 150 ml/kg/day).
- Outcomes assessed included mortality, neurological status at discharge, cranial MRI findings, and neurodevelopmental disability using Bayley Scales at 18-24 months.
Main Results:
- No significant difference in the primary outcome of mortality or neurological abnormality at discharge between the restricted (57%) and conventional (53%) fluid groups (P=0.58).
- Cranial MRI abnormalities were similar between groups (65% vs 71%, P=0.30).
- Rates of severe neurodevelopmental disability at 18-24 months were comparable (27% vs 28%, P=0.88), with similar adverse outcomes overall.
Conclusions:
- Fluid restriction in the first postnatal week did not demonstrate a benefit in improving short-term or long-term neurodevelopmental outcomes for term infants with moderate or severe HIE.
- Current fluid management strategies for HIE infants do not appear to be significantly improved by early-life fluid restriction.
- Further research may be needed to explore alternative fluid management protocols or other therapeutic interventions for HIE.
Abstract:
Fluid management in the first postnatal week among infants with perinatal asphyxia and hypoxic-ischemic encephalopathy (HIE) is an important knowledge gap. We aimed to evaluate the effects of fluid restriction on short- and long-term outcomes in infants with HIE. Term infants with moderate or severe HIE on therapeutic hypothermia were randomized within 6 hours of age to receive either restricted intravenous maintenance fluids (45 ml/kg/day on day 1 to a maximum of 120 ml/kg/day on day 6) vs conventional fluid (60 ml/kg/day on day 1 to a maximum of 150 ml/kg/day on day 6). The primary outcome was a composite of mortality or neurological abnormality at hospital discharge. We studied neurodevelopmental disability at 18-24 months using Bayley Scales of Infant Development, third edition. A total of 210 infants were randomized. Three infants died during the hospital stay. The primary outcome of mortality or neurological abnormality at discharge was not significantly different between the restricted and the conventional fluid group [57% vs 53%, RR: 1.07 (95% CI: 0.83, 1.37), P-value .58]. The incidence of cranial magnetic resonance imaging abnormalities was similar in the groups (65% vs 71%, P-value .30). There were no differences in the rates of severe neurodevelopmental disability at 18-24 months in the two groups [27% vs 28%, RR: 0.96 (95% CI: 0.62, 1.50), P-value .88]. Adverse outcomes were similar in both groups. Fluid restriction in the first postnatal week of life did not improve short- and long-term neurodevelopmental outcomes in term infants with moderate or severe HIE.