Related Experiment Video
Updated: May 26, 2025
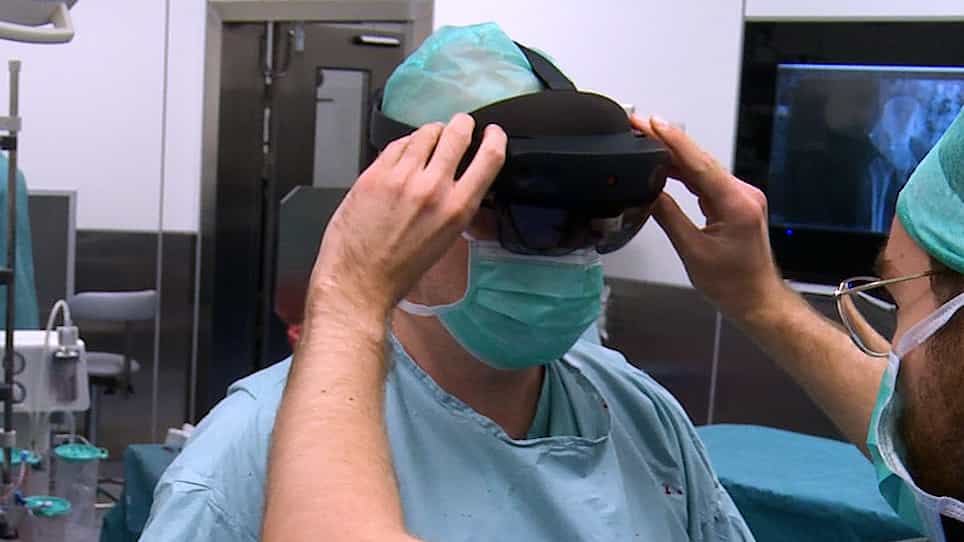
The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Comparative and predictive modeling of modern anatomic total shoulder arthroplasty revision rates in osteoarthritis
David R J Gill1, Sophia Corfield1, Peiyao Du2
1Australian Orthopaedic Association National Joint Replacement Registry (AOANJRR), Adelaide, South Australia, Australia.

Background:
The revision rates of 4 modern (currently used) polyethylene glenoid designs in anatomic total shoulder arthroplasty (stemmed and stemless) for osteoarthritis (OA) are compared from a national arthroplasty registry to model predictive variables.
Materials And Methods:
The study period was January 1, 2008, to December 31, 2023. The study population included all primary anatomic total shoulder arthroplasty (aTSA) procedures undertaken for OA. We classified the designs of modern polyethylene glenoids (glenoid component types) into 4 cohort groups: cemented all-polyethylene glenoids (CPGs), polyethylene glenoids with modified central pegs (MCPGs), nonmodular metal-backed glenoids (NMBGs), and hybrid glenoids (HGs). The cumulative percentage revision (CPR) was defined using Kaplan-Meier estimates of survivorship and hazard ratios (HRs) from Cox proportional hazard models adjusted for age, sex, humeral head size, humeral fixation, primary type (stemmed or stemless), and mean surgeon volume. Only prostheses with all known variables were analyzed. Possible interactions were examined. A subanalysis was undertaken capturing additional patient demographics from January 1, 2017.
Results:
There were 9332 primary aTSA procedures. The CPR at 8 years for CPG (n = 5048) was 5.5% (95% confidence interval [CI] 4.6, 6.4), 3.8% (95% CI 2.9, 5.1) for MCPG (n = 2217), and 9.4% (95% CI 7.4, 11.9) for HG (n = 1658). The NMBG (n = 409) had a 2-year CPR of 4.7% (95% CI 2.1, 10.1). The glenoid component type (CPG, MCPG, NMBG, or HG) influenced the rate of revision of aTSA (P < .001). There is evidence for an interaction term between age and glenoid type (P = .009), with a better model (Akaike information criterion [AIC] 6205.9) than main effects only (AIC 6211.5). There was no difference at subanalysis, whereas the patient sex, type of primary, polyethylene type, American Society of Anesthesiologists class, body mass index, glenoid fixation, glenoid morphology, and mean surgeon volume were less predictive than glenoid component type alone.
Conclusion:
Modern aTSA outcome for OA is affected by the polyethylene glenoid design implanted, with the result only modified further by patient's age. Informed decision making about aTSA current prosthesis survival is more accurate if age of the patient is included.
More Related Videos
 09:51
The Transition to an Anterior-Based Muscle Sparing Approach Improves Early Postoperative Function but is Associated with a Learning Curve
Published on: September 7, 2022
 09:08
Biotribological Testing and Analysis of Articular Cartilage Sliding against Metal for Implants
Published on: May 14, 2020