Related Experiment Video
Updated: Jun 15, 2026
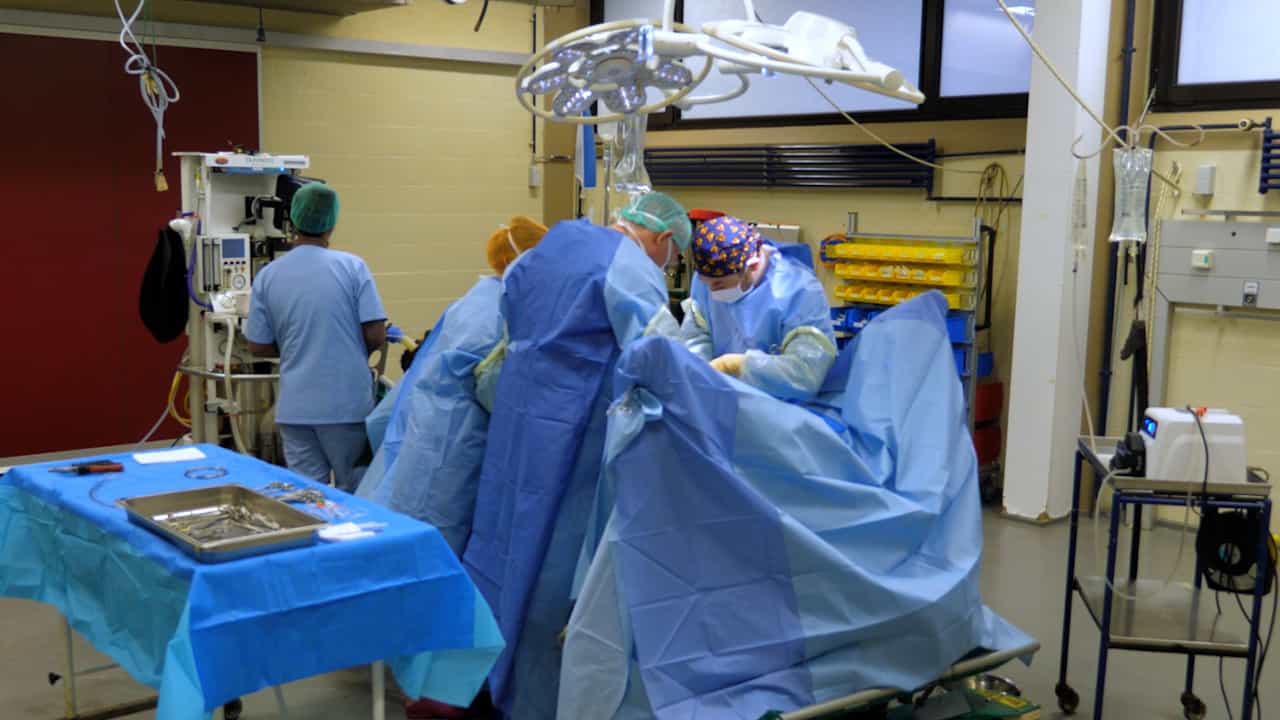
Surgical Closure of Equine Abdomen, Prevention, and Management of Incisional Complications
Published on: May 10, 2024
Open abdomen versus primary closure in nontrauma patients: A weighted analysis of a single-center experience
Francesca Margherita Bunino1, Davide Zulian, Simone Famularo
1From Emergency and Trauma Surgery Unit, Department of General Surgery (F.M.B., G.M., D.D.), IRCCS Humanitas Research Hospital; Department of Biomedical Sciences (F.M.B., G.W.L.P., G.M.), Humanitas University; Department of General Surgery (D.Z., G.W.L.P.), IRCCS Humanitas Research Hospital, Milan; Hepatobiliary Surgery Unit (S.F.), Fondazione Policlinico Universitario A. Gemelli, IRCCS, Catholic University of the Sacred Heart, Rome, Italy; and IRCAD (S.F.), Research Institute Against Cancer of the Digestive System, Strasbourg, France, Fondazione Ca' Granda IRCCS Ospedale Maggiore Policlinico, Milan, Italy (F.M.B).

Introduction:
The open abdomen (OA) technique is nowadays a worldwide strategy both for trauma and emergency general surgery. Despite the attempt at conducting prospective studies, a high level of evidence is far from established. The aim of this study was to investigate if we overused this strategy and if it improved the postoperative course of our patients.
Methods:
Emergency laparotomies from 2017 and 2023 were reviewed and stratified according to OA and closed abdomen (CA). Differences were balanced by inverse probability weighting, and the 90-day mortality was estimated. Subgroup analysis was carried out for patients with a Mannheim Peritonitis Index (MPI) of >26, bowel obstruction, bowel ischemia (BI) and gastrointestinal perforation.
Results:
Of the 320 patients, 167 were CA and 153 were OA. Groups were different for American Society of Anesthesiologists, comorbidities, transfusion rate, Physiologic and Operative Severity Score for the Study of Mortality and Morbidity score, MPI, Clinical Frailty Scale score, diagnosis, and resection. Two balanced pseudo-populations were created. The 90-day survival rate was 50.8% for CA and 60.8% for OA (hazard ratio [HR], 0.79; confidence interval [CI], 0.40-1.55; p = 0.502). At the Cox regression, the Clinical Frailty Scale score (HR, 1.125; 95% CI, 1.01-1.25; p = 0.033) and BI (HR, 5.531; 95% CI, 2.37-12.89; p < 0.001) were independent risk factors for mortality. Transfusion rate (odds ratio [OR], 3.44; 95% CI, 1.44-8.23; p < 0.006) and length of stay in the intensive care unit (OR, 1.13; 95% CI, 1.07-1.20; p < 0.001) were associated with major complications. Open abdomen did not modify mortality in the case of bowel obstruction, MPI >26, or gastrointestinal perforation. Finally, OA (HR, 0.056; 95% CI, 0.01-0.22; p = 0.001) and large bowel resection (HR, 6.442; 95% CI, 1.28-32.31; p = 0.040) were predictors of longer survival in the subgroup of patients with BI.
Conclusion:
Open abdomen was not associated with a higher complication rate or higher mortality but did result in a longer in-hospital stay. The only setting where OA seemed to be advantageous was in the BI population.
Level Of Evidence:
Prognostic and Epidemiological; Level III.
More Related Videos
 05:15
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
 20:33
A Case Series of Successful Abdominal Closure Utilizing a Novel Technique Combining a Mechanical Closure System with a Biologic Xenograft that Accelerates Wound Healing
Published on: July 4, 2019