Related Experiment Video
Updated: Jul 13, 2026


Minimally Invasive Endoscopic Intracerebral Hemorrhage Evacuation
Published on: October 15, 2021
Beyond the bleed: Navigating fetal intraventricular hemorrhage
Hillary C Lee1, Amee A Amin1, Danielle N Gonzales1
1Section of Neonatal-Perinatal Medicine, Department of Pediatrics, Baylor College of Medicine/Texas Children's Hospital, Houston, TX, USA.

Background: Antenatal intraventricular hemorrhage (IVH) is intracranial hemorrhage that occurs in utero at an incidence of 1-5 per 10,000. Though there is very limited data on neurodevelopmental prognosis, antenatally diagnosed fetal intracranial hemorrhages carry a very poor prognosis with an estimated 40% mortality in utero or within the first month after birth. Less than 50% of survivors have normal neurodevelopmental outcomes during their postnatal follow-up. We present a healthy, term infant, who was prenatally diagnosed with a grade IV fetal IVH.Case: A term, male infant was delivered via elective cesarean section following a prenatal diagnosis of unilateral grade IV intraventricular hemorrhage with bilateral cerebral ventriculomegaly. Pregnancy had been unremarkable with no history of trauma, hematologic, or infectious etiology. Extensive post-natal evaluation confirmed the prenatal MRI findings and an unremarkable infectious and hematologic evaluation but revealed a genetic syndrome for 15q11.2 deletion. On day of life 18, the infant was discharged home with parents, tolerating full oral feeds and with appropriate weight gain. Continued outpatient follow-up has revealed no further progression of the bleed on serial neuroimaging with the infant meeting appropriate developmental milestones at 6 months of age.Conclusion: Despite early detection, fetal intracranial hemorrhage (ICH) has poor outcomes compared to post-natal prematurity related IVH. Parents of affected fetuses should be counseled about poor survival rates and adverse neurodevelopmental outcomes, especially following the diagnosis of grade III or IV IVH.
Background: Antenatal intraventricular hemorrhage (IVH) is intracranial hemorrhage that occurs in utero at an incidence of 1-5 per 10,000. Though there is very limited data on neurodevelopmental prognosis, antenatally diagnosed fetal intracranial hemorrhages carry a very poor prognosis with an estimated 40% mortality in utero or within the first month after birth. Less than 50% of survivors have normal neurodevelopmental outcomes during their postnatal follow-up. We present a healthy, term infant, who was prenatally diagnosed with a grade IV fetal IVH.Case: A term, male infant was delivered via elective cesarean section following a prenatal diagnosis of unilateral grade IV intraventricular hemorrhage with bilateral cerebral ventriculomegaly. Pregnancy had been unremarkable with no history of trauma, hematologic, or infectious etiology. Extensive post-natal evaluation confirmed the prenatal MRI findings and an unremarkable infectious and hematologic evaluation but revealed a genetic syndrome for 15q11.2 deletion. On day of life 18, the infant was discharged home with parents, tolerating full oral feeds and with appropriate weight gain. Continued outpatient follow-up has revealed no further progression of the bleed on serial neuroimaging with the infant meeting appropriate developmental milestones at 6 months of age.Conclusion: Despite early detection, fetal intracranial hemorrhage (ICH) has poor outcomes compared to post-natal prematurity related IVH. Parents of affected fetuses should be counseled about poor survival rates and adverse neurodevelopmental outcomes, especially following the diagnosis of grade III or IV IVH.


Related Concept Videos
 01:25
Abdominal Aorta
The celiac trunk, a singular artery, divides into the left gastric artery, which...
 01:07
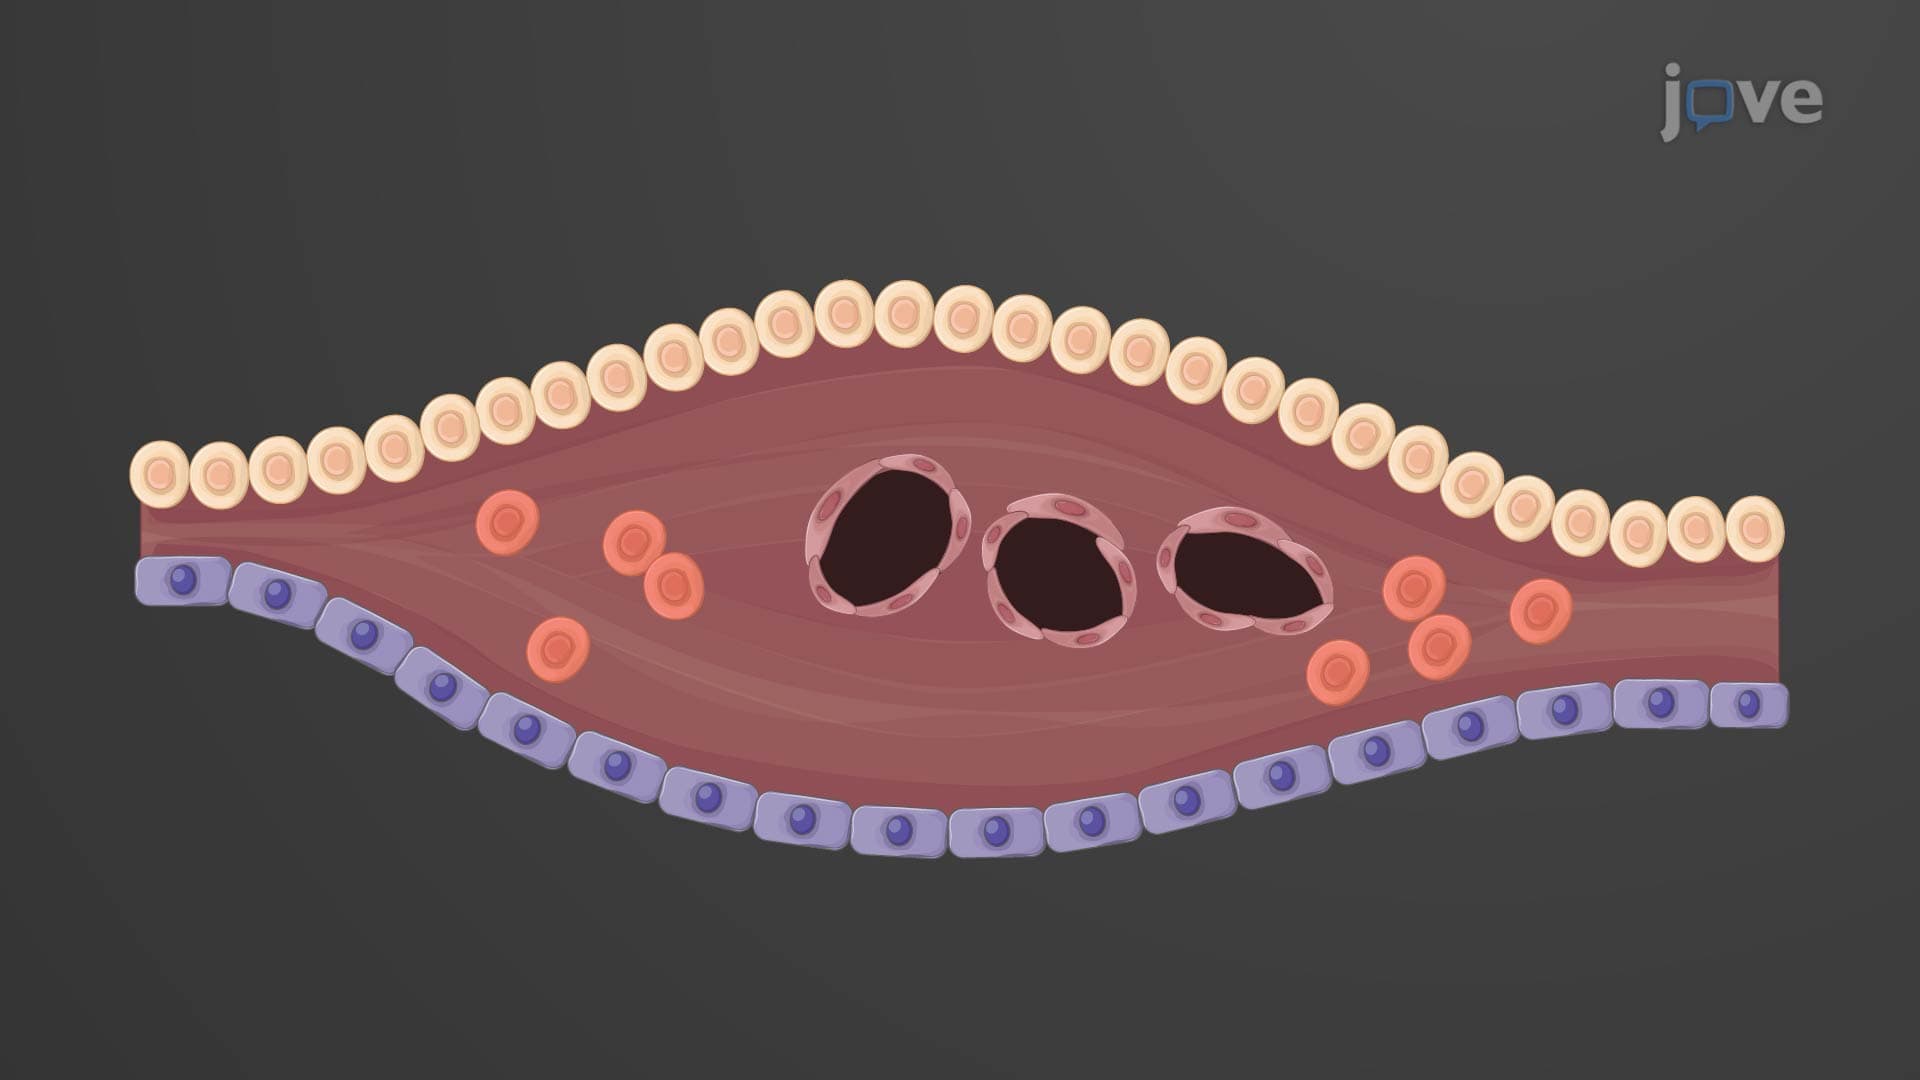
Development of Blood Vessels
The initial formation of this system is facilitated by the small amount of yolk present in the ovum and yolk sac. Blood vessels originate from...
 01:14
Fetal Circulation
Two umbilical arteries transport blood from the fetus to the placenta. At the placenta, the blood absorbs oxygen and nutrients while simultaneously eliminating waste products. This oxygen-enriched and nutrient-rich blood then returns to the fetus through one...
 01:16
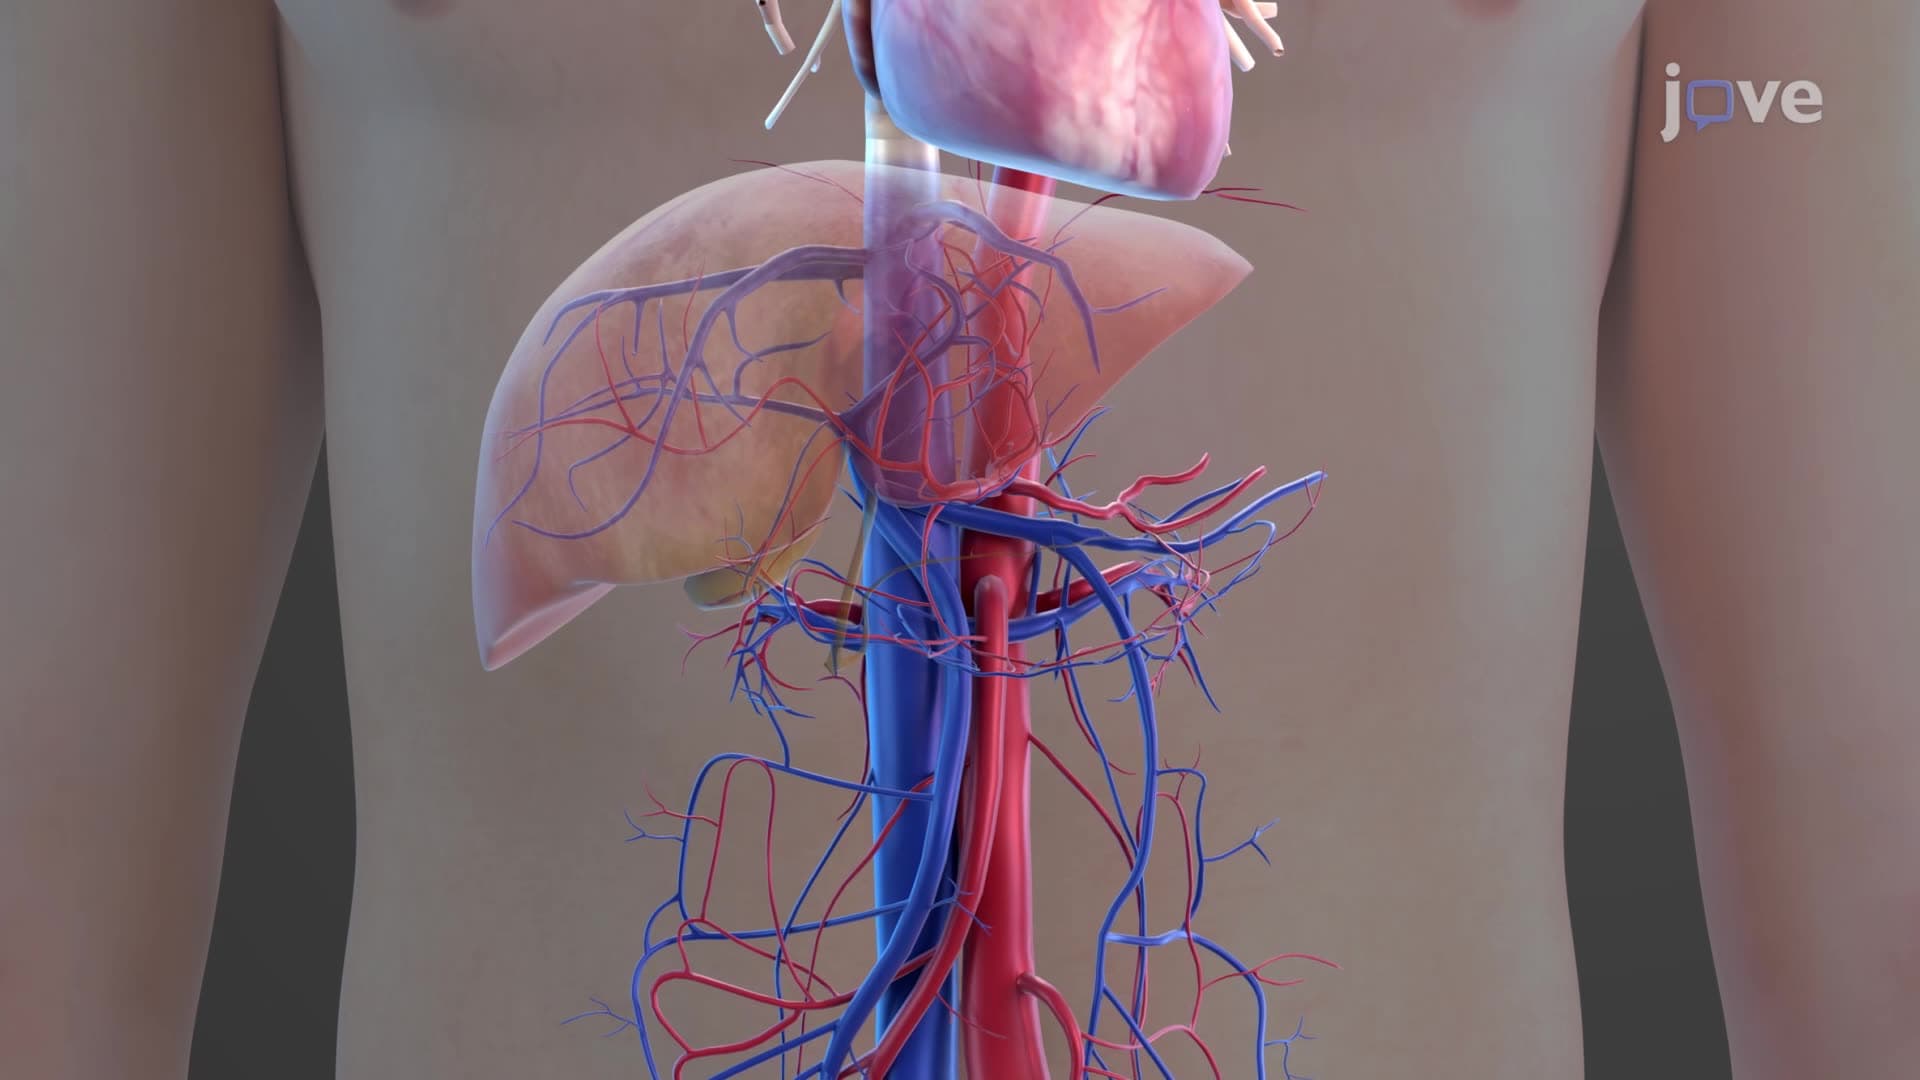
Blood Supply to the Digestive System
Blood Supply to the Digestive System: The splanchnic circulation involves three main arteries: the celiac artery (also known as the celiac trunk) and the superior and inferior mesenteric...
 01:24
Esophageal Varices-I: Introduction
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol abuse, or...