Related Experiment Video
Updated: May 12, 2026
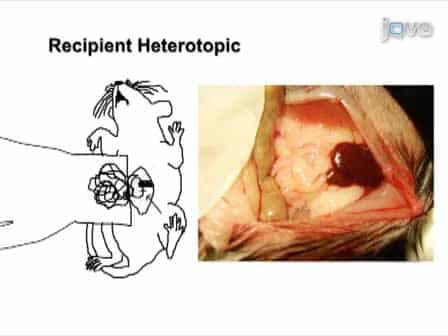
Heterotopic and Orthotopic Tracheal Transplantation in Mice used as Models to Study the Development of Obliterative Airway Disease
Published on: January 20, 2010
Partial cricotracheal resection for treatment of subglottic stenosis: complications and outcomes
Jeroen Meulemans1,2, Laila Mouqni1, Noah Ostyn1
1Otorhinolaryngology, Head and Neck Surgery, University Hospitals Leuven, Leuven, Belgium.

Purpose:
Subglottic stenosis (SGS) is defined as an obstruction of the subglottic area, potentially extending towards the first tracheal rings. Although endoscopic procedures are frequently preferred as first-line treatment, (partial) cricotracheal resection (PCTR) offers the most durable results. This study aims at reporting and analysing complications and respiratory and vocal outcomes after PCTR.
Methods:
For this retrospective cohort analysis, the files of 37 patients with SGS who underwent PCTR in a tertiary referral center were reviewed. Patient- and stenosis-characteristics along with postoperative outcomes and complications were analyzed using descriptive statistics.
Results:
The majority of patients were female (95%), which reflects the high incidence of idiopathic SGS in our patient group (89.2% vs. 2.7% postintubation SGS and 8.1% SGS related to systemic inflammatory disease). Most patients presented with a Cotton grade II (35.1%) and III (54.1%) stenosis, with a mean craniocaudal stenosis length of 17.5 mm. The vast majority of patients (89.2%) had undergone previous endoscopic procedures. The most common complication after PCTR was fibrin deposit/granulation tissue formation at the anastomotic site (n = 15, 40.5%). Other complications were rare, with anastomotic dehiscence, postoperative haemorrhage and vocal cord paralysis each in 1 patient (2.7%), temporary tracheostomy in 2 patients (5.4%), and postoperative wound infection in 3 patients (8.1%). During follow-up, only 2 patients (5.4%) developed restenosis which was successfully salvaged by endoscopic procedures. No patients were long-term tracheostomy dependent. Post-operative mean peak expiratory flow (PEF) percentage showed a 43.7% increase compared to pre-operative. For the mean increase in maximum inspiratory flow (MIF) at 50% this was 1.3 L/s. VHI (voice handicap index) scores increased significantly from baseline preoperative score of 27.5 (±23.7) to a mean value of 54.9 (±18.7) (p = 0.002) 1-month postoperatively but decreased below preoperative scores after 2 years (22.2 ± 18.1, p = 0.036).
Conclusion:
PCTR is an efficient treatment for SGS, with low complication rates, a low rate of long-term restenosis and good vocal outcomes.
Related Concept Videos
 01:22
Trachea
Anatomical Features:
Location: About half of the trachea is situated in the neck, anterior to the esophagus, and extends from the larynx (at the level of the...
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:30
Cardiopulmonary Resuscitation V: Advanced Airway Management Techniques