Related Experiment Video
Updated: Aug 5, 2026

Three-dimensional Navigation-guided, Prone, Single-position, Lateral Lumbar Interbody Fusion Technique
Published on: July 15, 2021
[Occurrence and risk factors of adjacent segment degeneration after early extreme lateral interbody fusion]

Abstract:
Objectives: To investigate the incidence of adjacent segment degeneration (ASD) following extreme lateral interbody fusion (XLIF) and identify risk factors for early ASD after XLIF. Methods: A retrospective study was conducted, including patients diagnosed with lumbar spinal stenosis who underwent XLIF at Tianjin Hospital between July 2019 and December 2022 and were followed-up for at least one year. Preoperative and final follow-up lumbar MRI and X-ray examination were performed for all patients to evaluate the degeneration status of adjacent segments. According to the occurrence of ASD at the last follow-up, the patients were divided into non-ASD group and ASD group. Age, gender, age, body mass index (BMI), American Society of Anesthesiologists (ASA) grade of anesthesia, follow-up time, length of fusion, time of operation, blood loss, hospital stay, pre-operation and follow-up clinical effects scores, pre-operation and follow-up sagittal parameters, central canal stenosis grades of adjacent segment and Pfirrmann grades were analyzed and compared between the two groups. Variables with a P-value less than 0.1 in the intergroup comparisons were included in a multivariate regression analysis to identify the risk factors for early onset of ASD following XLIF. Results: A total of 68 patients were included in this study, including 20 males and 48 females with a mean age of (60.0±6.9) years. At the last follow-up, 20 cases (28.9%) developed ASD and were included in the ASD group, while the remaining 48 cases were included in the non-ASD group. There was no statistically significant differences in the demographic characteristics between the two groups of patients (all P>0.05), indicating comparability. Compared with those in ASD group, the preoperative lumbar lordosis angle (LL) (46.5°±12.0° vs 32.3°±15.9°, P<0.01) and the sacral slope angle (SS) (36.6°±7.1° vs 29.5°±12.6°, P=0.022) in the non-ASD group were both greater, the mismatch rate of the preoperative pelvic incidence-lumbar lordosis angle (PI-LL) was lower [25.0% (12/48) vs 60.0% (12/20), P=0.033], and the preoperative morphologic grading of adjacent segmental vertebral canals was better (grades 0/1 were 33/15 and 6/14 cases, respectively, P<0.01). Compared to preoperative values, both groups showed significant improvements in the Oswestry disability index (ODI) score, VAS (back), and VAS (leg) at the last follow-up (all P<0.01). However, there were no statistically significant differences in the preoperative clinical function scores and the clinical function improvement rates at the last follow-up between the two groups (all P>0.05). Multivariate analysis showed that the preoperative central canal stenosis grade 1 of adjacent segment was a risk factor for ASD after early XLIF (OR=13.00, 95%CI: 2.51-67.04, P<0.01). Conclusions: About 28.9% of patients may experience ASD one year after XLIF surgery, preoperative adjacent segment central canal stenosis grade 1 is a risk factor for early postoperative ASD after XLIF surgery.
More Related Videos


Related Concept Videos
 01:29
Herniated Intervertebral Disc l: Introduction
 01:27
Degenerative Disc Disease I: Introduction
 01:23
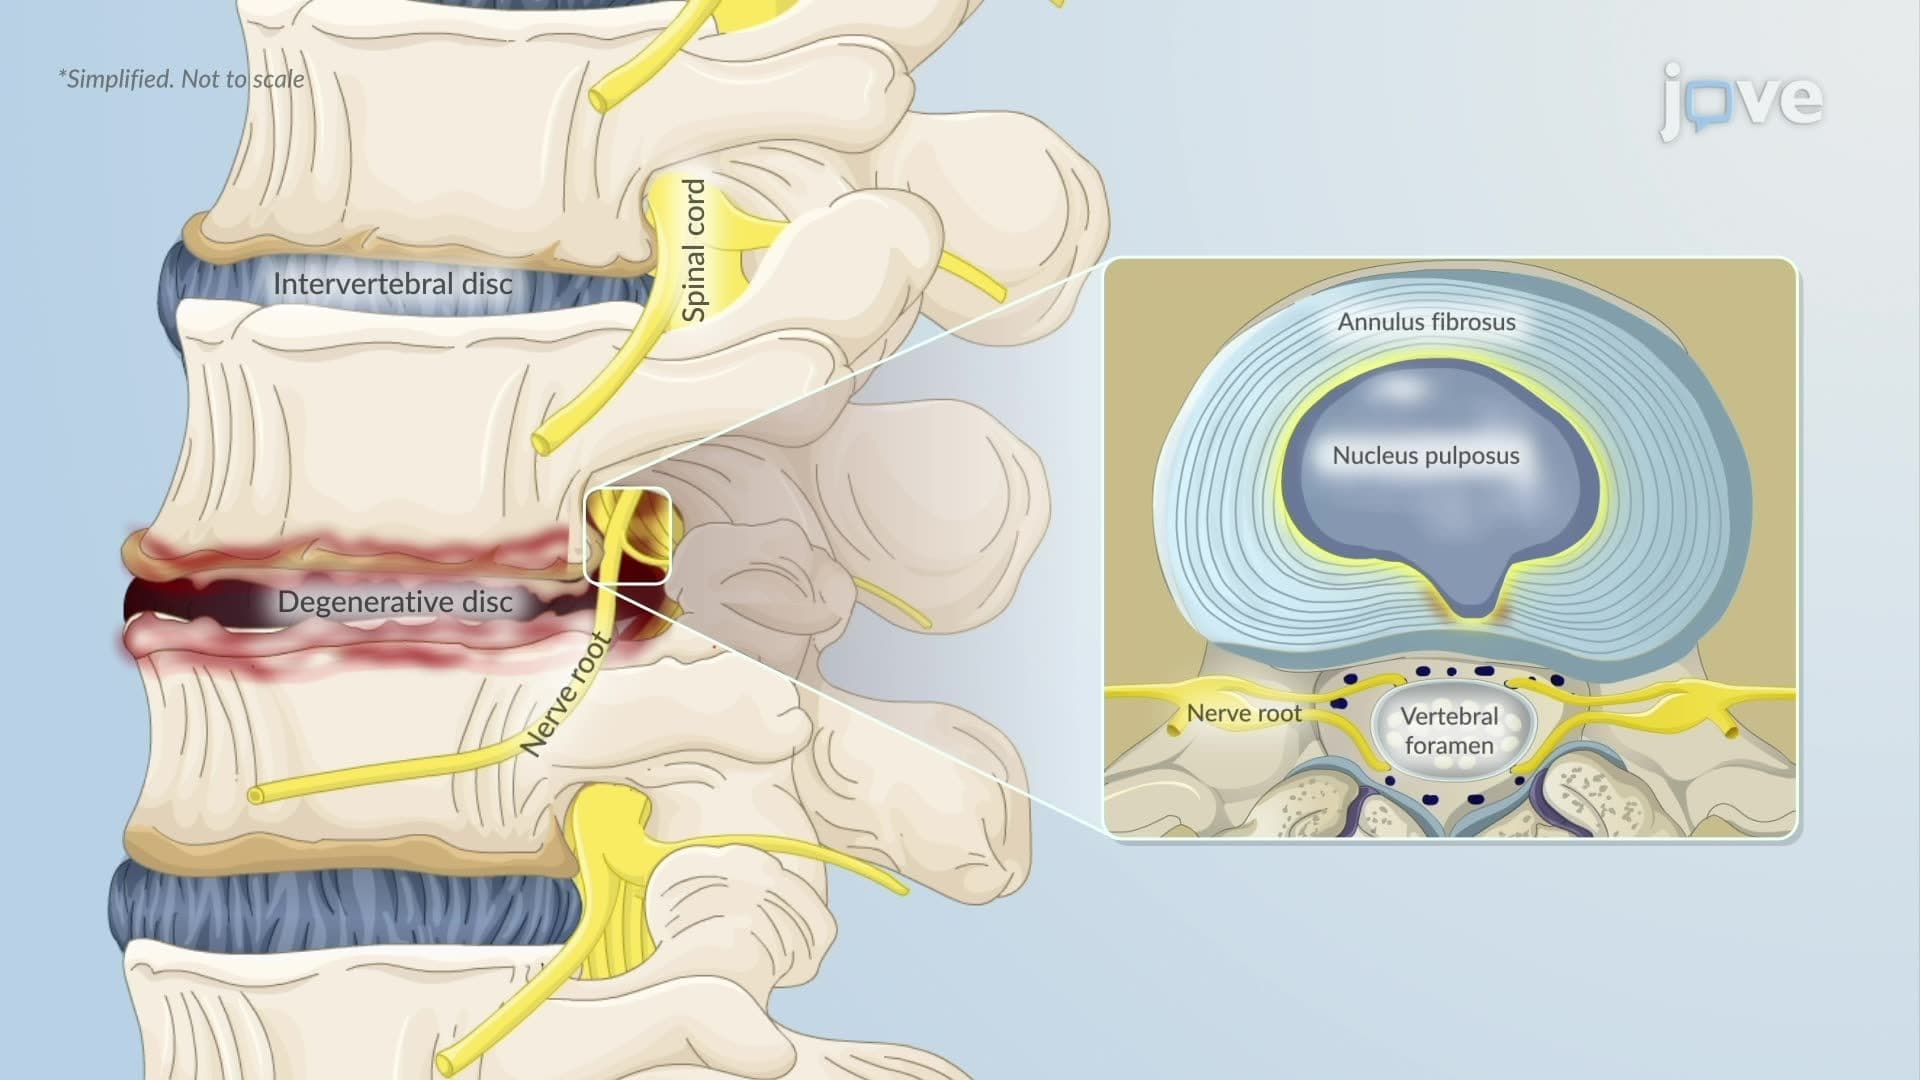
Degenerative Disc Disease ll: Pathophysiology