Related Experiment Video
Updated: May 24, 2025
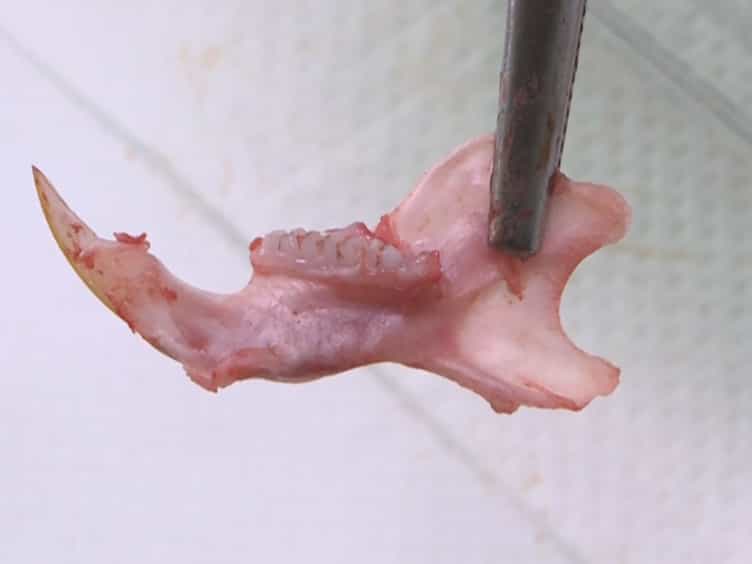

Micro-dissection of Enamel Organ from Mandibular Incisor of Rats Exposed to Environmental Toxicants
Published on: March 29, 2018
From teeth to bone: dental caries has causal effects on osteoporosis and osteoporotic fracture
Gongzi Zhang1,2, Juan Zheng1, Ying Zhou1
1Department of Rehabilitation, Chinese PLA General Hospital, No.28 Fuxing Road, Haidian District, Beijing, 100853, People's Republic of China.

Objectives:
Evidence from observational studies suggested oral diseases (periodontitis (PD) and dental caries) may increase susceptibility to bone loss. However, inherent confounding of observational studies limits causal interpretation. We aimed to conduct Mendelian randomization (MR) analysis to estimate the causal effect of oral diseases on osteoporosis (OP), bone mineral density (BMD) and fracture risk.
Methods:
We used summary-level GWAS meta-analysis data from the GLIDE consortium to identify 7 and 17 single-nucleotide polymorphisms (SNPs) for periodontitis and DMFS (the sum of Decayed, Missing, and Filled tooth Surfaces) as the instrumental variables. MR analyses of these instruments were performed on European individuals for the association with BMD of forearm, femoral neck and lumbar spine; and individuals from FinnGen consortium for OP, OP with pathological fracture, postmenopausal OP with pathological fracture, and site-specific fractures. We performed single-variable Mendelian randomization (SVMR) and multivariable Mendelian randomization (MVMR) to simultaneously assess independent causal effects of PD and DMFS on different outcomes. The estimates were primarily derived using inverse variance weighted (IVW) methods. Sensitivity analyses included weighted median, MR-egger, and Leave-one-out test.
Results:
In MVMR, after adjusting for PD, DMFS has a positive causal effect osteoporosis (OR = 1.165, [95% CI 1.020 to 1.331, P = 0.025]) and postmenopausal OP with pathological fracture (OR = 1.422, [95% CI 1.027 to 1.969, P = 0.034]). However, these causal relationships were not observed in the single-variable Mendelian randomization (SVMR) analysis. The causal associations were robust in various sensitivity analyses.
Conclusions:
In conclusion, dental caries causally increases the risk of OP and postmenopausal OP with pathological fracture, suggesting the existence of teeth-bone axis. Proactive osteoporosis screening in patients with severe dental caries may be warranted for clinical consideration.

Related Concept Videos
 01:29
Bone Disorders
Bone deposition is also affected by the levels of sex hormones like estrogen and testosterone that promote osteoblast activity and bone matrix synthesis. When the level of these hormones decreases due to aging, it causes a reduction in bone deposition. As a result, bone resorption by osteoclasts...
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...
 01:31
Osteoclasts in Bone Remodeling
 01:31
Essential Minerals for Bone Health
Calcium and Phosphorus
Calcium is a critical component of bones, especially in the form of calcium phosphate and calcium carbonate. Since the body cannot make calcium, it must be obtained from the diet. However, calcium cannot be absorbed from the small intestine without...
 01:17
Hormones and Bone Tissue
Hormones That Influence Osteoblasts and/or Maintain the Matrix
Several hormones are necessary for controlling bone growth and maintaining the bone matrix. The pituitary gland secretes growth hormone (GH), which, as its name implies, controls bone growth. This happens in several ways: first, it triggers chondrocyte...
 01:40
Bone Remodeling