Related Experiment Video
Updated: May 23, 2025
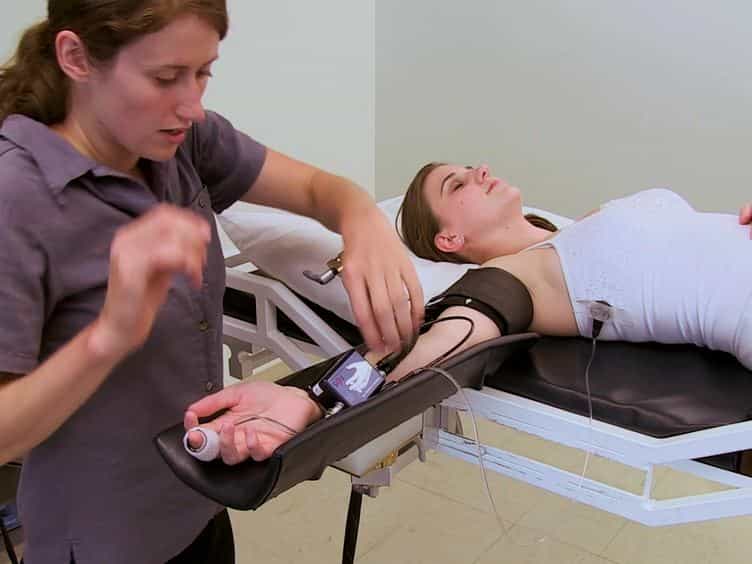

Tilt Testing with Combined Lower Body Negative Pressure: a "Gold Standard" for Measuring Orthostatic Tolerance
Published on: March 21, 2013
Stretch syncope in humans: Evidence for symptomatic neural reflex hypotension triggered by stretching of shoulder and
Marinos Kosmopoulos1, Jorge L Reyes1, Sima Patel2
1Cardiovascular Division, Department of Medicine, University of Minnesota Medical School, Minneapolis, Minnesota.

Background:
Stretch-induced syncope (SIS) is a poorly understood condition that we hypothesized may be due to a neural reflex hypotensive response triggered by stretching of shoulder/upper back muscles.
Objective:
This study compared the impact of shoulder/upper back stretching on heart rate (HR) and blood pressure (BP) responses in patients with SIS, with the findings in controls evaluated for symptoms unrelated to stretching.
Methods:
The study population comprised 33 individuals: 9 otherwise healthy patients with SIS and 24 healthy controls. Beat-to-beat HR and systolic BP (SBP) and mean arterial pressure (MAP) responses were recorded during active standing (AS), Valsalva maneuver, and respiratory sinus arrhythmia. Patients with SIS also underwent carotid sinus massage while seated. In addition, all subjects undertook an active shoulder/upper back extension maneuver for approximately 10-15 seconds while keeping forearms still and breathing normally.
Results:
Stretch elicited a drop in BP to nadir values of SBP and MAP (95.9 ± 24.2 and 76.2 ± 17.3 mm Hg in patients with SIS and controls, respectively). However, stretch-induced SBP and MAP decrease was greater in patients with SIS (P=.003 and P=.013). Further, the ratio of the ΔHR increase to ΔBP drop was lower (P=.001) during stretch-induced hypotension than during comparable hypotension induced immediately after AS.
Conclusion:
Shoulder/upper back stretching induces a transient hypotensive response in humans, with BP fall greater in patients with SIS than in controls. Further, compensatory HR increment associated with stretch-induced hypotension was less in both patients with SIS and controls than comparable transient BP fall with AS, suggesting chronotropic restraint. Thus, SIS results from exaggerated stretch-induced vasodepression with limited compensatory tachycardia favoring a neural reflex mechanism.
More Related Videos
 06:51
Development of an Algorithm to Perform a Comprehensive Study of Autonomic Dysreflexia in Animals with High Spinal Cord Injury Using a Telemetry Device
Published on: July 29, 2016
 11:06
A Human-machine-interface Integrating Low-cost Sensors with a Neuromuscular Electrical Stimulation System for Post-stroke Balance Rehabilitation
Published on: April 12, 2016
Related Concept Videos
 01:18
Disorders of the Autonomic Nervous System
Raynaud's disease, also known as Raynaud's...
 01:22
Somatic Spinal Reflexes
One of the most well-known somatic spinal reflexes is the stretch reflex, which is activated by the sudden stretching of a muscle. This reflex involves the activation of specialized sensory receptors called muscle spindles, which are located in the muscle tissue and detect changes in the length and speed of muscle contractions. When a muscle is suddenly...
 01:30
Alterations in Blood Pressure
Hypertension (High blood pressure)
Hypertension occurs when blood pressure readings consistently exceed the normal range. It is diagnosed when systolic blood pressure (the top number, indicating pressure while the heart...
 01:18
Neural Regulation of Blood Pressure
Baroreceptor Reflex
Baroreceptors, located in the carotid sinuses and aortic arch, detect changes in blood pressure. When blood pressure rises, these stretch-sensitive receptors...
 01:14
The Parasympathetic Nervous System
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.