Related Experiment Video
Updated: Jul 28, 2026

Design and Use of a Low Cost, Automated Morbidostat for Adaptive Evolution of Bacteria Under Antibiotic Drug Selection
Published on: September 27, 2016
Monte Carlo simulation to optimize polymyxin B dosing regimens for the treatment of Gram-negative bacteremia
Yingying Yu1, Zheng He2, Chengcheng Wang1
1Department of Pharmacy, Qilu Hospital (Qingdao), Cheeloo College of Medicine, Shandong University, Qingdao, Shandong, China.

Objective:
This study aimed to predict and evaluate the efficacy of various polymyxin B dosing regimens for Gram-negative bacteremia using Monte Carlo simulation, with a specific focus on assessing the efficacy in patients receiving continuous renal replacement therapy (CRRT). The goal was to optimize clinical dosing regimens and guide rational polymyxin B use in practice.
Methods:
A total of 1,939 Gram-negative bacterial strains were analyzed, collected between April 2019 and December 2021 through the China Bloodstream Gram-negative Pathogens Antimicrobial Resistance and Virulence Surveillance Network (CARVIS-NET). Pharmacokinetic parameters of polymyxin B from existing literature were used to conduct a Monte Carlo simulation based on pharmacokinetic/pharmacodynamic (PK/PD) theory. The probability of target attainment (PTA) and cumulative fraction of response (CFR) were evaluated across various dosing regimens.
Results:
The main pathogens of Gram-negative bacteremia were Escherichia coli, Klebsiella pneumoniae, Pseudomonas aeruginosa, and Acinetobacter baumannii, all of which demonstrated high susceptibility to polymyxin B. For pathogens with a minimum inhibitory concentration (MIC) ≤1 mg/L, all regimens achieved PTA >90%. However, when the MIC increased to 2 mg/L, the PTA for the 500,000 IU q12h regimen decreased to 77.53%, and at an MIC of 4 mg/L, none of the dosing regimens achieved a PTA >90%. For P. aeruginosa and K. pneumoniae with MIC ≤0.5 mg/L, all regimens demonstrated effectiveness. However, at MIC ≥1 mg/L, significant declines in PTA were observed, with the 500,000 IU q12h and 1.25 mg/kg q12h regimens yielding suboptimal outcomes. In CRRT patients, PTA values declined further, particularly against K. pneumoniae, raising concerns about potential treatment failure.
Conclusion:
Polymyxin B demonstrates high efficacy for Gram-negative bacteremia with MIC ≤1 mg/L. However, efficacy diminishes as MIC increases, particularly for P. aeruginosa and K. pneumoniae, where 500,000 IU q12h and 1.25 mg/kg q12h regimens may result in suboptimal outcomes. For CRRT patients with K. pneumoniae bacteremia, therapeutic drug monitoring and dose adjustments are crucial to mitigate treatment failure risks.
More Related Videos
 11:17
Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
 06:19
Author Spotlight: Characterizing Airway Environments to Advance Model Systems and Antimicrobial Discovery in Cystic Fibrosis and Chronic Respiratory Infections
Published on: October 11, 2024
Related Concept Videos
 01:15
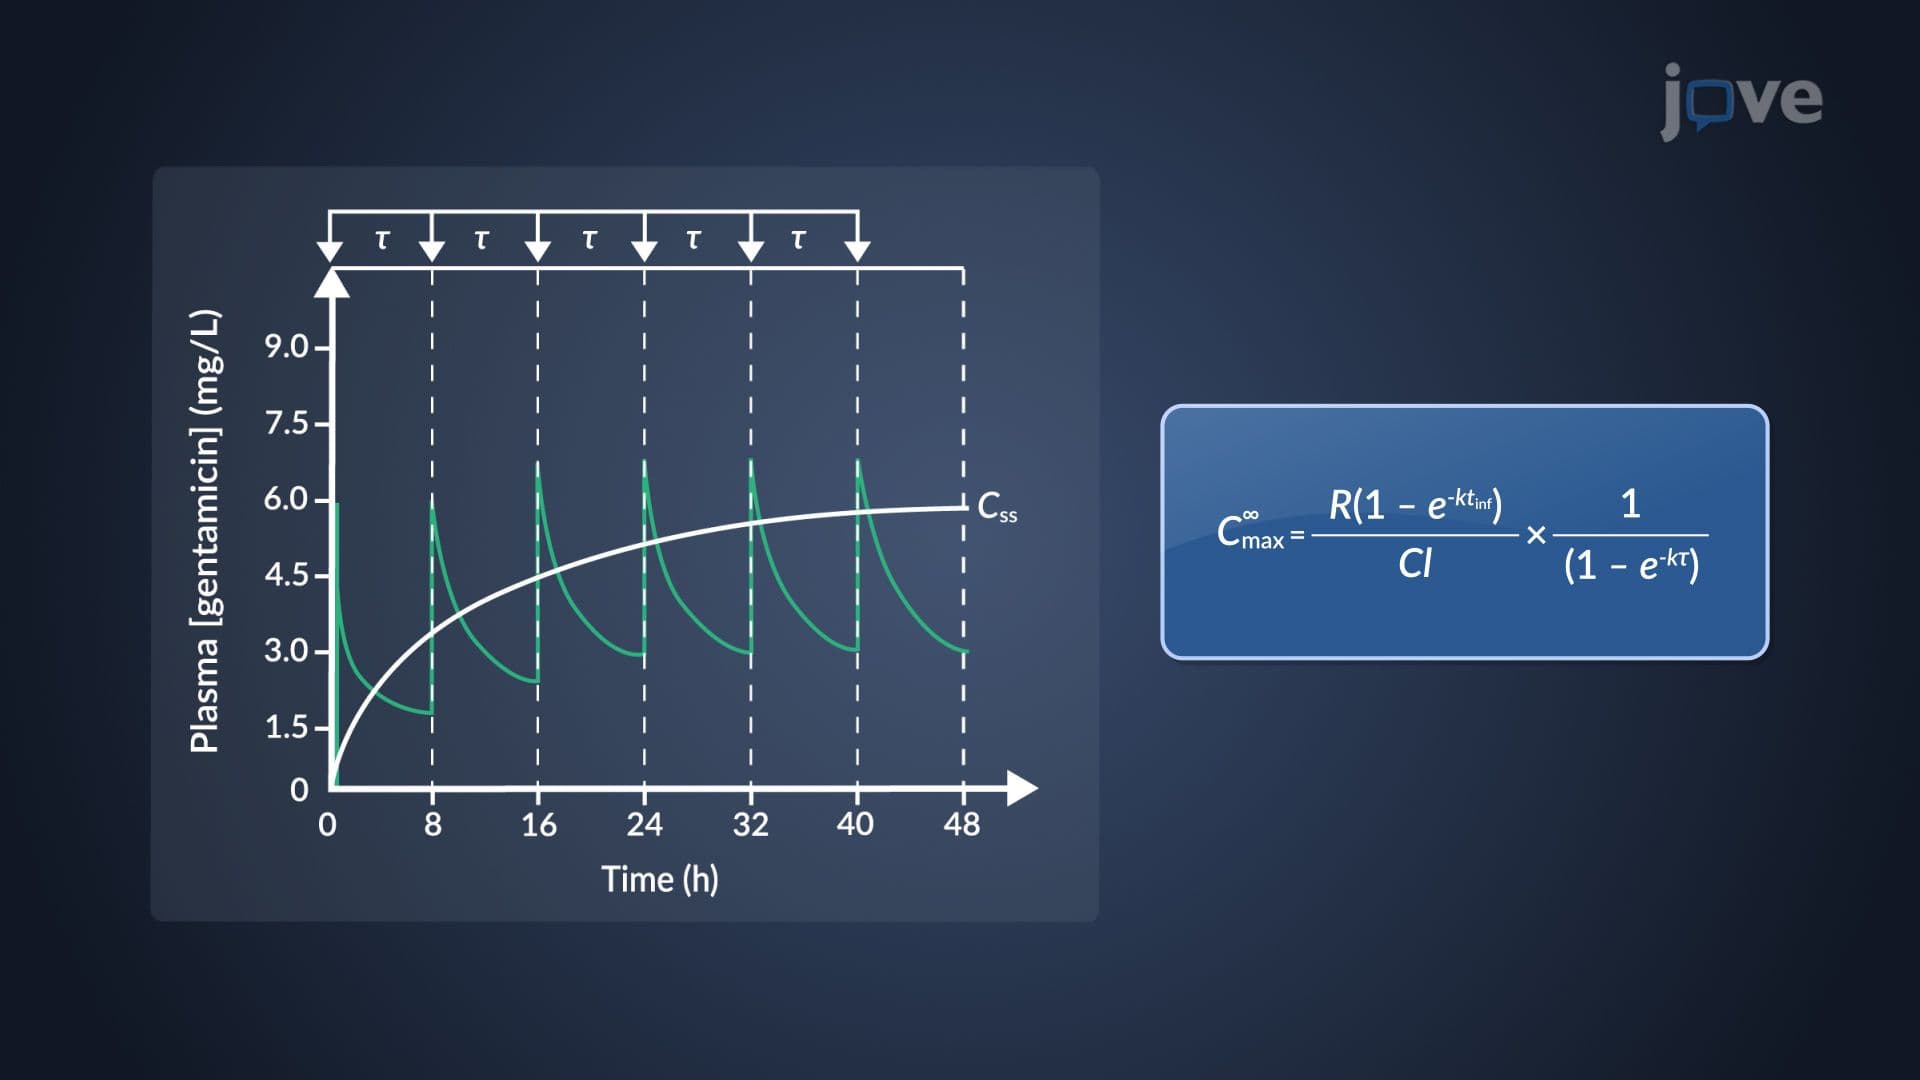
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:25
Clinical Significance of Antibiotic Resistance