
A Novel Radiofrequency-Assisted Trans-RAA Perforation Technique for Pericardial CO2 Insufflation to Facilitate
Pasquale Santangeli1, Nolan Hight1, Arwa Younis1
1Department of Cardiovascular Medicine, Heart, Vascular, and Thoracic Institute, Cleveland Clinic, Cleveland, Ohio, USA.

Background:
Perforation of a coronary venous branch for pericardial insufflation of carbon dioxide (CO2) enhances safety of epicardial access. The multiple procedural steps and length of the procedure remain a major limitation of this approach impacting its routine clinical adoption.
Objectives:
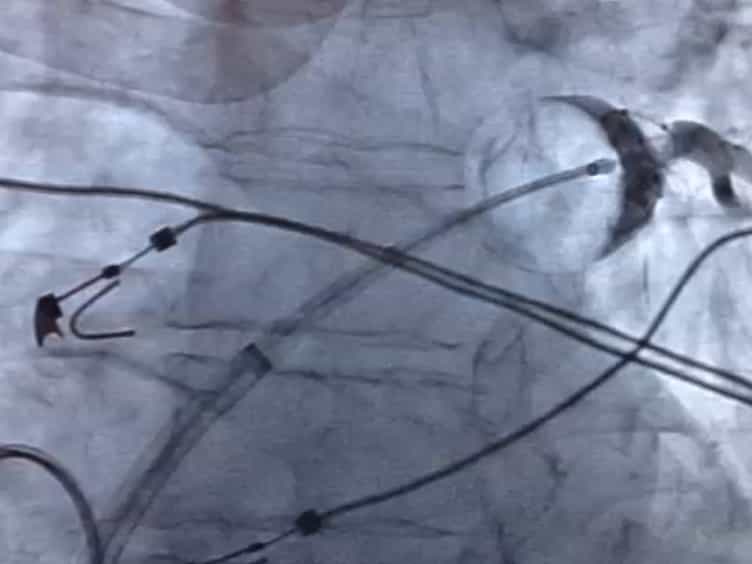
This study describes a novel and streamlined technique for pericardial CO2 insufflation via radiofrequency (RF)-assisted right atrial appendage (RAA) perforation.
Methods:
Between 2023 and 2024, 18 patients (age: 55 ± 11 years; left ventricular ejection fraction: 44 ± 13%) underwent epicardial access for mapping and ablation of ventricular arrhythmias facilitated by pericardial CO2 insufflation via a microperforation of the RAA with a custom-made telescopic crossing assembly consisting of a stiff 0.014-inch guidewire within 1.8-Fr microcatheter delivered inside a 4-F support catheter. The proximal end of the guidewire was connected to a unipolar RF generator (20-30 W in "cut mode", <1 s burst) to obtain a controlled RAA wall microperforation and facilitate advancement of the 1.8-F microcatheter in the pericardial space for CO2 insufflation.
Results:
Successful RAA exit with the RF guidewire-microcatheter assembly was achieved in all patients, and epicardial access was completed in 17 (94%) patients. In 1 patient, significant pericardial adhesions were detected after RAA exit, and epicardial access was deferred. The median time from femoral venous insertion of the catheter assembly to CO2 insufflation was 4 min (range: 3-7 min). Significant bleeding (>80 mL) occurred in 1 patient (patient #3; 150 mL), which led to a modification of the technique (shortening of the RF burst to <1 s with 1-2 mm guidewire exposure past the microcatheter and minimal advancement during RF). After technique modification (n = 15), pericardial bleeding ranged from 5 mL-30 mL (median: 10 mL; IQR: 5-20 mL). No patient had inadvertent right ventricle puncture or damage to a coronary artery. Three patients had pericardial pain after the procedure requiring 1 week of therapy with nonsteroidal anti-inflammatory drugs and colchicine.
Conclusions:
Intentional RAA perforation for pericardial CO2 insufflation with a custom RF guidewire-microcatheter assembly can be safely and efficiently performed to facilitate epicardial access for ventricular arrhythmias ablation.

