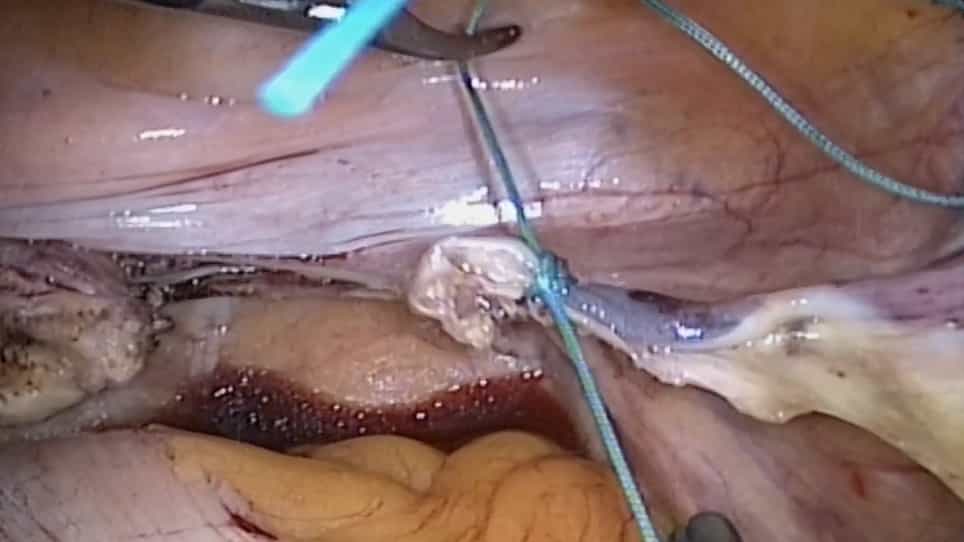
Related Experiment Video
Updated: May 22, 2025


Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Post-Caesarean Huge Isthmocele with Multiple Endometriomas and Cervical Stenosis: Laparoscopic Excision and Repair
Akkamahadevi C Hiremath1, Anuja Doolam1, K S Shivakumar1
1Department of Obstetrics and Gynaecology, Sri Sathya Sai Institute of Higher Medical Sciences, EPIP Area, Whitefield, Bengaluru, Karnataka 560066 India.

Background:
Cesarean scar defects or isthmoceles are increasingly detected in the recent times due to the rise in cesarean rates worldwide. They may develop due to poor healing at myometrial site. The pouch accumulates the menstrual blood and very rarely in long standing cases develops endometriomas in the wall.
Case Presentation:
A 30-year-old woman, para 1 living 1 with previous cesarean delivery 9 years back, presented to us with secondary infertility, chronic pelvic pain and post menstrual bleeding. A routine Transvaginal ultrasonography (TVS) showed a large fluid filled outpouching adjoining the uterine scar line, in communication with endometrial cavity. T2 weighted magnetic resonance Imaging (MRI) showed a huge isthmocele arising from the scar defect at lower uterine segment measuring 96 x 60 x52 mm with multiple endometrial rests in the wall showing shading and hypo intensity. The ishtmocele was laparoscopically excised and defect closed in two layers with hysteroscopic transillumination guidance. On hisptopathlogical examination, the lining of isthmocele had endocervical epithelium with thick fibromuscular tissue and focal areas of endometriosis. Postoperative period was uneventful and patient was discharged on third postoperative day. The patient was relieved of her pain abdomen and postmenstrual bleeding at 6 months follow-up.
Conclusion:
Laparoscopic approach is the preferred surgical technique in huge isthmoceles. Endometrioma develop within the wall of the pseudosac during natural course of the disease in longstanding ishthmoceles. Meticulous closure of uterine incision during cesarean section making sure that edges are taken properly into the stiches along with proper antibiotic coverage in cases with premature rupture of membranes (PROM) can prevent occurrence of isthmocele. Early diagnosis and surgical repair can prevent the progressive disease and Cesarean scar defect Syndrome.