Related Experiment Video
Updated: May 22, 2025
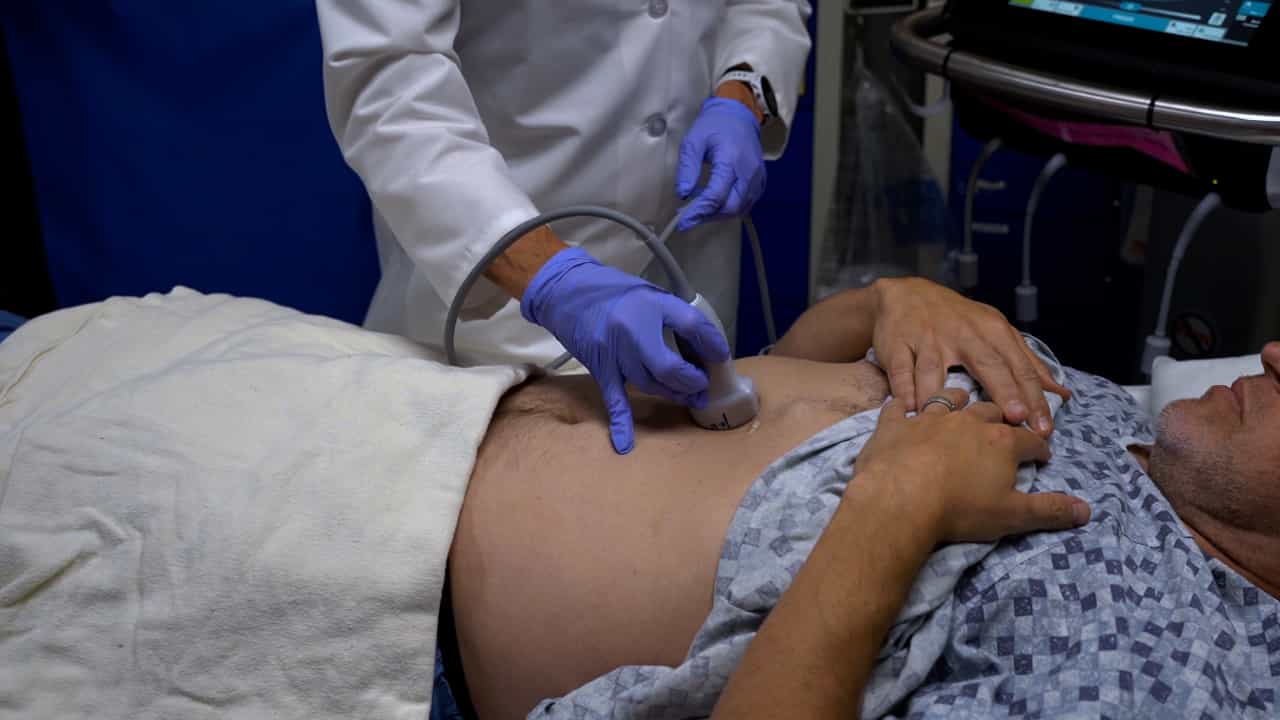
Author Spotlight: Point-of-Care Ultrasound for Gastric Content Assessment and Risk Stratification in Perioperative Care
Published on: September 22, 2023
Silent rupture: The hidden danger of gastric perforation in paediatric blunt trauma: A case report
Ayushi Chotra1, Vishal Bharadwaj2, Deepak Goel3
1Department of Paediatrics, Bristol Royal Hospital for Children, Bristol, United Kingdom.

Insights
A 5-year-old girl with isolated gastric perforation from blunt abdominal trauma after a fall made a full recovery. Early suspicion and timely surgical repair were key to managing this rare pediatric case.
Area of Science:
- Pediatric Surgery
- Trauma Surgery
- Gastrointestinal Surgery
Background:
- Blunt abdominal trauma is a significant cause of pediatric injury.
- Gastric perforation is a rare but life-threatening complication of blunt abdominal trauma.
Purpose of the Study:
- To report a rare case of isolated gastric perforation in a child following blunt abdominal trauma.
- To highlight the importance of prompt diagnosis and surgical management in pediatric gastric injuries.
Main Methods:
- Case presentation of a 5-year-old girl with severe abdominal symptoms post-fall.
- Diagnostic workup including physical examination, X-ray, and contrast-enhanced Computerised Tomography (CECT) scan.
- Emergency exploratory laparotomy with surgical repair of gastric laceration and peritoneal lavage.
Main Results:
- The CECT scan revealed ascites and pneumoperitoneum, indicating hollow organ perforation.
- Surgical repair of a 7 cm gastric laceration was successful.
- Postoperative management included intensive care with inotropic support and oxygen therapy for systemic inflammatory response syndrome (SIRS).
- The patient recovered without complications and was discharged on postoperative day 10.
Conclusions:
- Isolated gastric perforation from blunt abdominal trauma is uncommon in children.
- Early clinical suspicion, advanced imaging, and prompt surgical intervention are crucial for favorable outcomes.
- Multidisciplinary care, including pediatric intensive care, is vital for managing post-operative complications like SIRS.
Abstract:
We present herein a case with the relatively uncommon presentation of isolated gastric perforation resulting from blunt trauma of the abdomen following a fall shortly after eating in a 5-year-old girl. The child experienced severe abdominal pain, tachycardia, hypotension, and shortness of breath. A physical examination revealed epigastric tenderness and abdominal distension. Initial X-ray was non-diagnostic, and a contrast-enhanced Computerised Tomography [CECT scan] demonstrated ascites and pneumoperitoneum that suggested hollow organ perforation. The emergency exploratory laparotomy revealed a 7 cm laceration on the stomach that was surgically repaired using two-layer closure. Following that, extensive peritoneal lavage occurred. In the postoperative period, the patient developed systemic inflammatory response syndrome [SIRS]. Hence, the PICU provided inotropic support and oxygen therapy. On the fourth day, she became significantly improved, and on the tenth day, we made her able to go home without any complications. The important points in the management of gastric perforation in paediatric blunt abdominal trauma are early suspicion, further imagination, and timely surgical intervention.


Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus....
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:28
Peptic Ulcer Disease II: Pathophysiology
Damaging agents such as Helicobacter pylori, gastric acid, pepsin, and nonsteroidal anti-inflammatory drugs (NSAIDs) can weaken the mucosal defense, allowing hydrogen ions to infiltrate back and harm epithelial cells.