Related Experiment Video
Updated: May 21, 2025
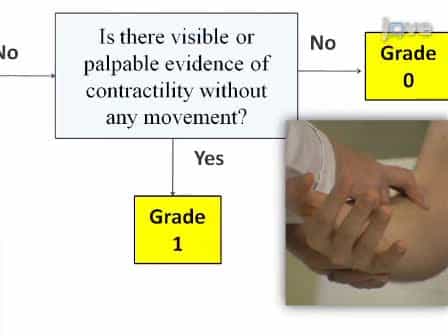

Manual Muscle Testing: A Method of Measuring Extremity Muscle Strength Applied to Critically Ill Patients
Published on: April 12, 2011
Respiratory and limb muscles' ability to repeatedly generate maximal isometric strength in patients with intensive
Margaux Machefert1,2, Guillaume Prieur3,4, Solène Aubry5
1Physiotherapy Department, Le Havre Hospital, Le Havre, F-76600, France. margaux.machefert@ch-havre.fr.

Background:
Intensive care unit-acquired weakness (ICU-Aw) is a prevalent complication in critically ill patients, affecting both limb and respiratory muscles, individually or concurrently. The precise mechanisms by which muscle weakness influences the distinct functional roles of each muscle group remain to be fully elucidated. The objective of this study was to compare the time course evolution of inspiratory and quadriceps muscles strength during repeated maximal isometric contractions in patients with limb muscles and inspiratory muscles weakness.
Methods:
A single-center, observational study was conducted in critically ill patients after extubation, presenting with both inspiratory and limb muscle weakness (defined as maximal inspiratory pressure (Pimax) < 30 cmH2O and an MRC score < 48). The patients' ability to sustain maximal voluntary effort was measured using electronic manometers and dynamometers, with repeated efforts performed 10 times. Following each measurement, a 10-second rest period was observed, and strength measurements were repeated to evaluate recovery.
Results:
A total of 20 patients (90% male, mean age 61 ± 10 years, SAPS II score 28 ± 17) were included. The mean first maximal inspiratory pressure was 32.6 ± 17 cmH2O, and the mean first quadriceps maximal force was 135 ± 90 Newtons (N). Investigation revealed a decline in quadriceps muscle force of -15.45 ± 28.61 N (95% CI: -28.84 to -2.05) while inspiratory muscles demonstrated stability (mean difference: 1.75 ± 7.57 cmH2O (95% CI: -1.80 to 5.30)). A statistically significant interaction between time and muscle group was identified (p = 0.0017), suggesting a different time course evolution of maximal voluntary strength between muscle groups. After a one-minute recovery, significant improvement in quadriceps strength was observed (p = 0.009), while no statistically significant change was detected in inspiratory muscle strength (p = 0.16).
Conclusions:
The results of this study indicate potential disparities in the maximum force maintenance capacity between the quadriceps muscles and inspiratory muscles in patients with ICU-acquired weakness.
Trial Registration:
Registered on ClinicalTrials.gov Identifier NCT05396066.
More Related Videos
 09:24
Repeated Measurement of Respiratory Muscle Activity and Ventilation in Mouse Models of Neuromuscular Disease
Published on: April 17, 2017
 09:37
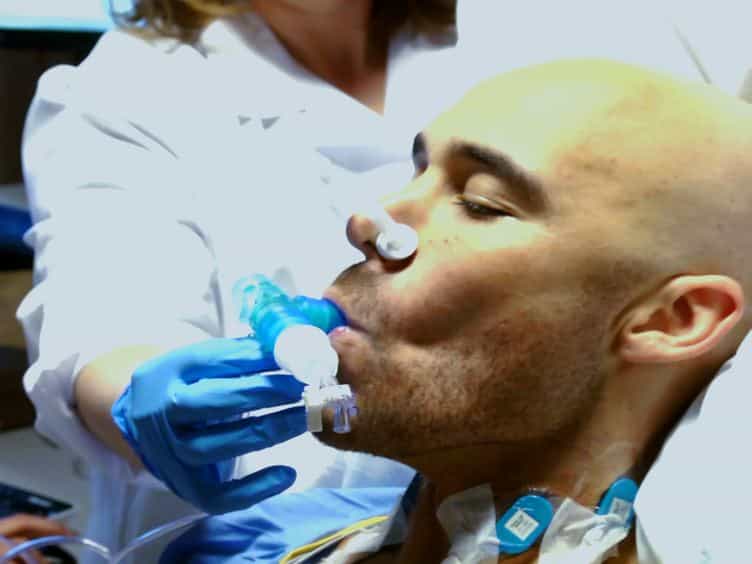
Evaluation of Respiratory Muscle Activation Using Respiratory Motor Control Assessment RMCA in Individuals with Chronic Spinal Cord Injury
Published on: July 19, 2013
Related Concept Videos
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration...
 01:21
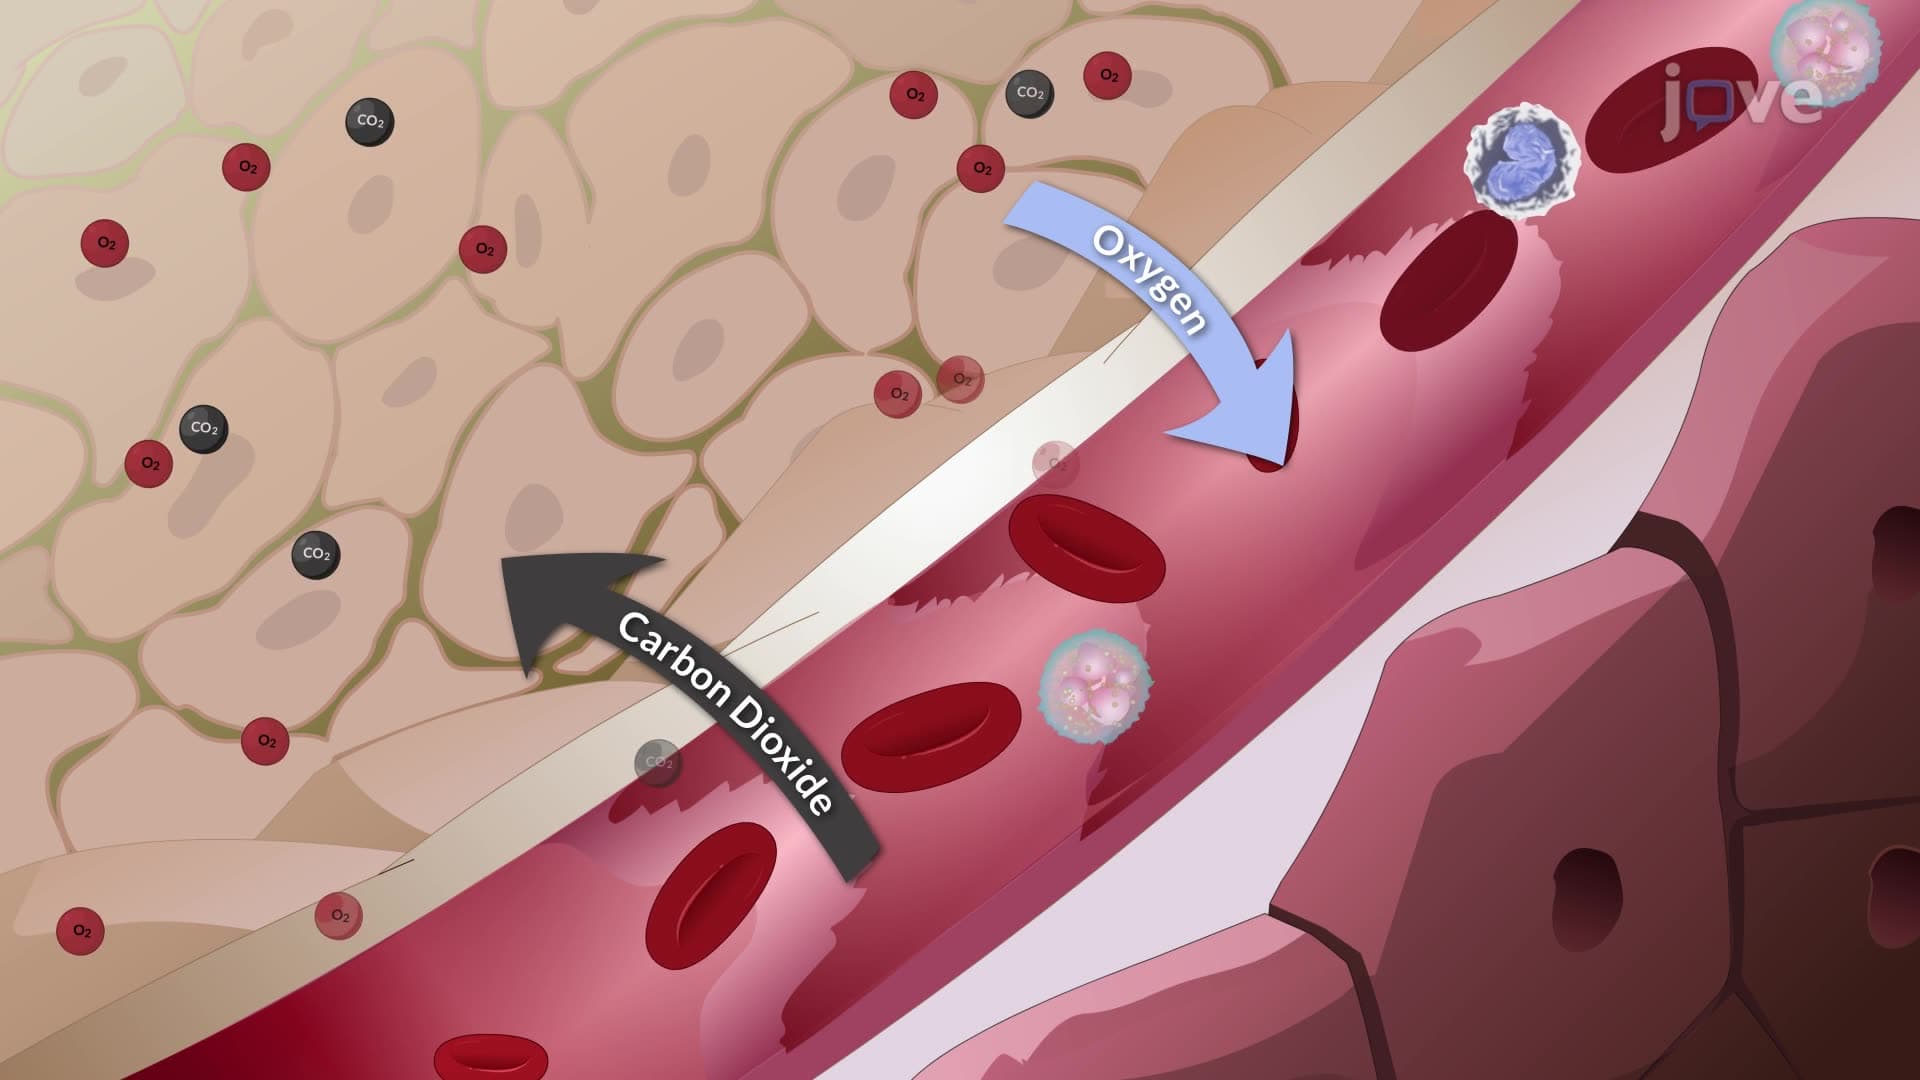
Mechanism of Breathing III: The Accessory Muscles
The respiratory system is a complex network that relies on primary respiratory muscles like the diaphragm, but also involves accessory muscles to enhance lung expansion and airflow during both inhalation and exhalation.
Enhancing Inhalation with Accessory Muscles:
Accessory muscles such as the sternocleidomastoid, scalene, intercostal, and abdominal muscles are crucial when additional respiratory effort is required, such as during deep...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:23
Acute Respiratory Failure-IV
 01:30
Acute Respiratory Failure-III