Related Experiment Video
Updated: May 20, 2025
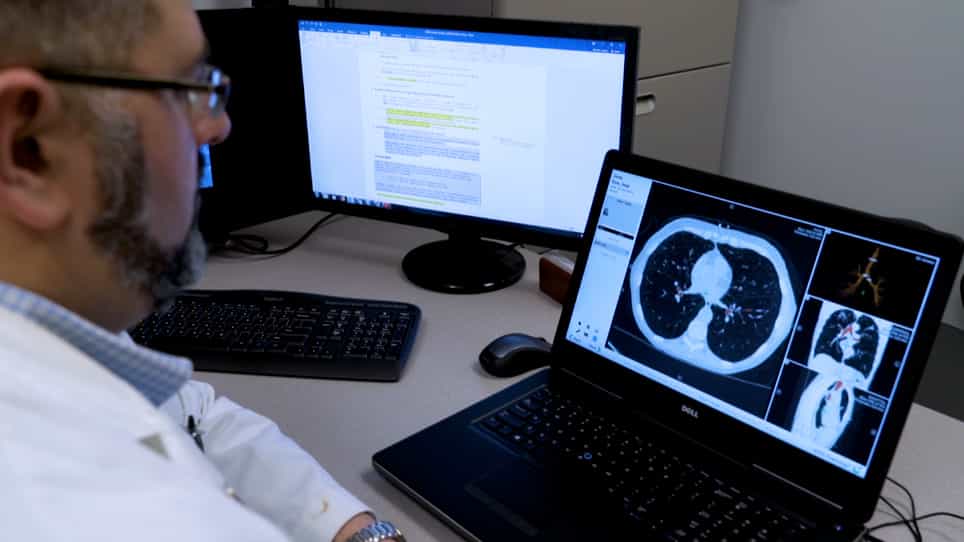

Electromagnetic Navigation Transthoracic Nodule Localization for Minimally Invasive Thoracic Surgery
Published on: May 4, 2022
One-Stage Bilateral Pulmonary Nodule Resection via Unilateral Thoracic Cavity Access: A Single-Center Experience of
Zhen Wang1, Zhaolei You1, Yingjian Song1
1Department of Thoracic Surgery, Yantai Yuhuangding Hospital, Qingdao University, Yantai, People's Republic of China.

Background:
Surgical intervention remains the primary therapeutic modality for managing multiple pulmonary nodules. However, in cases with bilateral pulmonary nodules, one-stage bilateral resection is discouraged due to tumor aggressiveness and surgical invasiveness. In light of this, we investigated an innovative approach, termed one-stage bilateral pulmonary nodule resection via unilateral thoracic cavity access.
Methods:
From July 2022 to September 2024, a cohort of 12 patients with bilateral pulmonary nodules were enrolled in this study. This technique involves initial unilateral transcostal incision for segmental or lobectomy of a nodule on one side, followed by bilateral mediastinal pleura incision through the anterior mediastinum, facilitating subsequent wedge resection of the contralateral nodule. Clinical and pathological data, along with perioperative imaging findings and follow-up information, were systematically collected and subjected to a comprehensive retrospective analysis.
Results:
A total of 25 nodules were resected from 12 patients. Regarding surgical approaches, nine patients underwent right thoracic incision, while three patients underwent left thoracic incision. Intraoperatively, seven patients received bilateral wedge resections, whereas five patients underwent segmentectomy on one side combined with wedge resection on the contralateral side. R0 resection of the contralateral nodules was successfully achieved during the procedures. The average distance between the surgical margin and the contralateral nodules was 12.5 mm, ranging from 5 mm to 25 mm. Of the 12 patients, one (Patient 6) was lost to follow-up, while the remaining 11 patients underwent postoperative chest CT examinations. The median follow-up duration for these 11 patients was 105 days (range: 36-857 days). No evidence of bilateral pleural effusion or tumor recurrence was detected on follow-up chest CT scans.
Conclusions:
This study offers the potential to concurrently address bilateral pulmonary nodules, thereby sparing patients from the need for a subsequent hospitalization for surgical intervention.

