Related Experiment Video
Updated: May 20, 2025


Improved Renal Denervation Mitigated Hypertension Induced by Angiotensin II Infusion
Published on: May 26, 2022
Impact of intensive blood pressure control on kidney outcomes
Jia Xin Huang1, Vanessa-Giselle Peschard2,3, Elaine Ku4,5
1Department of Pediatrics, Division of Critical Care, University of California San Francisco.

Insights
Intensive blood pressure (BP) control offers cardiovascular benefits for patients with chronic kidney disease (CKD). However, its impact on kidney outcomes is mixed, with benefits seen in later stages (CKD 4-5) but not earlier stages (CKD 3).
Area of Science:
- Nephrology
- Cardiology
- Clinical Trials
Background:
- Hypertension is a key modifiable risk factor for cardiovascular events.
- The role of intensive blood pressure (BP) control in slowing chronic kidney disease (CKD) progression remains under investigation.
- Evidence from high-quality trials is crucial for guiding clinical practice.
Purpose of the Study:
- To review current evidence on the effects of intensive BP control on kidney outcomes in patients with CKD.
- To focus on trial-grade evidence to clarify the benefits and risks of intensive BP management.
- To provide an update on the ongoing debate regarding BP targets in CKD patients.
Main Methods:
- Analysis of recent large-scale clinical trials from China evaluating intensive BP control.
- Individual-level meta-analyses of six trials comparing different BP control strategies in CKD patients.
- Focus on trial-grade evidence to assess impact on kidney outcomes.
Main Results:
- Three recent Chinese trials showed cardiovascular benefits with intensive BP control.
- These trials reported mixed results regarding the risk of adverse kidney outcomes.
- Meta-analyses indicated intensive BP control reduced kidney replacement therapy risk in CKD stages 4-5, but not in CKD stage 3.
Conclusions:
- Current guidelines often recommend a systolic BP target of 120-130 mmHg for CKD patients due to cardiovascular benefits.
- Intensive BP control strategies may pose potential risks to kidney health.
- Further research is needed to optimize BP management for diverse CKD populations.
Purpose Of Review:
Hypertension has long been recognized as a modifiable risk factor for cardiovascular events. However, the role of intensive blood pressure (BP) control in preventing kidney disease progression continues to be debated. This review will provide a brief update on the evidence in support of or against the intensive control of BP on kidney outcomes in patient with chronic kidney disease (CKD), focusing particularly on trial-grade evidence.
Recent Findings:
Recently, three large trials conducted in China compared the effects of intensive BP control in adults with cardiovascular risk factors. All three trials demonstrated that intensive BP control confers cardiovascular benefits, but mixed results were noted in terms of the risk of adverse kidney outcomes. In individual-level meta-analyses of six trials of different BP control strategies in patients with CKD, intensive BP control appeared to reduce the risk of kidney replacement therapy in those with CKD stage 4-5, but not in patients with CKD stage 3.
Summary:
Most guidelines continue to recommend a systolic BP target of 120-130 mmHg for patients with CKD given the cardiovascular benefits observed in trials of intensive BP control, though there are some signals of potential risks to the kidney with this BP treatment strategy.


Related Concept Videos
 01:18
Hypertension and Regulation of Blood Pressure
 01:25
Antihypertensive Drugs: Direct Renin Inhibitors
 01:30
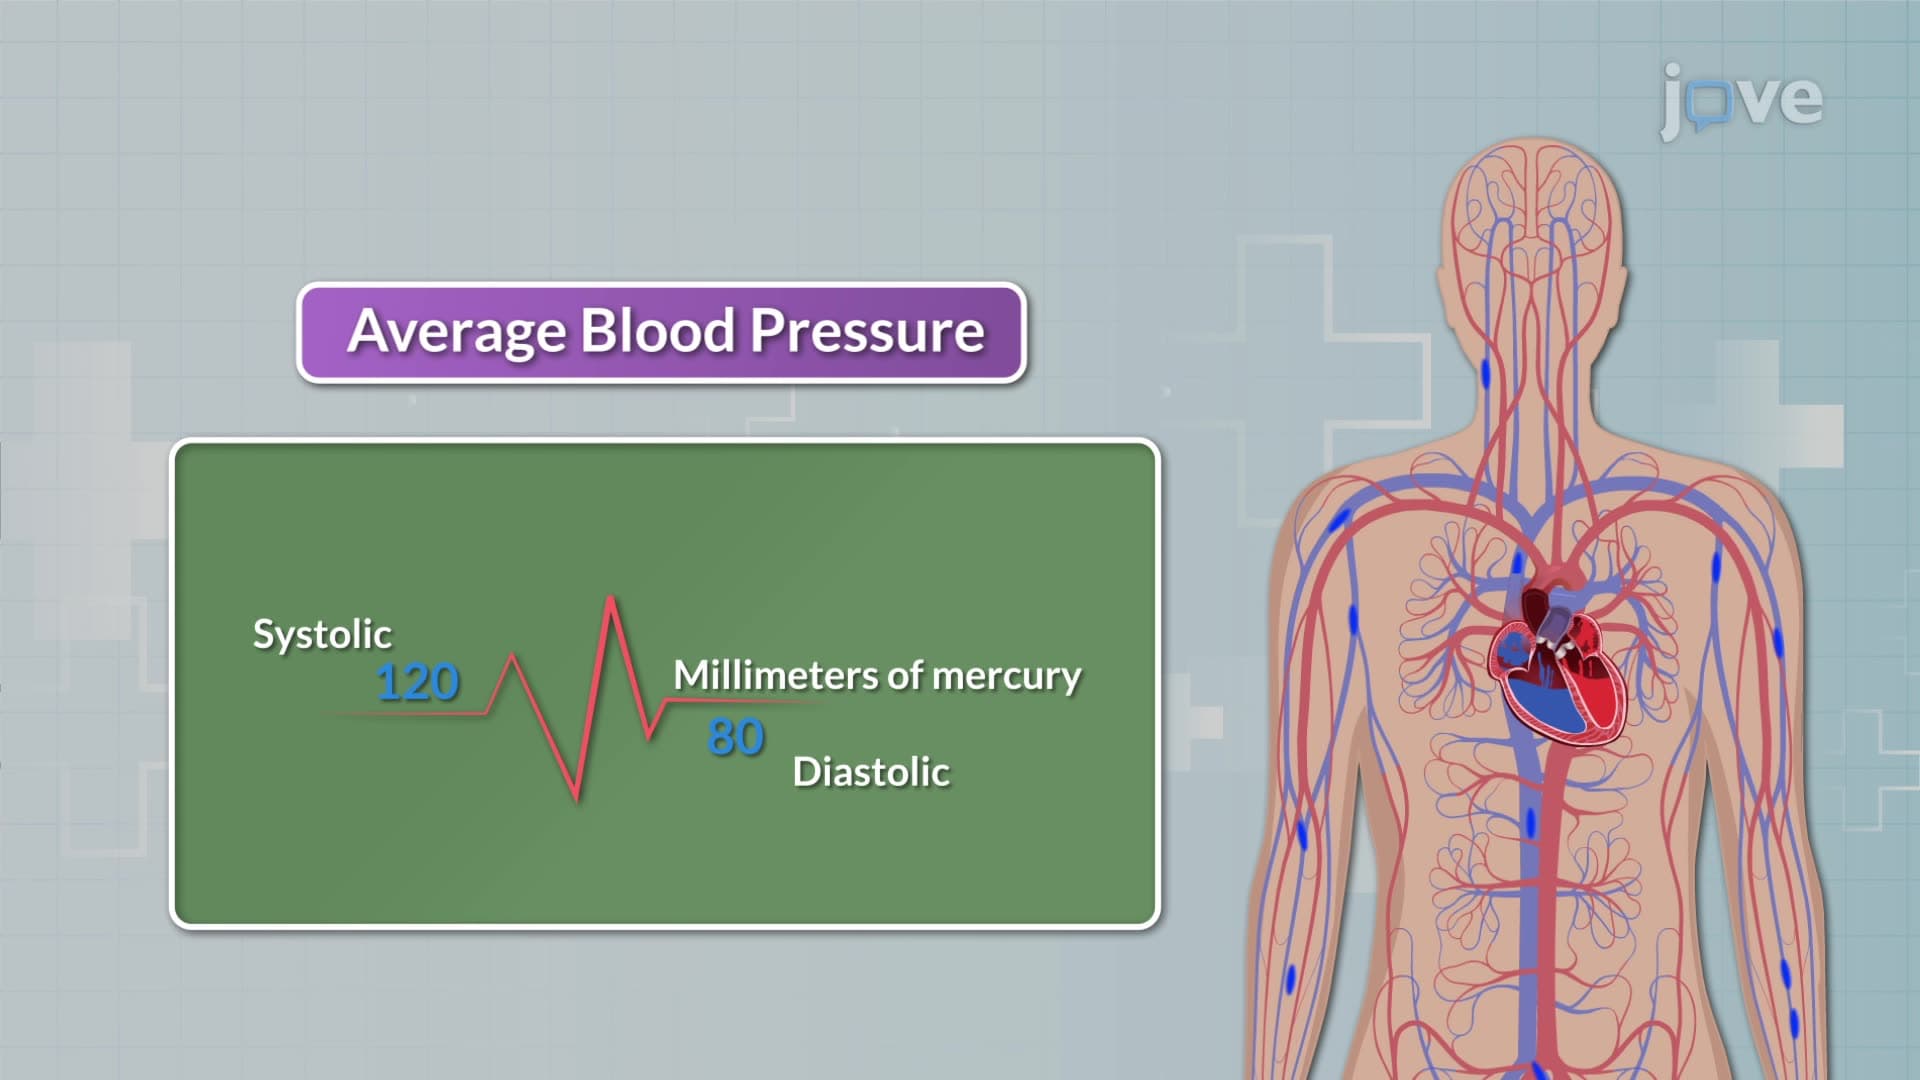
Blood Pressure
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the...
 01:30
Antihypertensive Drugs: Angiotensin-Converting Enzyme Inhibitors
 01:33
Hormonal Regulation
 01:28
Factors affecting Blood pressure
Physiological Factors: