Related Experiment Video
Updated: May 20, 2025
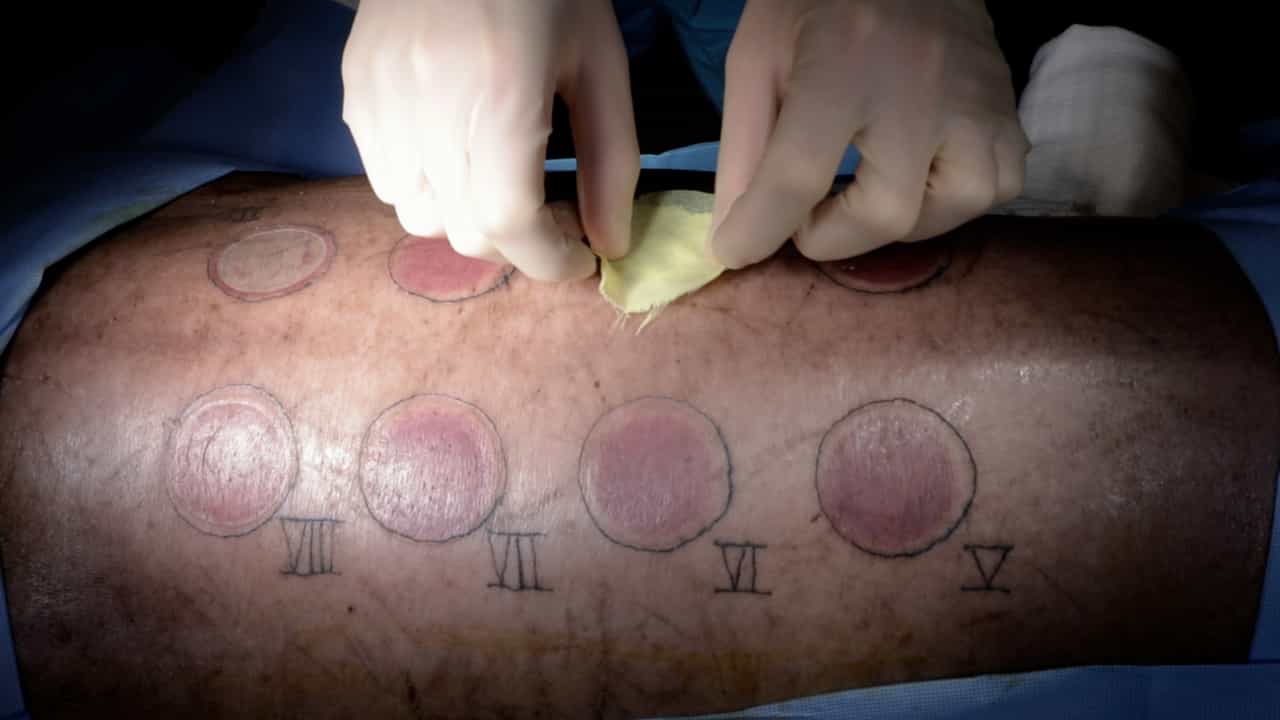

Author Spotlight: A Multi-Depth Porcine Model for Comprehensive Study of Burn Injuries and Healing Processes
Published on: February 23, 2024
Atypical care of burned patients is typical in war: Adapting old dogma for maximal survival
Peter Sienko1, Gary A Vercruysse1
1University of Michigan, Ann Arbor, MI.

During the wars in Iraq and Afghanistan, US troops experienced burns were stabilized and quickly evacuated out of theater to Germany and then to the US Army Institute of Surgical Research in San Antonio, Texas. This was not true of casualties involving non-US or non-North Atlantic Treaty Organization soldiers and medical systems. In such situations, soldiers and civilians alike were treated in North Atlantic Treaty Organization medical treatment facilities and/or were transferred to host nation health care facilities until they healed or died from their wounds. Before 1970, most burns worldwide were treated conservatively and managed with some form of resuscitation and dressing changes. Debridement and skin grafting were reserved for burn wounds that became infected or granulated after separation of the burn wound eschar. This treatment algorithm was developed because of a lack of modern equipment (such as a dermatome or skin mesher) and partly because of adherence to dogmatic principles adopted for the previous century of battlefield burn wound treatment. Modern burn care standards in developed countries have advanced dramatically in the last several decades. However, employing these standards in under-resourced and overburdened hospital systems, such as those in the combat environment, will lead to a waste of resources and unnecessary loss of life. The following is a primer to burn care in war, tailored for providers in austere systems, that will maximize survival, help obviate the need for intensive care unit care, and save valuable resources and hospital bedspace.
During the wars in Iraq and Afghanistan, US troops experienced burns were stabilized and quickly evacuated out of theater to Germany and then to the US Army Institute of Surgical Research in San Antonio, Texas. This was not true of casualties involving non-US or non-North Atlantic Treaty Organization soldiers and medical systems. In such situations, soldiers and civilians alike were treated in North Atlantic Treaty Organization medical treatment facilities and/or were transferred to host nation health care facilities until they healed or died from their wounds. Before 1970, most burns worldwide were treated conservatively and managed with some form of resuscitation and dressing changes. Debridement and skin grafting were reserved for burn wounds that became infected or granulated after separation of the burn wound eschar. This treatment algorithm was developed because of a lack of modern equipment (such as a dermatome or skin mesher) and partly because of adherence to dogmatic principles adopted for the previous century of battlefield burn wound treatment. Modern burn care standards in developed countries have advanced dramatically in the last several decades. However, employing these standards in under-resourced and overburdened hospital systems, such as those in the combat environment, will lead to a waste of resources and unnecessary loss of life. The following is a primer to burn care in war, tailored for providers in austere systems, that will maximize survival, help obviate the need for intensive care unit care, and save valuable resources and hospital bedspace.

Related Concept Videos
 01:22
Burn Injuries
The damage results in the death of skin cells, which can lead to a massive loss of fluid. Dehydration, electrolyte imbalance, and renal and circulatory failure follow, which can be fatal. Burn patients are treated with intravenous fluids to offset...
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:29
Decreased Body Temperature
 01:26
Flail Chest-II
Assessment:
1. Clinical Evaluation:
History:
 01:30
Pneumonia V: Nursing management and Prevention
The nurse must practice strict medical asepsis and adhere to infection control guidelines to minimize healthcare-associated infections.
Enhance airway patency
Position the patient correctly to facilitate drainage of the affected lung segments. Manual or mechanical percussion and vibration can also be employed....
 01:22
Methods of reducing fever
Pharmacological Methods of Reducing Fever: