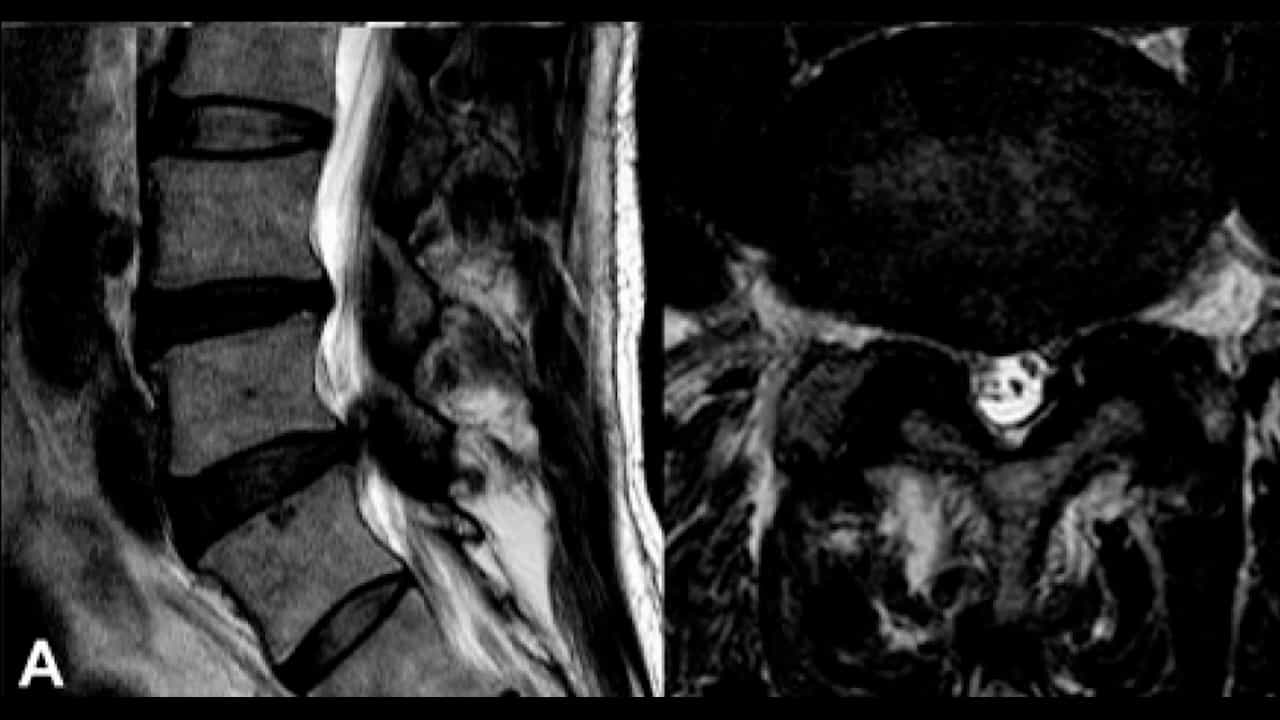
Related Experiment Video
Updated: May 5, 2026
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
Effect of Vertebral Morphology on Radiographic and Symptomatic Lumbar Spinal Stenosis in Patients Undergoing
Kusushi Murai1, Shizumasa Murata1, Hiroki Iwahashi2
1Department of Orthopedic Surgery, Wakayama Medical University, Wakayama, JPN.

Abstract:
Purpose Lumbar spinal stenosis (LSS) is a degenerative condition characterized by spinal canal narrowing, often leading to nerve compression and significantly impairing quality of life, particularly in older adults. Magnetic resonance imaging (MRI) is the gold standard for diagnosing LSS; however, radiographic evidence of stenosis often does not align with clinical symptoms, complicating management. We explored the relationship between vertebral morphology and both radiographic and symptomatic stenosis, hypothesizing that specific vertebral shapes, particularly oval (O) morphology, increase the risk of symptomatic stenosis. Methods This retrospective cohort study included patients who underwent microendoscopic decompression surgery between 2010 and 2022. Vertebral morphology was classified as bean (B), plane (P), or oval (O) based on MRI assessments of the posterior vertebral wall. Radiographic stenosis was identified based on MRI findings using the Schizas classification, whereas symptomatic stenosis required a correlation with clinical symptoms, such as neurogenic claudication or radicular pain confirmed through physical examination and functional diagnostics. Levels with radiographic stenosis that lacked clinical correlation were categorized as asymptomatic stenosis. The primary outcome was the prevalence of radiographic and symptomatic stenoses across different vertebral morphology groups. Secondary outcomes included the influence of patient demographics and morphology on stenosis at various lumbar levels. Statistical analyses included Chi-square tests and multivariate logistic regression, with p-values <0.05 considered significant. Results A total of 234 patients (105 females and 129 males; mean age: 72.2 years) were included. Radiographic stenosis prevalence increased progressively from L1/2 to L4/5, with the highest rate at L4/5 (167/234, 71.4%). Among these cases, symptomatic stenosis was observed in 86.2% (144/167), with O morphology showing the strongest association (79/86, 91.2%), followed by P morphology (65/81, 80.2%). By contrast, B morphology had the lowest prevalence of radiographic stenosis (10/103, 9.7%) and the weakest correlation with symptomatic outcomes (2/38, 5.3%). Overall, 265/337 (78.6%) of radiographic stenosis cases were symptomatic, whereas 72/337 (21.4%) remained asymptomatic despite MRI findings, highlighting the gap between imaging findings and clinical symptoms. Multivariate analysis confirmed that O morphology was significantly associated with symptomatic stenosis (odds ratio: 3.45; 95% CI: 2.10-5.67; p<0.001), underscoring the influence of vertebral morphology on symptomatic presentation. Conclusions Vertebral morphology was observed to influence the prevalence and severity of both radiographic and symptomatic stenosis. The O morphology demonstrated a higher prevalence of symptomatic stenosis, particularly at the L4/5 level, whereas the B morphology was associated with the lowest prevalence. These findings suggest that incorporating vertebral morphology into diagnostic evaluations and treatment planning for patients with LSS may enhance alignment between imaging findings and clinical presentations, facilitating more accurate prognostic assessments and tailored strategies.