Related Experiment Video
Updated: May 4, 2026


A Conditioned Place Preference Protocol for Measuring Incubation of Craving in Rats
Published on: November 6, 2018
Comparative Safety of Short-Acting Opioid Dose Escalation and Long-Acting Opioid Initiation in Nursing Home Residents
Anthony P Nunes1, Heeyoon Jung1, Yiyang Yuan1
1Department of Population and Quantitative Health Sciences, Division of Epidemiology, UMass Chan Medical School, Worcester, Massachusetts, USA.

Background:
For patients with continued pain while receiving an initial course of a short-acting opioid (SAO), clinicians may intensify the opioid regimen by escalating the SAO dose or initiating a long-acting opioid (LAO). The objective of this study was to assess the comparative safety of opioid intensification regimens in nursing home residents with nonmalignant pain.
Methods:
We conducted a retrospective cohort analysis of US long-stay nursing home residents identified from the national Minimum Data Set (MDS) 3.0 and linked Medicare data, 2011-2016. Opioid regimen changes were assessed using Part D claims to identify dose escalation of SAO, adding LAO to SAO, or a switch from SAO to LAO. The outcomes of interest were hospitalized falls/fractures and delirium identified in the MDS or hospitalization. Resident attributes were described by opioid regimen. Hazard ratios of study outcomes were quantified using as-treated (primary analysis) and intent-to-treat (secondary analysis) doubly robust inverse probability of treatment (IPT) weighted Fine & Gray regression models with a competing risk of death.
Results:
In the as-treated analysis, relative to residents in the SAO escalation cohort, the hazard of delirium was elevated in the LAO cohorts (aHR [LAO switch]: 2.05, 95% CI: 1.57-2.67; aHR [LAO add-on]: 1.55, 95% CI: 1.23-1.96). Results for falls and fractures were inconclusive. We did not observe evidence of an association with falls and fractures in the primary as-treated analysis; however, the intent-to-treat analysis observed increased hazards in the LAO switch cohort relative to the SAO escalation cohort (aHR 2.86, 95% CI:1.64-4.99).
Conclusions:
There is limited evidence to inform the clinical judgment between escalating the SAO dose or incorporating a LAO. Our study suggests increased risks of delirium in nursing home residents with nonmalignant pain when switching or adding an LAO to the opioid regimen relative to increasing the dose of SAOs.
Related Concept Videos
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:25
Analgesia and Pain Management
 01:15
Opioid Analgesics: Synthetic and Semisynthetic Opioids
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:24
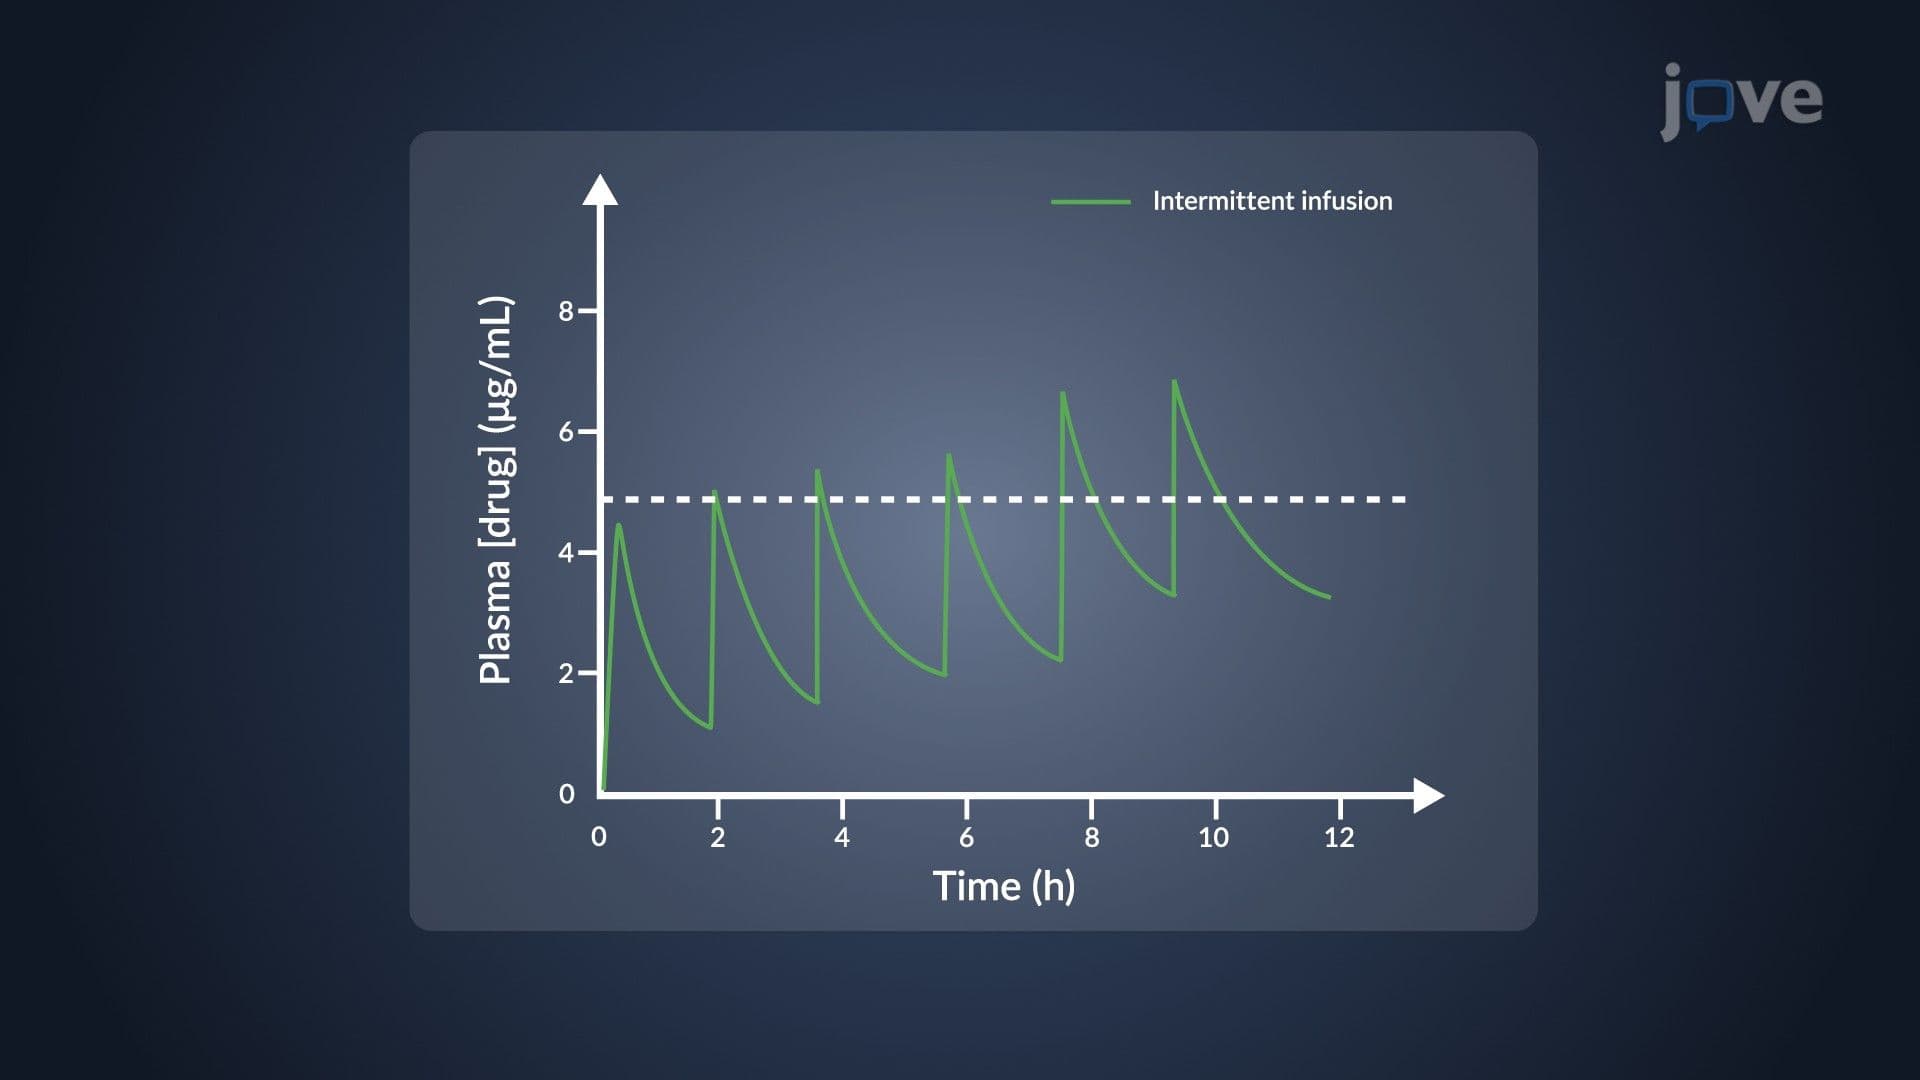
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:15
Drug Dosing: Geriatric Patients