Related Experiment Video
Updated: Jun 23, 2026
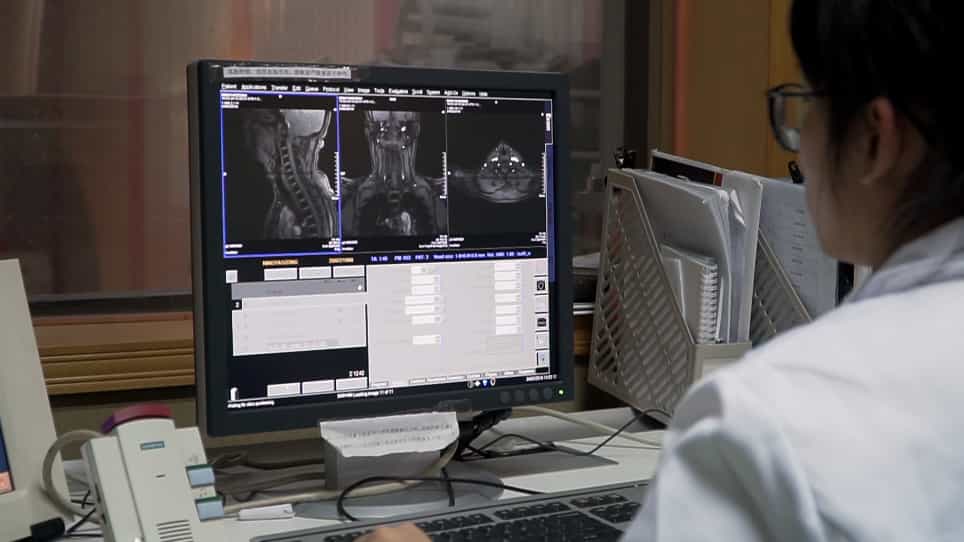

Diffusion Tensor Magnetic Resonance Imaging in Chronic Spinal Cord Compression
Published on: May 7, 2019
Using deep learning to enhance reporting efficiency and accuracy in degenerative cervical spine MRI
Aric Lee1, Junran Wu2, Changshuo Liu2
1Department of Diagnostic Imaging, National University Hospital, 5 Lower Kent Ridge Rd, 119074, Singapore.

Background Context:
Cervical spine MRI is essential for evaluating degenerative cervical spondylosis (DCS) but is time-consuming to report and subject to interobserver variability. The integration of artificial intelligence in medical imaging offers potential solutions to enhance productivity and diagnostic consistency.
Purpose:
To assess whether a transformer-based deep learning model (DLM) can improve the efficiency and accuracy of radiologists in reporting DCS MRIs.
Study Design/Setting:
Retrospective study using external DCS MRIs from December 2015 to August 2018.
Patient Sample:
The test dataset comprised 50 preoperative DCS MRIs (2,555 images) from 50 patients (mean age = 60 years ± SD 14; 13 women [26%]), excluding cases with instrumentation.
Outcome Measures:
Primary outcomes were interpretation time and interobserver agreement (Gwet's kappa) among radiologists grading spinal canal and neural foramina stenosis with and without DLM-assistance.
Methods:
A transformer-based DLM was used to classify spinal canal (grades 0/1/2/3) and neural foramina (grades 0/1/2) stenosis at each disc level. Two experienced musculoskeletal radiologists (both with 12-years-of-experience) provided reference standard labels in consensus. Ten radiologists (0-7 years of experience) graded DCS MRIs with and without DLM-assistance, with a 1-month washout period between sessions to minimize recall bias. Interpretation time and interobserver agreement were assessed.
Results:
DLM-assistance significantly improved interpretation time by 69 to 308 s (p<.001), reducing mean time from 159-490 s (SD 27-649) to 90-182 s (SD 42-218). Radiology residents experienced the largest time savings. DLM-assistance improved interobserver agreement across all stenosis gradings compared to baseline. For dichotomous spinal canal grading, residents had the largest improvement in agreement (κ = 0.63 to 0.77, p<.001). Conversely, for dichotomous neural foramina grading, musculoskeletal radiologists had the largest improvement (κ=0.60 to 0.72, p<.001). Notably, independent DLM performance alone was equivalent or superior to all readers.
Conclusions:
The integration of a deep learning model into the radiological assessment of DCS MRI improved radiologists' interpretation time and interobserver agreement, regardless of experience level.

