Related Experiment Video
Updated: May 16, 2025
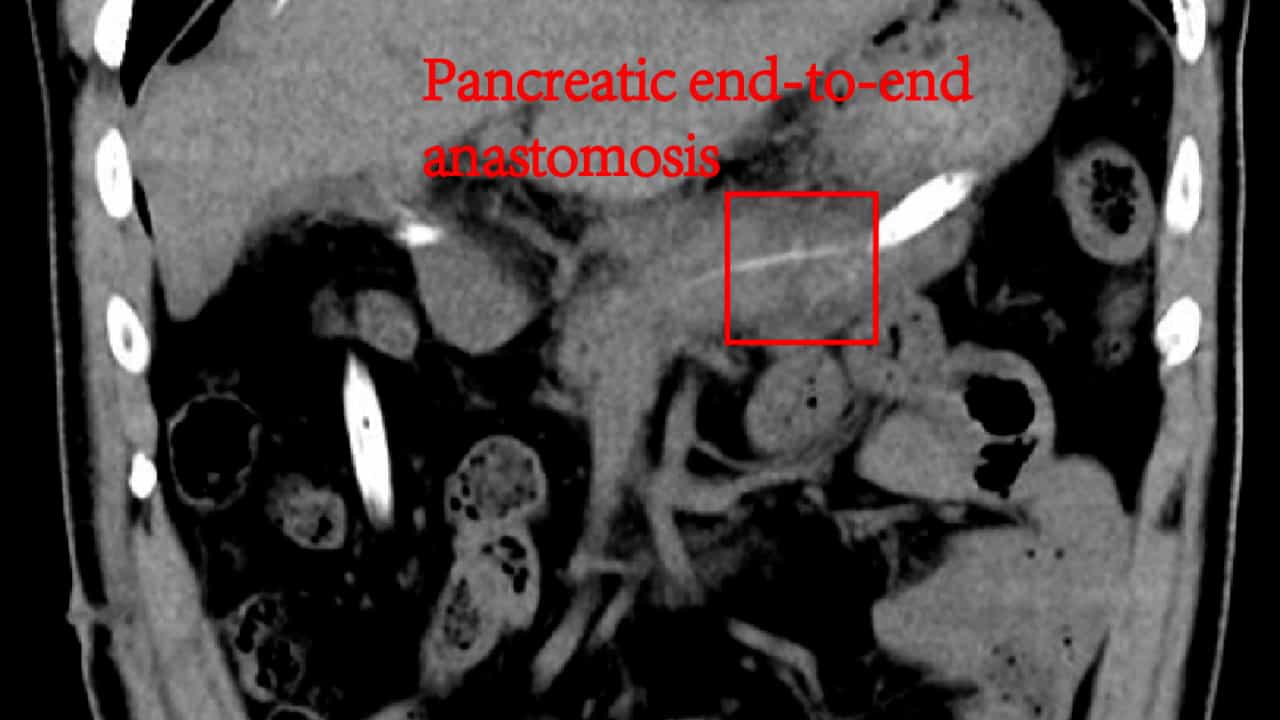
Application of Mid-Pancreatectomy with End-to-End Anastomosis in Pancreatic Benign Tumors
Published on: February 9, 2024
Clinical outcomes of interlocking main pancreatic duct-jejunal internal bridge drainage in middle pancreatectomy: A
1Department of General Surgery, Shengjing Hospital of China Medical University, Shenyang 110004, Liaoning Province, China.

Background:
Middle pancreatectomy (MP) is a surgical procedure that removes non-invasive lesions in the pancreatic neck and body, allowing for the preservation of pancreatic function. However, MP is associated with a higher risk of postoperative complications, and there's no clear consensus on which anastomotic method is preferable. In recent years, our team has developed a new method called interlocking main pancreatic duct-jejunal (IMPD-J) internal bridge drainage to MP.
Aim:
To compare perioperative and postoperative outcomes in patients who underwent IMPD-J bridge drainage and those underwent traditional duct-to-mucosa pancreatojejunostomy.
Methods:
Patients who underwent MP in our hospital between October 1, 2011 and July 31, 2023 were enrolled in this study. Patients were divided into two groups based on their pancreatojejunostomy technique: IMPD-J bridge drainage group and duct-to-mucosa pancreatojejunostomy group. Demographic data (age, gender, body mass index, hypertension, diabetes, etc.) and perioperative indicators [operation time, intraoperative bleeding, clinically relevant postoperative pancreatic fistula (CR-POPF), delayed gastric emptying, etc.] were recorded and analyzed statistically.
Results:
A total of 53 patients were enrolled in this study, including 23 in the IMPD-J Bridge Drainage group and 30 in the traditional duct-to-mucosa pancreatojejunostomy group. There were no significant differences in demographic or preoperative characteristics between the groups. Compared to traditional duct-to-mucosa pancreaticojejunostomy, IMPD-J bridge drainage had a significant shorter operation time (4.3 ± 1.3 hours vs 5.8 ± 1.8 hours, P = 0.002), nasogastric tube retention days (5.3 ± 1.7 days vs 6.5 ± 2.0 days, P = 0.031), lower incidence of delayed gastric emptying (8.7% vs 36.7%, P = 0.019), and lower incidence of CR-POPF (39.1% vs 70.0%, P = 0.025). Multivariate logistic regression analysis showed that pancreaticojejunostomy type (odds ratio = 4.219, 95% confidence interval = 1.238-14.379, P = 0.021) and plasma prealbumin (odds ratio = 1.132, 95% confidence interval = 1.001-1.281, P = 0.049) were independent risk factor for CR-POPF. In IMPD-J bridge drainage group, only one patient experienced recurrent pancreatitis due to the large diameter of the silicone tube and had it removed six months after surgery.
Conclusion:
Compared to traditional duct-to-mucosa pancreatojejunostomy, IMPD-J bridge drainage has the advantages of simplicity and fewer perioperative complications, with favorable long-term outcomes.
Insights
Interlocking main pancreatic duct-jejunal (IMPD-J) bridge drainage offers a simpler, safer alternative to traditional pancreatojejunostomy for middle pancreatectomy. This new method significantly reduces complications like delayed gastric emptying and pancreatic fistulas.
Area of Science:
- Surgical Innovation in Pancreatic Procedures
- Gastrointestinal Surgery Outcomes
- Minimally Invasive Surgical Techniques
Background:
- Middle pancreatectomy (MP) preserves pancreatic function but carries risks of postoperative complications.
- Optimal anastomotic techniques for MP remain debated.
- Development of interlocking main pancreatic duct-jejunal (IMPD-J) internal bridge drainage for MP.
Purpose of the Study:
- To compare perioperative and postoperative outcomes of IMPD-J bridge drainage versus traditional duct-to-mucosa pancreatojejunostomy in MP.
- To evaluate the efficacy and safety of the novel IMPD-J technique.
Main Methods:
- Retrospective study of 53 patients undergoing MP from October 2011 to July 2023.
- Patients divided into IMPD-J bridge drainage (n=23) and duct-to-mucosa pancreatojejunostomy (n=30) groups.
- Analysis of demographic data and perioperative indicators, including operation time, bleeding, CR-POPF, and delayed gastric emptying.
Main Results:
- IMPD-J bridge drainage group showed significantly shorter operation times (4.3 vs 5.8 hours) and fewer nasogastric tube retention days (5.3 vs 6.5 days).
- Lower incidence of delayed gastric emptying (8.7% vs 36.7%) and clinically relevant postoperative pancreatic fistula (CR-POPF) (39.1% vs 70.0%) in the IMPD-J group.
- Multivariate analysis identified pancreaticojejunostomy type and plasma prealbumin as independent risk factors for CR-POPF. One patient in the IMPD-J group experienced recurrent pancreatitis.
Conclusions:
- IMPD-J bridge drainage is simpler and associated with fewer perioperative complications compared to traditional duct-to-mucosa pancreatojejunostomy.
- The IMPD-J technique demonstrates favorable short-term and long-term outcomes for middle pancreatectomy.
- IMPD-J offers a promising alternative for improving surgical outcomes in MP.
Related Concept Videos
 01:26
Endoscopic Procedures V: ERCP
Patient...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD: