Related Experiment Video
Updated: May 16, 2025

Single-stage Dynamic Reanimation of the Smile in Irreversible Facial Paralysis by Free Functional Muscle Transfer
Published on: March 1, 2015
Nerve transfers for facial palsy: grading of volitional control after using the hypoglossal and masseter nerves
Mariano Socolovsky1, Roberto S Martins2, Simon Miedema3
11Department of Neurosurgery, University of Buenos Aires School of Medicine, Buenos Aires, Argentina.

Objective:
Nerve transfers are utilized to restore function in cases of facial palsy when the proximal nerve stump is not available for reconstruction. The process of regaining partial or complete voluntary control of the reinnervated muscles is mediated by changes in the central nervous system, known as brain plasticity. This involves the disconnection of the original donor nerve-related neural programs and their reconnection to the programs of the acceptor nerve. In this study, the authors aimed to evaluate the degree of voluntary control achieved after 2 nerve transfer procedures for facial palsy.
Methods:
A series of patients with complete unilateral facial palsy (cranial nerve [CN] VII) who underwent nerve transfer surgery using the hypoglossal (CNXII) or the masseter (CNV) as donors were analyzed. A modified 4-point plasticity grading scale (PGS) was used to determine the level of donor nerve disconnection from its original brain program and reconnection to the central program of the facial muscles, with grade 1 defined as a complete lack of plasticity and grade 4 as full independent control. Patient variables, including sex, age, time from trauma to surgery, duration of follow-up, and PGS outcomes, were recorded and statistically analyzed.
Results:
A total of 91 patients were included in the study: 67 patients (74%) underwent CNXII-CNVII nerve transfer, while 24 (26%) received CNV-CNVII nerve transfer. The mean ± SD PGS scores of the CNXII-CNVII and CNV-CNVII transfer groups were 1.64 ± 0.6 and 1.63 ± 0.6, respectively. Within the CNXII-CNVII subgroup, age at time of surgery (p < 0.001) and time from trauma to surgery (p = 0.008) were identified as negative predictors for PGS outcomes, whereas quality of rehabilitation emerged as a positive predictive factor (p = 0.005). No associations were observed between sex, follow-up duration, and brain plasticity.
Conclusions:
After nerve transfer for facial palsy, brain plasticity is often insufficient to achieve full independence of movements generated by the donor motor program.
Related Concept Videos
 01:22
Cranial Nerves: Types Part II
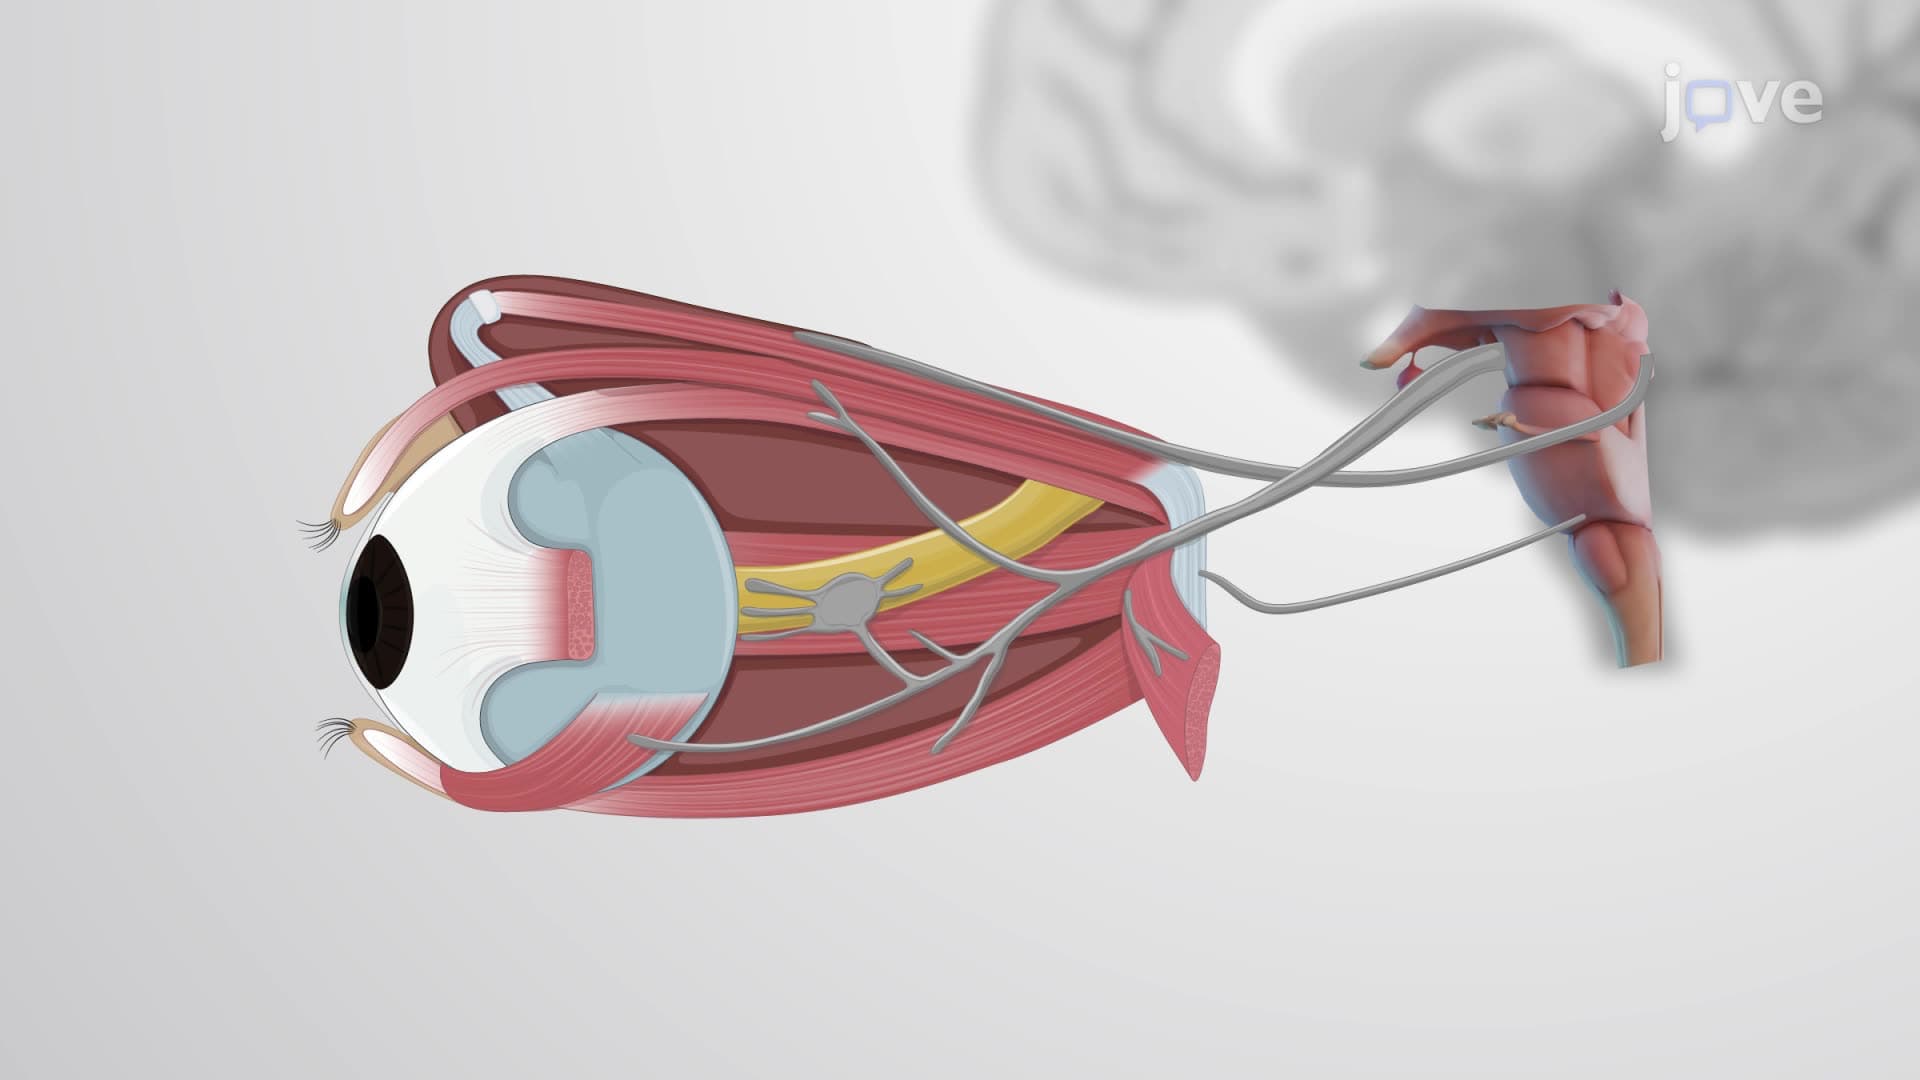
Facial Nerve (Cranial Nerve VII)
Cranial nerve VII, or the facial nerve,...
 01:14
Cranial Nerves: Types Part I
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
 01:19
Cranial Nerves: Overview and Anatomy
 01:19
Brainstem
The Midbrain
The midbrain is located beneath the diencephalon and connects the cerebrum with the lower parts of the brain. The cerebral peduncles are prominent midbrain structures that house the...
 01:11
Direct Motor Pathways
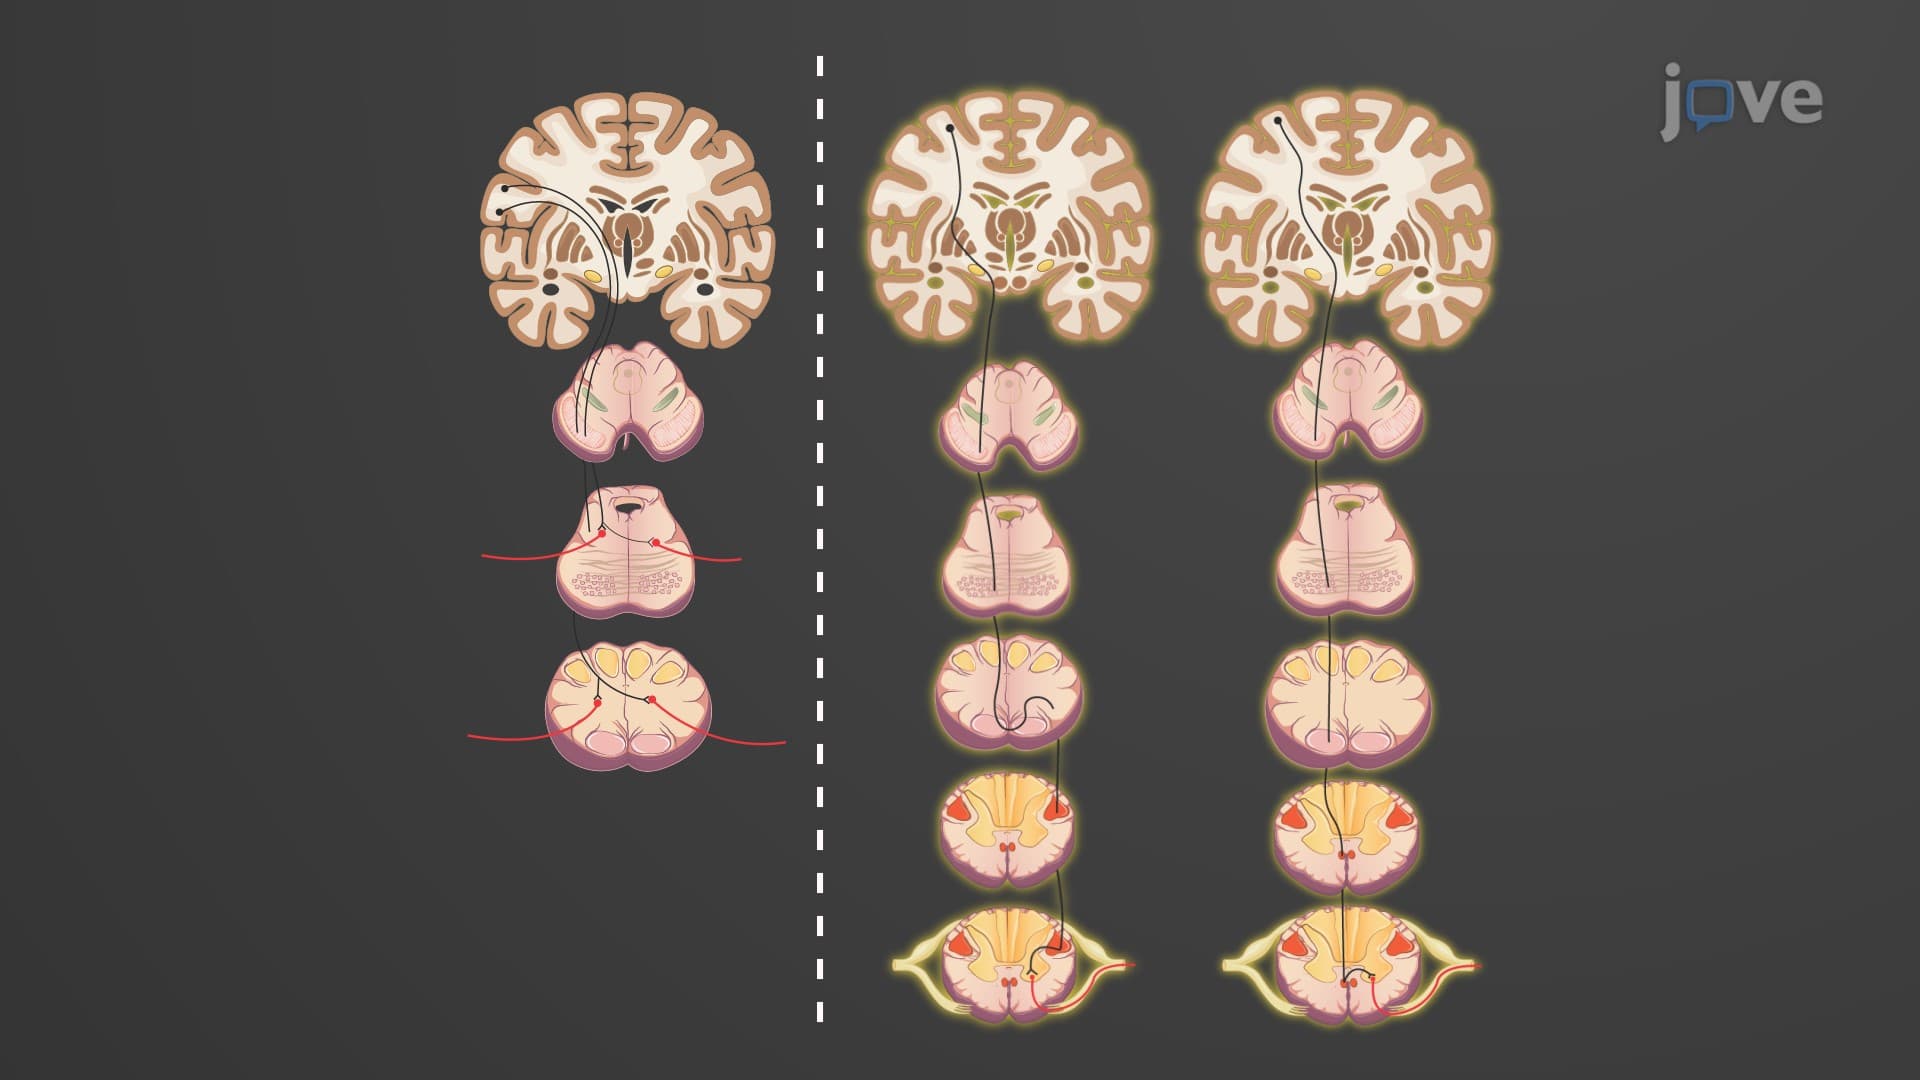
The corticospinal tract is responsible for the voluntary movement of the limbs and trunk. It originates in the cerebral cortex of the brain and descends through the cerebrum's internal capsule and...
 01:18
Hierarchy of Motor Control