Related Experiment Video
Updated: May 8, 2025

Cell-based Assay Protocol for the Prognostic Prediction of Idiopathic Scoliosis Using Cellular Dielectric Spectroscopy
Published on: October 16, 2013
Left-sided thoracic curves in adolescent idiopathic scoliosis: are the outcomes different?
Bryan O Ren1, Anne Marie Dumaine2, Jerry Y Du3
1Department of Orthopaedic Surgery, University of Michigan, Ann Arbor, MI, USA.

Purpose:
The purpose was to compare outcomes in adolescent idiopathic scoliosis (AIS) patients with left vs. right main thoracic curves. A secondary purpose was to elucidate surgeon opinions between these two curve types and differences in surgical approach via a survey.
Methods:
A multicenter database was utilized to identify AIS patients with left thoracic curves without significant MRI abnormalities from 1996 to 2018 receiving posterior spinal fusion. A 1:1 propensity match was performed to right thoracic curves. Differences between the curve groups were analyzed.
Results:
Fifty patients had left thoracic curves. Curve direction had no impact on levels fused, surgical time, length of hospitalization, estimated blood loss, cell saver transfused, death, pain, pseudoarthrosis, reoperation, or infection rates. At two-years postoperatively, left curves had greater T2-T12 kyphosis (37 vs. 31°, p = .02), and variations in T1 tilt angle direction (30 vs. 39 left tilt, p = .04), EIV angulation (-2 vs. 5°, p < .01), EIV translation (0.6 vs. -0.2 cm, p = .03), and left shoulder elevation (12 in left curves vs. 25 in right curves, p = .01). There were no differences in correction rate, Cobb angle, lumbar curve, T12-S1 lordosis, shoulder height difference, or SRS 22 scores.
Conclusion:
In AIS, there are no significant differences in surgical characteristics or outcomes between left and right-thoracic curves. Notably, curve direction does not influence correction rate, surgical time, levels fused, length of hospitalization, blood loss, pain, SRS 22 scores, or rates of reoperation, infection, or pseudoarthrosis. There are some variations in radiographic parameters postoperatively that are unlikely to be clinically significant.
More Related Videos
 12:25
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:16
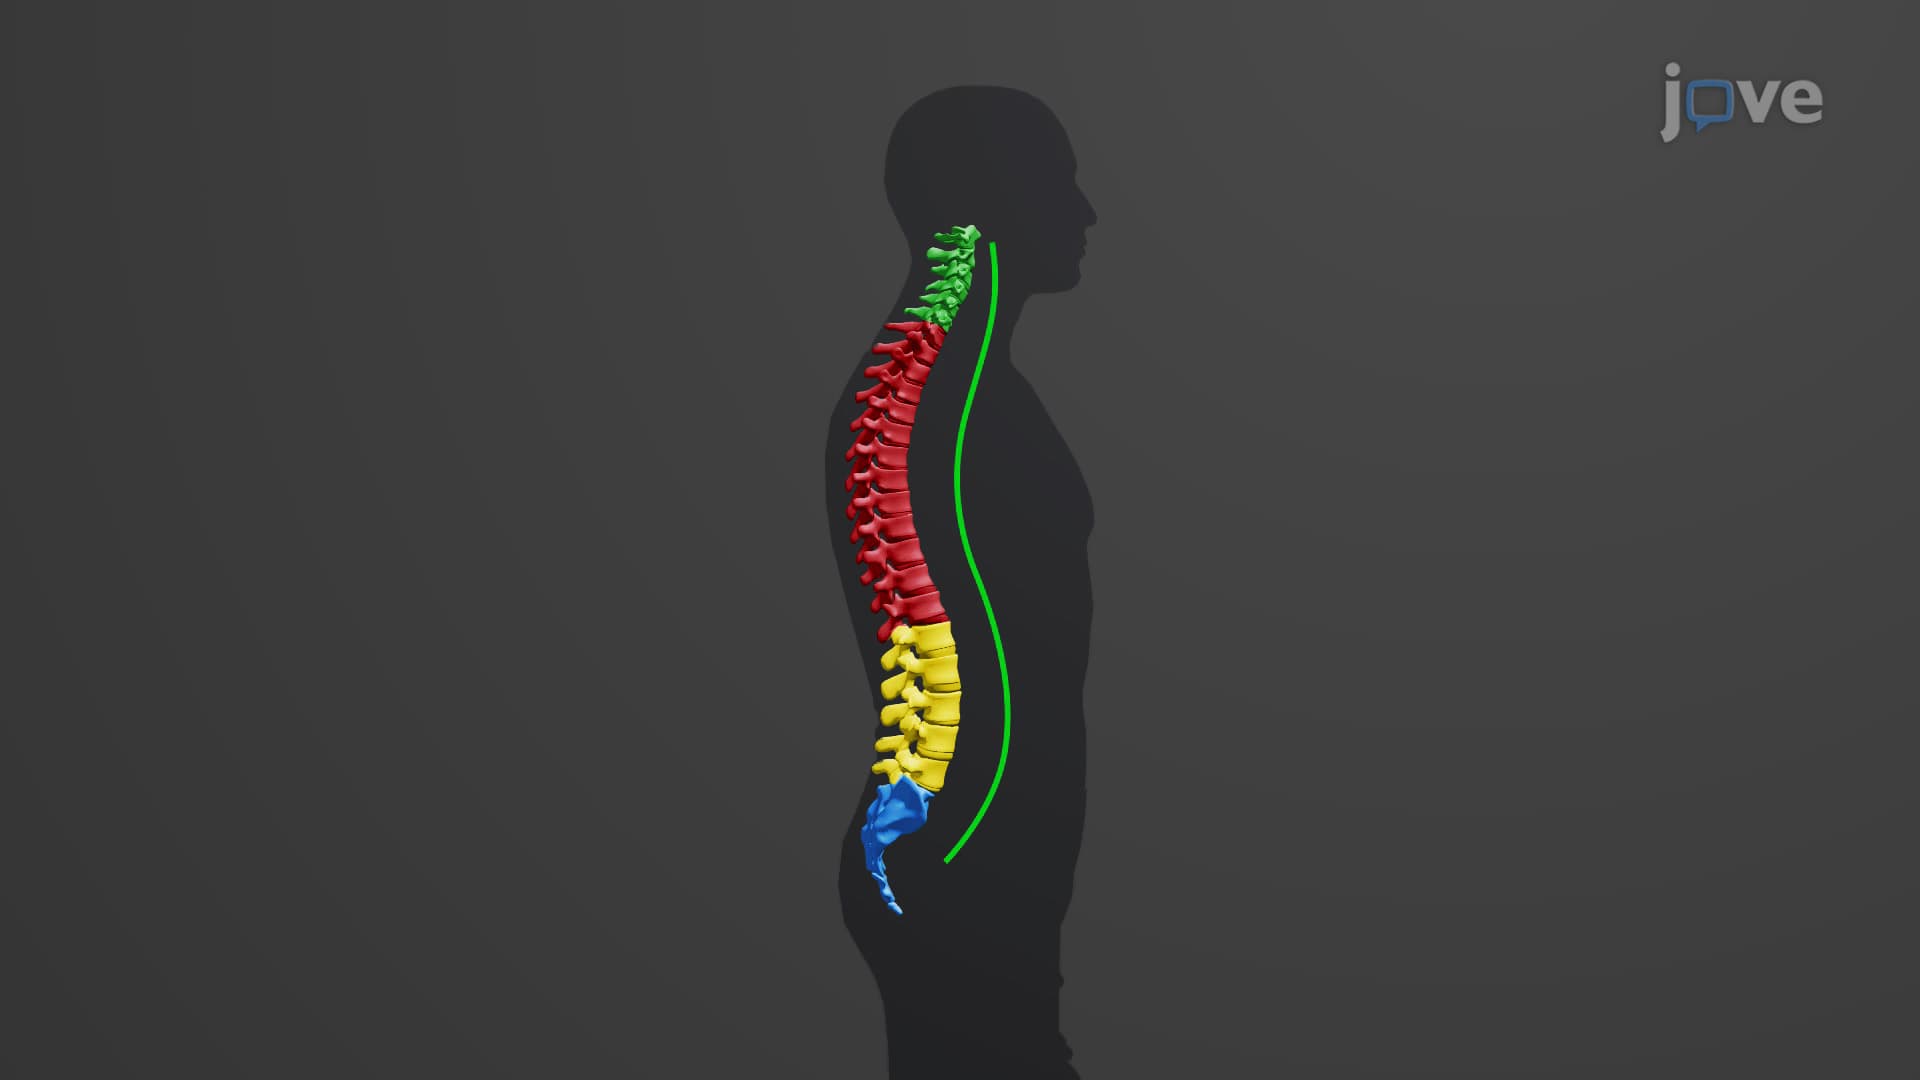
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form...
 01:20
The Thoracic Cage: Ribs
Parts of a Typical Rib
A typical rib has a head, neck, and body. The posterior end of the rib is called the head, followed by a narrow neck. The head articulates primarily with the costal...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...
 01:14
Bending of Curved Members - Strain Analysis
The important part of bending analysis for such a member...
 01:17
The Thoracic Cage: Sternum
The sternum is the elongated bony structure on the anterior side of the thoracic cage. It consists of three parts: the manubrium, the body, and the xiphoid...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...