Related Experiment Video
Updated: May 15, 2025


Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Management of Pheochromocytoma in The Setting of Acute Stroke
Solomon Oak1,2, Mahsa Javid1,3,2, Glenda G Callender1
1From the Department of Surgery, Section of Endocrine Surgery, Yale University School of Medicine, New Haven, Connecticut.

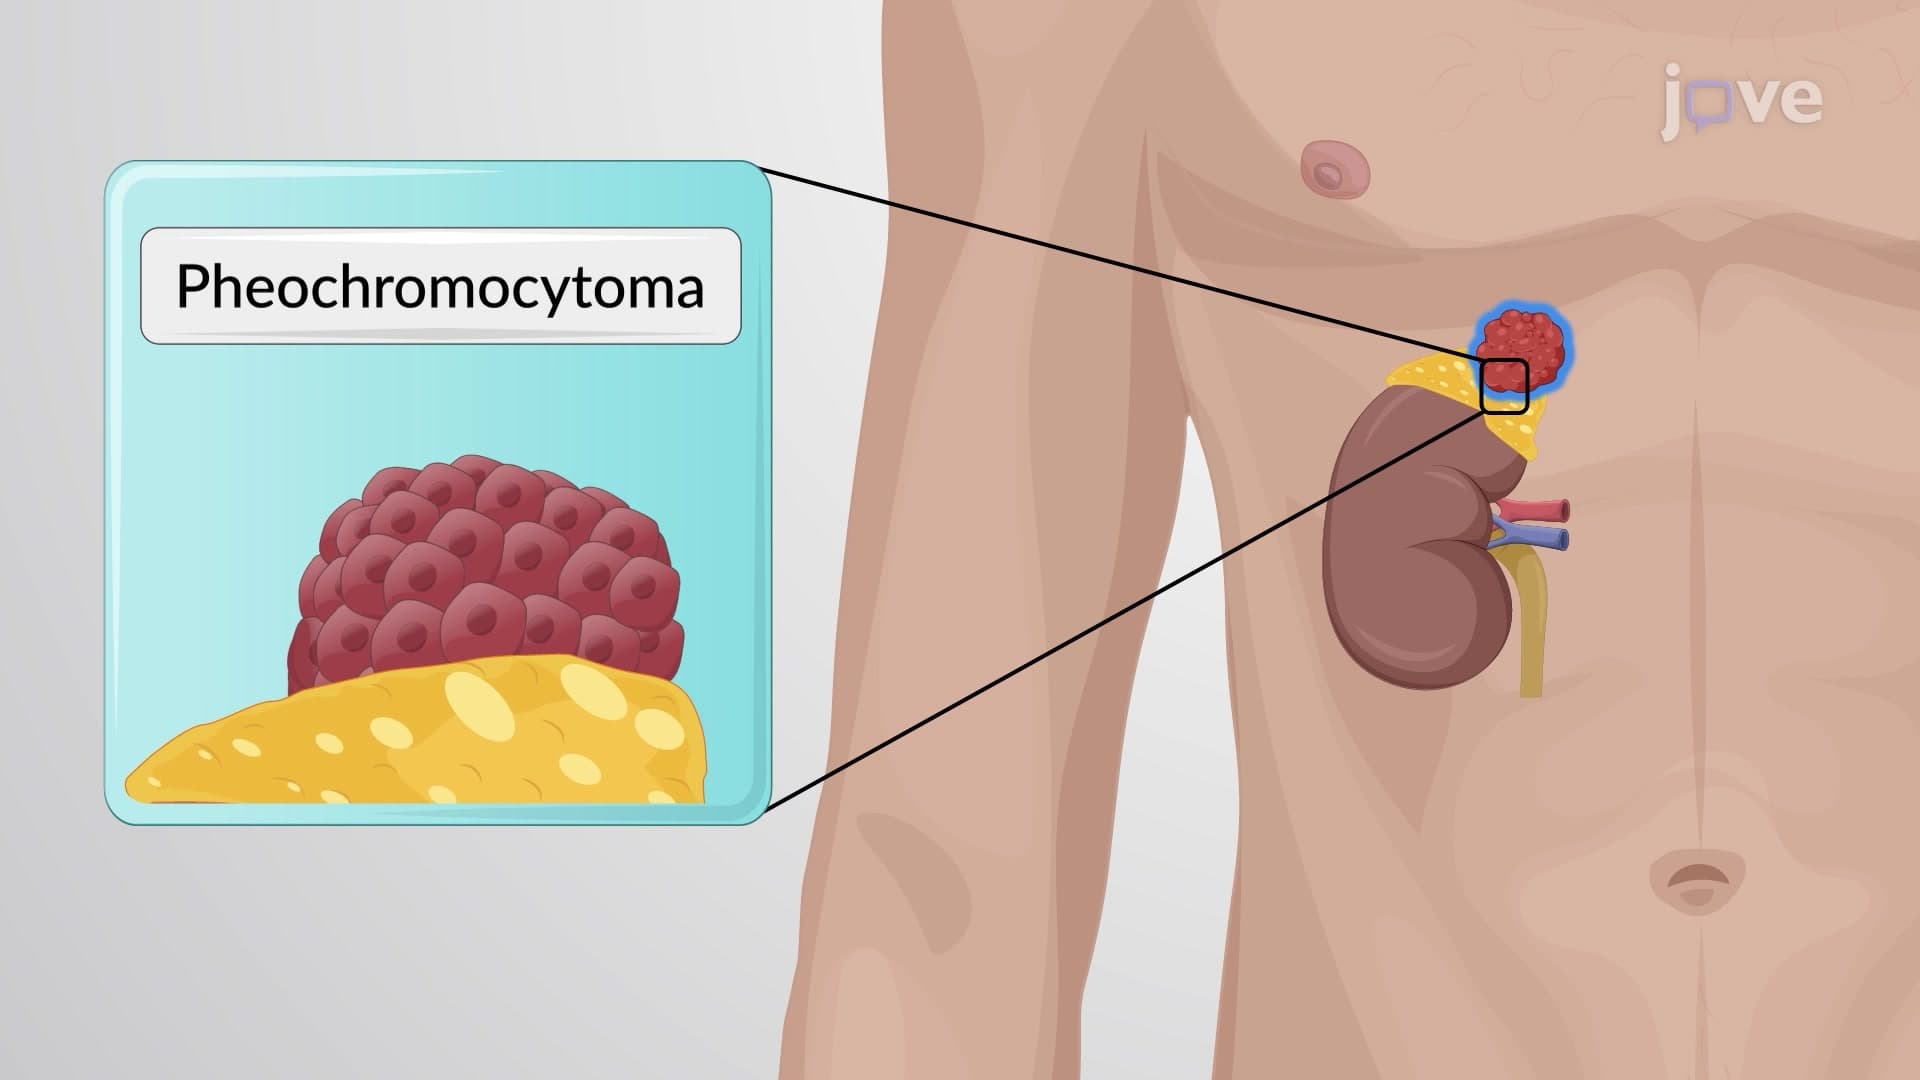
Stroke is a rare presenting symptom of pheochromocytoma; therefore, a balance between adequate pre-operative medical blockade and expedition of surgery to minimize the risk of further peri-operative stroke is needed. However, currently there are no established guidelines regarding timing of surgery or length of pre-operative blockade in these patients. We report a case of pheochromocytoma in a 53-year-old woman presenting with a hemorrhagic transformation of an ischemic stroke. We describe the clinical course, diagnosis, and management of our case and then discuss similar cases in the literature as well as optimal pre-operative management. We review all clinical data and describe the patient presentation and treatment. A comprehensive literature review of the topic is discussed. Pheochromocytoma in our patient presented as a combination of stroke, severe hypertension, and tachycardia. A computed tomography scan, evaluation of catecholamine levels, and 123iodine-labeled metaiodobenzylguanidine scan confirmed pheochromocytoma. Hemodynamic stability was achieved after 9 weeks of treatment with selective alpha-blockade and other antihypertensive medications, after which laparoscopic transabdominal adrenalectomy was performed. Despite a normal blood pressure at pre-induction, the patient experienced 6 episodes of severe hypertension intra-operatively. There were no operative complications and hypertension resolved postoperatively. A review of the literature identified 5 similar cases; however, the optimal management of these patients remains unclear. Our case highlights the importance of including pheochromocytoma in the differential diagnosis of patients with stroke. Optimal results may be achieved by ensuring at least 6 weeks of recovery following stroke, and inducing orthostatic hypotension for at least 2 weeks prior to the surgery. Abbreviation: CT computed tomography.
Stroke is a rare presenting symptom of pheochromocytoma; therefore, a balance between adequate pre-operative medical blockade and expedition of surgery to minimize the risk of further peri-operative stroke is needed. However, currently there are no established guidelines regarding timing of surgery or length of pre-operative blockade in these patients. We report a case of pheochromocytoma in a 53-year-old woman presenting with a hemorrhagic transformation of an ischemic stroke. We describe the clinical course, diagnosis, and management of our case and then discuss similar cases in the literature as well as optimal pre-operative management. We review all clinical data and describe the patient presentation and treatment. A comprehensive literature review of the topic is discussed. Pheochromocytoma in our patient presented as a combination of stroke, severe hypertension, and tachycardia. A computed tomography scan, evaluation of catecholamine levels, and 123iodine-labeled metaiodobenzylguanidine scan confirmed pheochromocytoma. Hemodynamic stability was achieved after 9 weeks of treatment with selective alpha-blockade and other antihypertensive medications, after which laparoscopic transabdominal adrenalectomy was performed. Despite a normal blood pressure at pre-induction, the patient experienced 6 episodes of severe hypertension intra-operatively. There were no operative complications and hypertension resolved postoperatively. A review of the literature identified 5 similar cases; however, the optimal management of these patients remains unclear. Our case highlights the importance of including pheochromocytoma in the differential diagnosis of patients with stroke. Optimal results may be achieved by ensuring at least 6 weeks of recovery following stroke, and inducing orthostatic hypotension for at least 2 weeks prior to the surgery. Abbreviation: CT computed tomography.


Related Concept Videos
 01:30
Adrenergic Agonists: Therapeutic Uses
Emergency and Intensive Care Unit (ICU) applications: Pressor agents increase blood pressure, heart rate, and contractility in shock and organ failure situations. Dopamine can induce vasodilation and stimulate adrenoceptors. Endogenous catecholamines are effective in treating cardiogenic shock. α2-agonists like clonidine can reverse anesthesia-induced hypertension.
Allergies and...
 01:26
Heart Failure Drugs: Inhibitors of Renin-Angiotensin System
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:27
Adrenergic Antagonists: Pharmacological Actions of β-Receptor Blockers
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally,...
 01:24
Parkinson's Disease: Treatment
Parkinson's Disease is primarily a result of the loss of dopaminergic neurons in the substantia nigra pars compacta. The cornerstone of...