Related Experiment Video
Updated: Aug 23, 2026
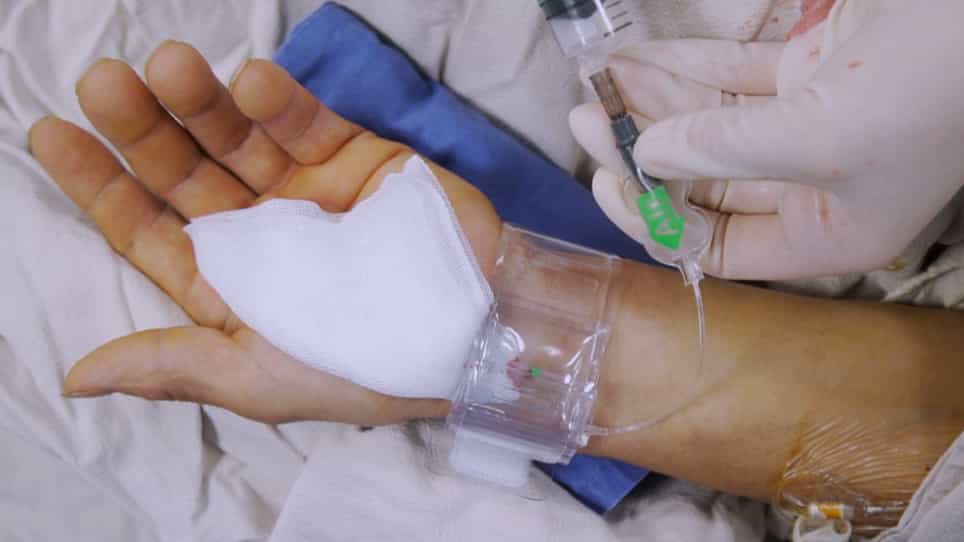

Transradial Access Chemoembolization for Hepatocellular Carcinoma Patients
Published on: September 20, 2020
Severe Radial Artery Spasm Causing Radial Artery Sheath Entrapment: A Case Report
Zahid Khan1,2,3,4, Tat Koh5
1Acute Medicine, Mid and South Essex NHS Foundation Trust, Southend-on-Sea, GBR.

Over the past decade, there has been a significant increase in the use of the transradial approach in patients undergoing coronary angiography due to lower risk of complications and quicker recovery. Nevertheless, radial artery spasm remains a challenge, particularly in anxious men and women, and young female patients. Transradial access is associated with a significantly lower bleeding risk compared to transfemoral access. The radial artery is predisposed to significant spasms as it has a smaller caliber and is highly sensitive to mechanical and humoral stresses compared to femoral artery. We present the case of an 82-year-old male who was transferred from a district general hospital for coronary angiography and developed severe spasm in the right radial artery at the end of the procedure, resulting in radial artery sheath entrapment. We administered 600 microgram of intra-arterial nitrates, 2.5 mg intra-arterial verapamil, 3.5 mg midazolam, and 2.5 mg intravenous morphine with no effect on the spasm. Following this, we applied a blood pressure cuff and inflated it to 156 mmHg, which was 40 mmHg greater than his systolic blood pressure, for five minutes to occlude the brachial artery. This resulted in smooth muscle relaxation facilitating the removal of radial sheath without any adverse outcomes.
Over the past decade, there has been a significant increase in the use of the transradial approach in patients undergoing coronary angiography due to lower risk of complications and quicker recovery. Nevertheless, radial artery spasm remains a challenge, particularly in anxious men and women, and young female patients. Transradial access is associated with a significantly lower bleeding risk compared to transfemoral access. The radial artery is predisposed to significant spasms as it has a smaller caliber and is highly sensitive to mechanical and humoral stresses compared to femoral artery. We present the case of an 82-year-old male who was transferred from a district general hospital for coronary angiography and developed severe spasm in the right radial artery at the end of the procedure, resulting in radial artery sheath entrapment. We administered 600 microgram of intra-arterial nitrates, 2.5 mg intra-arterial verapamil, 3.5 mg midazolam, and 2.5 mg intravenous morphine with no effect on the spasm. Following this, we applied a blood pressure cuff and inflated it to 156 mmHg, which was 40 mmHg greater than his systolic blood pressure, for five minutes to occlude the brachial artery. This resulted in smooth muscle relaxation facilitating the removal of radial sheath without any adverse outcomes.
More Related Videos
Related Concept Videos
 01:11
Assessment of radial pulse
The radial pulse, located at the wrist, is often the preferred site for assessing peripheral pulse because of its accessibility and dependability. The process of determining the radial pulse involves several steps:
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:12
Arteries of the Upper Limbs
 01:30
Peripheral Artery Disease I: Introduction
 01:21
Peripheral Arterial Disease II: Clinical Manifestations and Diagnostic Evaluation
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies