Related Experiment Video
Updated: May 14, 2025
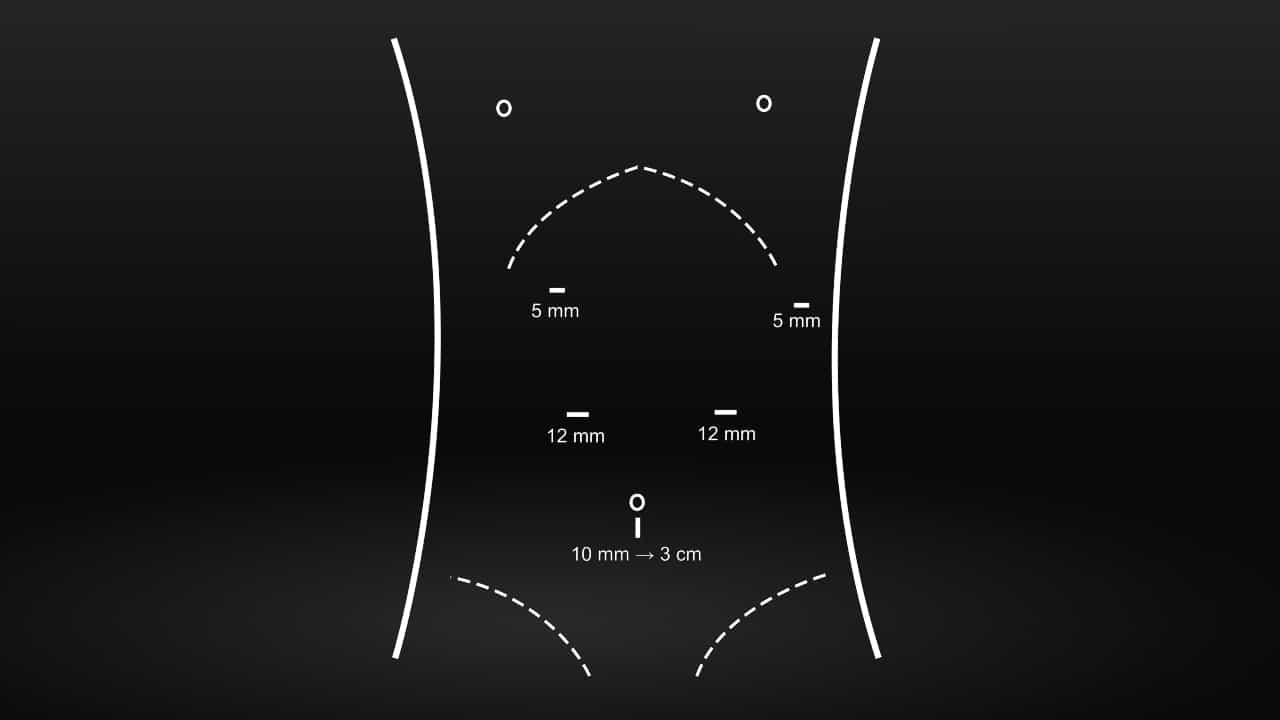

Laparoscopic Splenectomy with Pericardial Devascularization for Hypersplenism and Esophageal Variceal Hemorrhage Due to Portal Hypertension
Published on: November 15, 2024
Development of an explainable prediction model for portal vein system thrombosis post-splenectomy in patients with
Dou Qu1,2,3,4, Duwei Dai3,5, Guodong Li1,3,4
1Institute for Precision Medicine, Xi'an Jiaotong University Second Affiliated Hospital, Xi'an, Shaanxi, China.

Background:
Portal vein system thrombosis (PVST) is a common and potentially life-threatening complication following splenectomy plus pericardial devascularisation (SPDV) in patients with cirrhosis and portal hypertension. Early prediction of PVST is critical for timely intervention. This study aimed to develop a machine learning-based prediction model for PVST occurrence within 3 months after splenectomy.
Methods:
392 patients with cirrhosis who underwent splenectomy at the Second Affiliated Hospital of Xi'an Jiaotong University between 1 July 2016 and 31 December 2022 were enrolled in this study and followed up for 3 months. The predictive model integrated 37 candidate predictors based on accessible clinical data, including demographic characteristics, disease features, imaging results, laboratory values, perioperative details and postoperative prophylactic therapies, and finally, eight predictors were selected for model construction. The five machine learning algorithms (logistic regression, Gaussian Naive Bayes, decision tree, random forest and AdaBoost) were employed to train the predictive models for assessing risks of PVST, which were validated using five fold cross-validation. Model discrimination and calibration were estimated using receiver operating characteristic curves(ROC), accuracy, sensitivity, specificity, positive predictive value, negative predictive value and Brier scores. The outcome of the predictive model was interpreted using SHapley Additive exPlanations (SHAP), which provided insights into the factors influencing PVST risk prediction.
Results:
During the 3-month follow-up, a total of 144 (36.73%) patients developed PVST. The AdaBoost model demonstrated the highest discriminative ability, with a mean area under the receiver operating characteristic curve (AUROC) of 0.72 (95% CI 0.60 to 0.84). Important features for predicting PVST included albumin, platelet addition, the diameter of the portal vein, γ-glutamyl transferase, length of stay, activated partial thromboplastin time, D-dimer level and history of preoperative gastrointestinal bleeding, as revealed by SHAP analysis.
Conclusions:
The machine learning-based prediction models can provide an initial assessment of 3-month PVST risk after SPDV in patients with cirrhosis and portal hypertension. The AdaBoost model demonstrates moderate discriminative ability in distinguishing between high-risk and low-risk patients, with an AUROC of 0.72 (95% CI 0.60 to 0.84). By incorporating SHAP analysis, the model can offer transparent explanations for personalised risk predictions, facilitating targeted preventive interventions and reducing excessive interventions across the entire patient population.

Related Concept Videos
 01:28
Esophageal Varices-II: Clinical Features and Management
In the initial assessment, a thorough review of the patient's medical history is vital to identify risk factors such as liver disease, alcohol...
 01:24
Esophageal Varices-I: Introduction
 01:21
Hepatic Portal System
At its core, the hepatic portal vein is the result of a confluence of the superior and inferior mesenteric veins along with the splenic vein. Each of these veins has a unique role. The superior mesenteric vein is...