Related Experiment Video
Updated: May 14, 2025


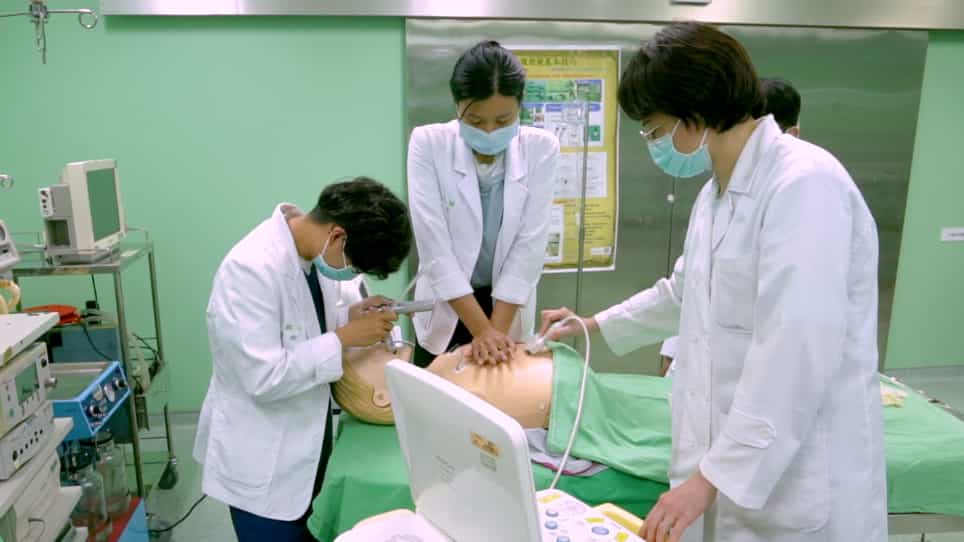
Standardized Model of Ventricular Fibrillation and Advanced Cardiac Life Support in Swine
Published on: January 30, 2020
Impact of Body Mass Index on Stroke in Extracorporeal Cardiopulmonary Resuscitation: Data from the Extracorporeal
Jin Kook Kang1, Shi Nan Feng1, Winnie L Liu1
1Division of Neuroscience Critical Care, Departments of Neurology, Neurosurgery, and Anesthesiology and Critical Care Medicine, Johns Hopkins University School of Medicine, Baltimore, MD 21205, USA.

Abstract:
Objective: We aimed to characterize the impact of body mass index (BMI) on stroke in patients receiving extracorporeal cardiopulmonary resuscitation (ECPR). Methods: We queried the Extracorporeal Life Support Organization registry for patients receiving ECPR (2020-2024). Patients were categorized into five BMI groups: underweight (<18.5 kg/m2), normal weight (18.5-24.9 kg/m2), overweight (25-29.9 kg/m2), class 1 obesity (30-34.9 kg/m2), and class 2 obesity or above (≥35 kg/m2). A generalized additive model (GAM) analysis was used to identify the BMI range with the greatest stroke risk. Multivariable regression was used to compare odds of stroke between standard BMI groups and normal weight. Propensity score matching was used to compare stroke and mortality between normal weight and the BMI group with the highest predicted stroke risk. Results: Of 6390 patients (median age = 57.5, 68.6% male), 470 (7.4%) had a stroke during ECMO support (4.5% ischemic; 3.4% hemorrhagic). A total of 9.6% (n = 131) of class 1 obesity patients experienced stroke compared with 6.6% (n = 111) of normal weight, 6.9% (n = 79) of class 2 obesity or above, 6.9% (n = 143) of overweight, and 5.4% (n = 6) of underweight patients (p = 0.01). The GAM analysis showed a highest predicted stroke risk for class 1 obesity patients (n = 1366), which was confirmed by multivariable regression (adjusted odds ratio (aOR) = 1.63, 95%CI = 1.01-2.62, p = 0.045). After propensity matching (n = 357 each), class 1 obesity was associated with ischemic (aOR = 2.01, 95%CI = 1.02-4.08, p = 0.047) but not hemorrhagic stroke. Odds of hospital mortality were higher in both class 1 and 2 obesity patients compared with normal weight. Conclusions: Class 1 obesity was associated with increased odds of ischemic but not hemorrhagic stroke compared with normal weight patients.

Related Concept Videos
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...
 01:27
Regulation of Stroke Volume
Preload refers to the degree of stretch on the heart before it contracts. It's analogous to the stretching of a rubber band; the more it's stretched, the more forcefully it snaps back. This concept is encapsulated in the Frank-Starling...
 01:20
Exercise and Cardiovascular Response
Light to moderate physical activity initiates a series of interconnected responses in the body. The heart rate modestly increases in anticipation of the workout, followed by widespread vasodilation as oxygen consumption by skeletal muscles increases. This results in decreased peripheral resistance, increased capillary blood flow, and accelerated...
 01:11
Cardiac Output and Stroke Volume
In an average resting adult male, the typical...
 01:17
Exercise and Cardiac Output
Sustained exercise increases the muscles' oxygen demand, which can be...