Related Experiment Video
Updated: May 23, 2025
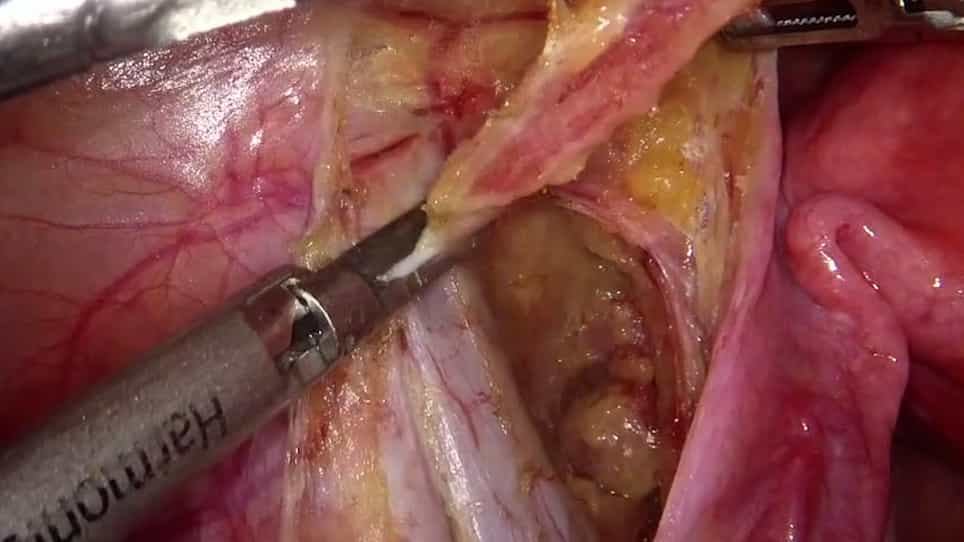
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Preoperative tumour size assessment in patients with early-stage cervical cancer: Final results of the SENTIX study
Martina Borčinová1, Christhardt Köhler2, Kristýna Němejcová3
1Department of Gynecology, Obstetrics and Neonatology, First Faculty of Medicine, Charles University and General University Hospital in Prague, Prague, Czech Republic.

Background:
Preoperative tumour size is a key prognostic marker in tailoring surgical treatment in early-stage cervical cancer. This post-hoc analysis assessed the accuracy of preoperative tumour size evaluation via imaging, utilizing data from the prospective, international, multicentre SENTIX study that evaluated safety of sentinel lymph node (SLN) biopsy without pelvic lymph node dissection in patients with early-stage cervical cancer.
Methods:
Between 05/2016-09/2020, forty-seven sites across 18 countries enrolled cervical cancer patients (FIGO2018 stages 1A1/lymphovascular-space-invasion-positive to 1B2). Preoperative staging included pelvic MRI or ultrasound as mandatory imaging modalities. All patients underwent primary surgical treatment. Pathological assessment of surgical specimens served as reference standard for evaluating the accuracy of preoperative assessments.
Results:
Among the 680 included patients, although the mean tumour size discrepancy between preoperative/pathological assessments was only 1.24 ± 8.891 mm, postoperative pT stage was upgraded in 187 (27.5 %) and downgraded in 74 (10.9 %) patients. Discrepancy of ≥10 mm was observed among 155 (22.8 %) patients across all stages, with underestimation in 105 (15.4 %), overestimation in 50 (7.4 %), and a positive correlation (P < 0.0001) between the pathological tumour size and the discrepancy in size assessment. If a maximum 2 cm tumour size threshold were applied to guide the decision between simple and radical hysterectomy, underestimation would result in inadequate surgical management for 9.0 % of patients, whereas overestimation would lead to unnecessarily radical procedures in 5.1 % of cases.
Conclusions:
The study highlights, that even with the use of modern imaging in preoperative staging, inaccuracies in tumour size assessment remain a common cause of up-/down-staging after surgery resulting in potential inappropriate planning of surgery, and thus in procedure that is either excessively or insufficiently radical.
Trial Registration:
ClinicalTrials.gov: NCT02494063.
More Related Videos
 06:46
Competing-Risk Nomogram for Predicting Cancer-Specific Survival in Multiple Primary Colorectal Cancer Patients after Surgery
Published on: September 27, 2024
 04:04
Endobronchial Ultrasound-guided Intratumoral Injection of Cisplatin for the Treatment of Isolated Mediastinal Recurrence of Lung Cancer
Published on: February 12, 2017